Related Experiment Video
Updated: Aug 21, 2026
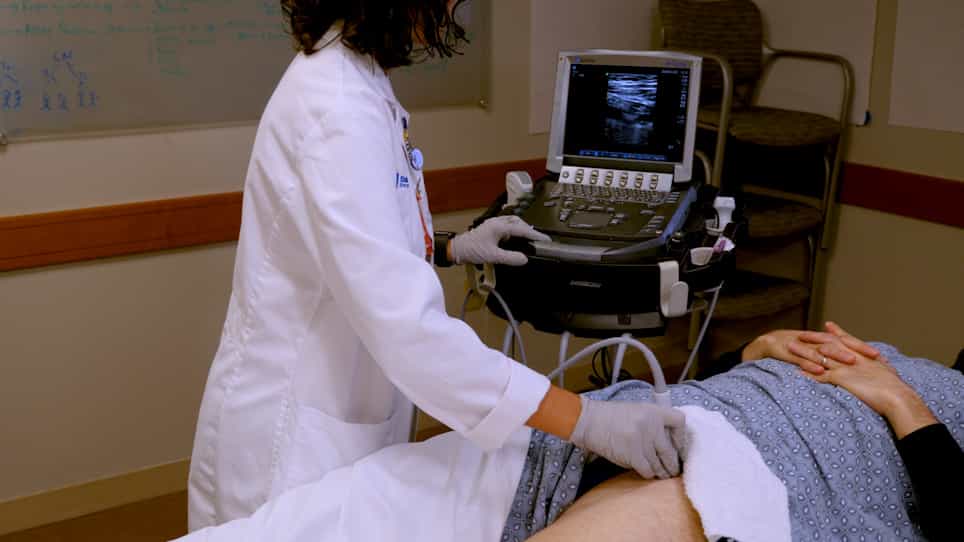

Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Diagnosis of deep venous thrombosis and alternative diseases in symptomatic outpatients
Werner Blättler1, Ivana Martinez, Irene K. Blättler
1Angio Bellaria, Center for Vascular Diseases, Bellariastrasse 40, Zürich CH-8038, Switzerland.

Insights
A low clinical probability combined with a negative D-dimer test reliably excludes deep vein thrombosis (DVT). Ultrasound remains valuable for diagnosing alternative conditions, suggesting comprehensive diagnostic strategies are essential.
Area of Science:
- Medical Diagnostics
- Vascular Medicine
- Clinical Decision-Making
Background:
- Deep vein thrombosis (DVT) management is debated, with recent evidence supporting withholding anticoagulation in low-risk patients with normal D-dimer levels.
- Diagnostic strategies for DVT, particularly for distal thrombi, require careful evaluation.
- The utility of routine ultrasound in suspected DVT cases warrants further investigation.
Purpose of the Study:
- To compare a score-based, explicit DVT assessment model with an empirical, implicit approach.
- To evaluate the diagnostic performance of a combined clinical probability and D-dimer testing strategy.
- To determine the information gained from routine ultrasound in suspected DVT patients.
Main Methods:
- Consecutive patients with suspected DVT underwent D-dimer testing, clinical probability assessment (implicit vs. explicit scoring), and objective testing.
- Ultrasound was performed on all patients; venography and other tests were used as indicated.
- Retrospective analysis compared the implicit assessment, explicit Wells score, and the value of ultrasound.
Main Results:
- DVT was confirmed in 28% of patients. The implicit assessment identified proximal DVT more effectively than the explicit Wells score.
- A combination of low implicit clinical probability and a negative D-dimer test achieved a 98% negative predictive value for DVT.
- Ultrasound proved useful in 91% of cases, aiding in the diagnosis of alternative conditions.
Conclusions:
- Proximal and distal DVT can be reliably excluded using a sensitive clinical probability assessment and a negative D-dimer assay.
- Ultrasound is crucial for identifying alternative diagnoses, highlighting the limitations of strategies reducing its use.
- Comprehensive diagnostic approaches are necessary for effective DVT management.
Abstract:
BACKGROUND: The management of patients with suspected deep vein thrombosis (DVT) is controversial. Recent studies have suggested that anticoagulant treatment can safely be withheld if the clinical probability is low and the D-dimer concentration in blood is normal. We examined a diagnostic algorithm comparing a score-based, explicit assessment model with our empirical, implicit approach, which was designed to be more sensitive for distal DVT. We further investigated what information would be lost by not performing a routine ultrasound examination in each patient. METHODS: Consecutive patients with suspected DVT first received a D-dimer estimation, then an examination to assess the clinical probability, and ultimately objective testing for DVT or alternative diseases. Ultrasound was used in all patients; venography and other tests were performed as indicated. The implicit assessment of clinical probability was compared with the explicit scoring system of Wells et al., and the value of ultrasound was assessed retrospectively. RESULTS: In 57 of 206 patients (28%), DVT was confirmed. A high clinical probability was attributed to all pelvic and femoral DVT (except one), but popliteal and crural DVT were missed in 78% by the explicit approach and in 34% by the implicit approach. The negative predictive values for any DVT were 83% for the explicit assessment and 92% for the implicit assessment, 95% for the D-dimer estimation, and 98% (95% CI 92-99) for the combination of low implicit clinical probability and a negative D-dimer test. This combination yielded the same NPV for isolated crural DVT and was found in 41% of all suspected cases. An alternative organic diagnosis was established in 100 patients (48%) and no organic diagnosis was made in 49 (24%). In half of all suspected cases, irrespective of whether DVT was present or not, concomitant or alternative venous pathologies were observed. Ultrasound was found useful in 91% of cases. CONCLUSIONS: Proximal as well as distal DVT can reliably be excluded when both a sensitive assessment of clinical probability and a bedside D-dimer assay are negative. Nevertheless, ultrasound is helpful in establishing alternative diagnoses. Strategies to reduce the number of ultrasound investigations appear to lack comprehensiveness.

Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care