Related Experiment Video
Updated: Aug 21, 2026


Diagnosis of Hirschsprung's Disease by Immunostaining Rectal Suction Biopsies for Calretinin, S100 Protein and Protein Gene Product 9.5
Published on: April 26, 2019
Thickening of the internal anal sphincter in idiopathic constipation in children
Alireza S Keshtgar1, Harry C Ward, Graham S Clayden
1Great Ormond Street Children's Hospital, London WC1N 3JH, UK. ali.keshtgar@ntlworld.com

Insights
Thickened internal anal sphincter (IAS) in children with chronic idiopathic constipation (IC) correlates with symptom severity and rectal size. This thickening may result from chronic fecal presence, leading to hypertrophic changes in the IAS.
Area of Science:
- Pediatric Gastroenterology
- Colorectal Surgery
- Anorectal Physiology
Background:
- Internal anal sphincter (IAS) thickening is noted in chronic idiopathic constipation (IC) and solitary rectal ulcer syndrome (SRUS).
- This thickening has been linked to rectal intussusception and may represent a feature of obstructed megarectum.
Purpose of the Study:
- To investigate the significance of IAS thickening in children with chronic IC.
- To determine the association between IAS thickness and anorectal manometry findings and patient symptoms.
Main Methods:
- Prospective evaluation of 144 children with chronic IC.
- IAS thickness measured by endosonography; anorectal manometry for functional assessment.
- Symptom severity assessed using a validated symptom score (SS).
Main Results:
- IAS thickness significantly correlated with total symptom severity score (r=0.31, p=0.0001), soiling score (r=0.28, p=0.001), and megarectum size (r=0.36, p=0.0001).
- A significant correlation was found between IAS thickness and rectal contraction amplitude (r=0.23, p=0.007) and patient age (r=0.55, p=0.0001).
- No correlation was observed between IAS thickness and resting anal sphincter pressure or anal sphincter contraction amplitude.
Conclusions:
- Thickening of the IAS in children with chronic IC is significantly associated with symptom duration and severity, megarectum size, and rectal contraction amplitude.
- The pathogenesis is likely secondary to chronic fecal retention, causing abnormal stimulation and subsequent hypertrophy of the IAS.
- IAS myectomy was performed in 24 children, with histological examination showing smooth muscle fibers and ganglion cells.
Abstract:
Thickening of the internal anal sphincter (IAS) is observed in chronic idiopathic constipation (IC) and solitary rectal ulcer syndrome (SRUS), where it has been correlated with the presence and severity of rectal intussusception. Alternatively, thickened IAS may be a feature of the obstructed megarectum in a similar way to the hypertrophy of bladder neck seen in dyssynergic bladders. The aim of this study was to investigate the significance of thickening of the IAS in children with chronic IC and to determine any association between the thickened IAS and anorectal manometry findings and patient's symptoms. A total of 144 children were admitted for investigations and treatment of chronic IC and evaluated prospectively between April 2001 and April 2003. IAS thickness was measured by endosonography using B&K axial endosonic probe type 1850 with a 10-MHz rotating transducer. The thickness of IAS was measured at 3, 6, and 9 o'clock, and the mean value of the three measurements was used for analysis. Functional assessment was done by anorectal manometry pressure studies under ketamine anaesthesia. A validated symptom score (SS) was used to assess the severity of symptoms. The sum of SS ranged between 0 and 65. Spearman's rho two-tailed test was used to correlate the thickness of IAS with patients' symptoms and anorectal manometry findings. Results were expressed as median and range and p-value of less than 0.05 was considered significant. Of 144 children, 84 were boys, median age 8.1 years (range 3.1-15). Soiling was present in 137 (94%) patients, delay in defecation in 132 (91%), and a palpable megarectum on abdominal examination in 117 (80%). The median duration of symptoms and duration of laxative treatment were 4 years (range 0.3-14.5) and 3.3 years (0.2-13.5), respectively. The average severity score for soiling, delay in defecation, palpable megarectum, and the total SS were 8 (range 0-10), 5 (0-10), 2 (0-12), and 33 (11-51), respectively. The median thickness of IAS was 0.9 mm (range 0.3-2.8) and the median resting anal sphincter pressure was 54 mmHg (19-107). The median amplitudes of rectal and anal sphincter contraction were 3 mmHg (1-25) and 9 mmHg (1-35), respectively. The thickness of IAS correlated significantly with total symptom severity score (r=0.31, p=0.0001), soiling score (r=0.28, p=0.001), megarectum score on abdominal palpation (r=0.29, p=0.001), size of megarectum on manometry (r=0.36, p=0.0001), amplitude of rectal contraction (r=0.23, p=0.007), and age of patient (r=0.55, p=0.0001). There was also a significant correlation between the amplitude of rectal and anal sphincter contraction (r=0.32, p=0.0001). There was no correlation between thickness of IAS and resting anal sphincter pressure and amplitude of anal sphincter contraction on anorectal manometry study. A total of 24 children had myectomy of thickened and overactive IAS in addition to the medical treatment of their chronic IC. The histology examination of myectomy specimen with eosin and haematoxylin staining and histochemical acetylcholine esterase staining showed smooth muscle fibres and ganglion cells. Thickening of IAS correlates significantly with duration and severity of symptoms, size of megarectum, and amplitude of rectal contraction. The pathogenesis is secondary to the continuous presence of faeces in the rectum, resulting in chronic abnormal stimulus to the IAS, which leads to hypertrophic changes in the rectum wall and IAS.
Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
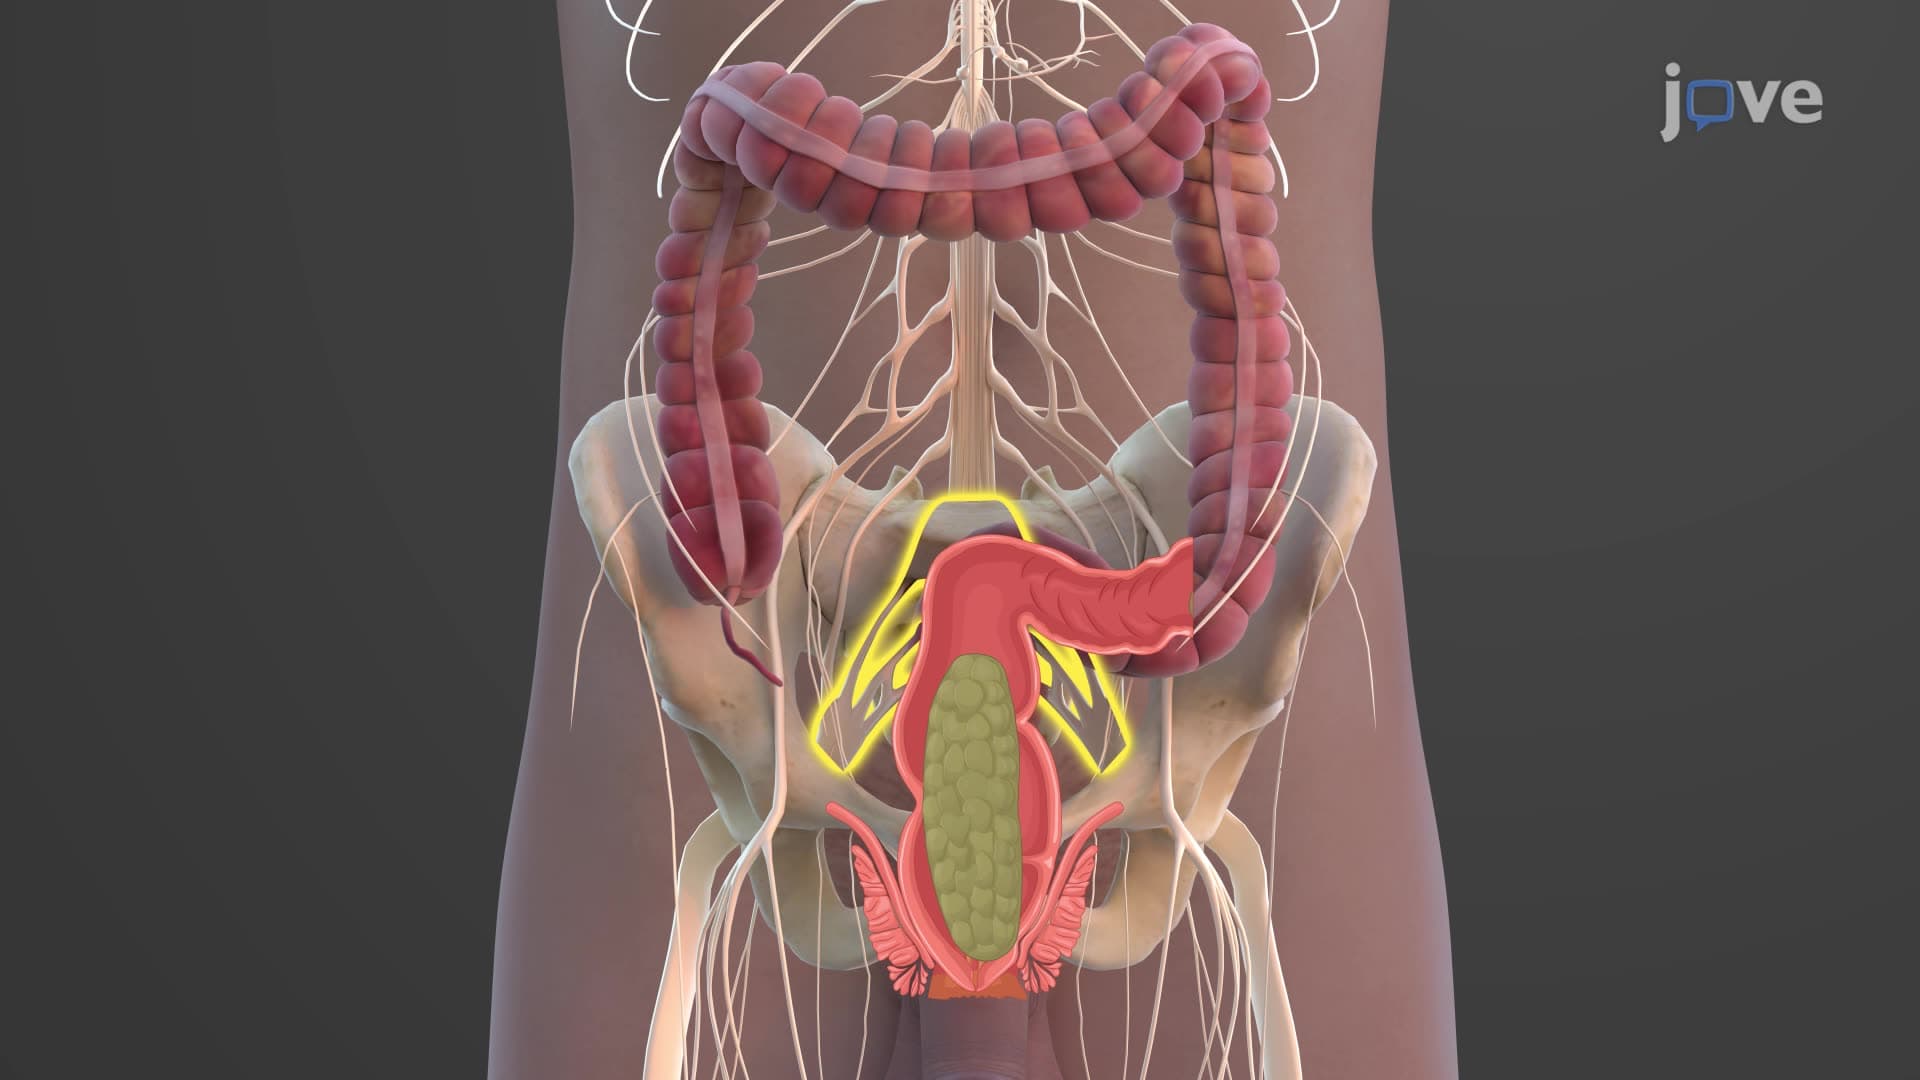
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:07
Intestinal Obstruction II: Pathophysiology
 01:26
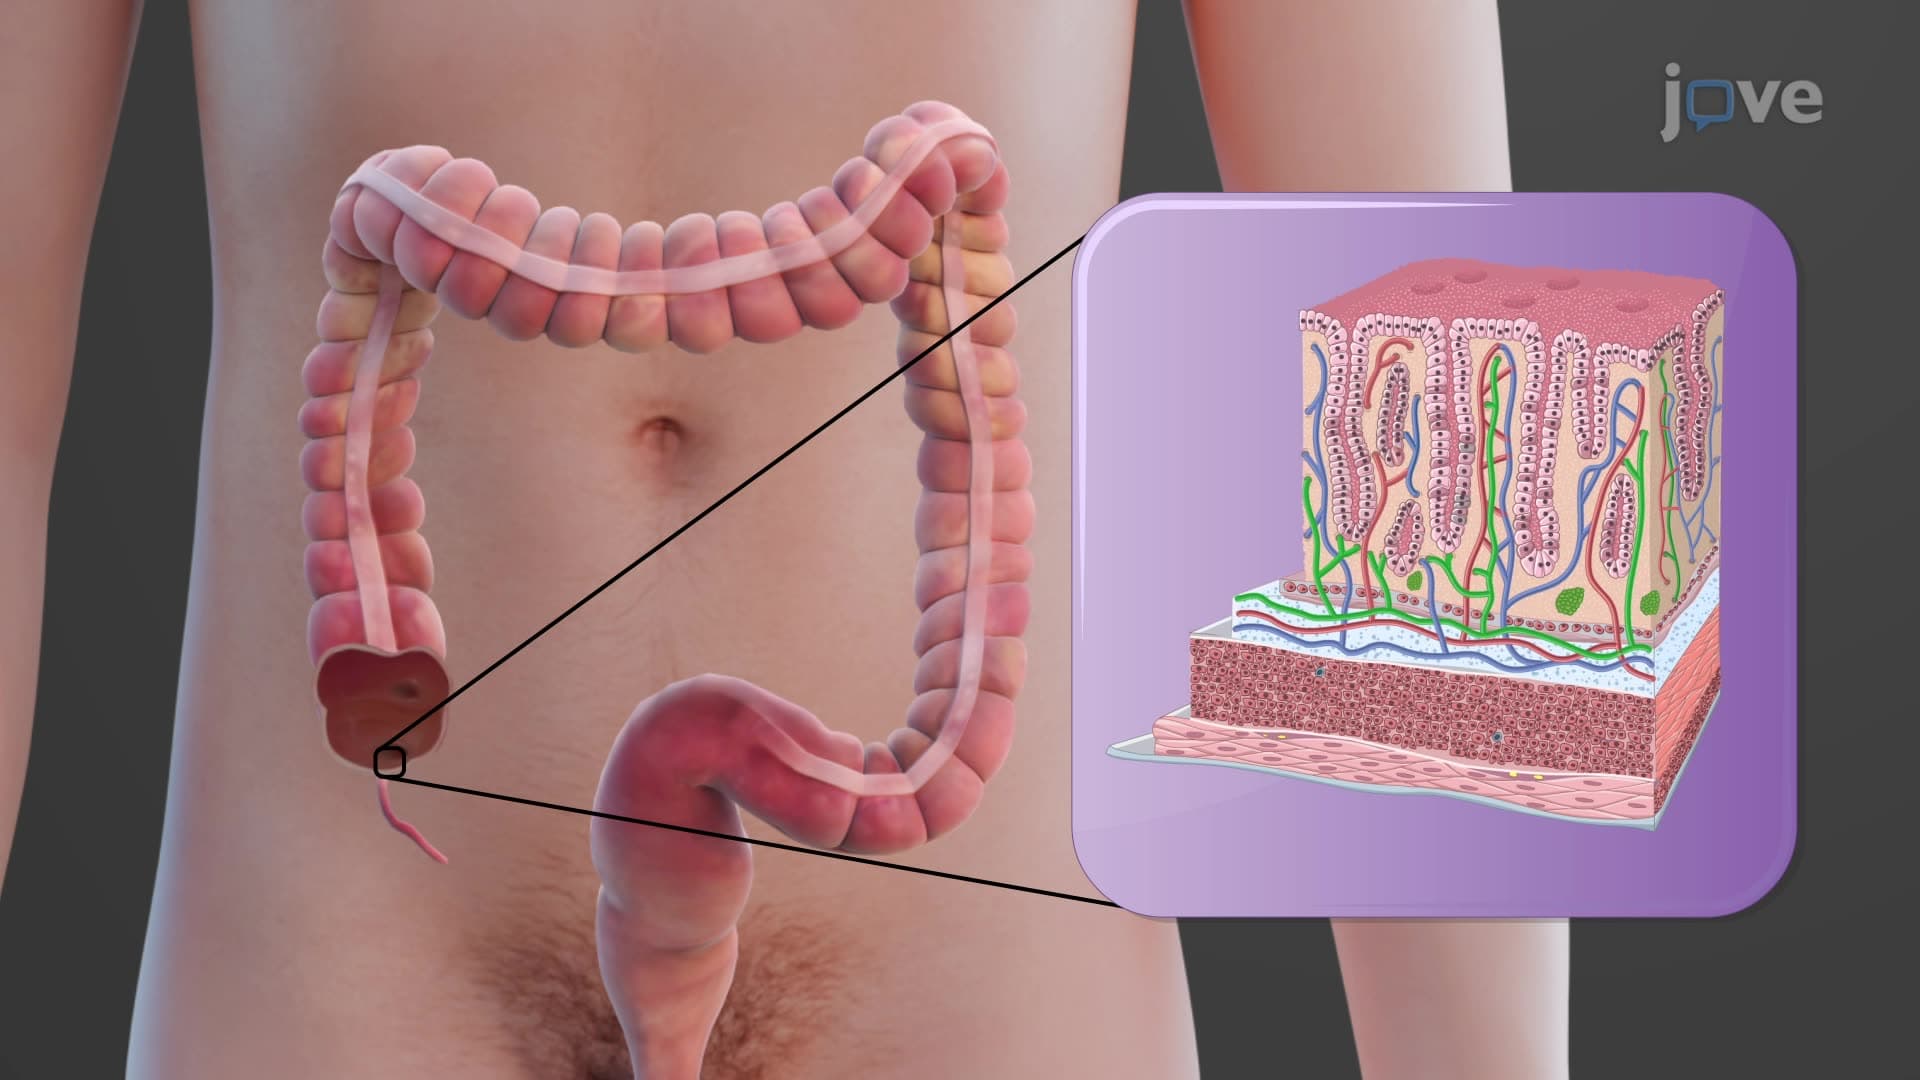
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:27
Diverticular Disease of the Colon