Related Experiment Videos
The clinical relevance of adrenomedullin: a promising profile?
David C Bunton1, Mark C Petrie, Chris Hillier
1Vascular Assessment Unit, Department of Biological and Biomedical Sciences, Glasgow Caledonian University, Cowcaddens Road, Glasgow G4 0BA, UK. d.bunton@gcal.ac.uk

Abstract:
Adrenomedullin (AM) is a peptide that possesses potentially beneficial properties. Since the initial discovery of the peptide by Kitamura et al. in 1993, the literature has been awash with reports describing its novel mechanisms of action and huge potential as a therapeutic target. Strong evidence now exists that AM is able to act as an autocrine, paracrine, or endocrine mediator in a number of biologically significant functions, including the endothelial regulation of blood pressure, protection against organ damage in sepsis or hypoxia, and the control of blood volume through the regulation of thirst. Its early promise as a potential mediator/modulator of disease was not, however, entirely as a result of the discovery of physiological functions but due more to the observation of increasing levels measured in plasma in direct correlation with disease progression. In health, AM circulates at low picomolar concentrations in plasma in 2 forms, a mature 52-amino acid peptide and an immature 53-amino acid peptide. Plasma levels of AM have now been shown to be increased in a number of pathological states, including congestive heart failure, sepsis, essential hypertension, acute myocardial infarction, and renal impairment. These earliest associations have been further supplemented with evidence of a role for AM in other pathologies including, most intriguingly, cancer. In this review, we offer a timely review of our current knowledge on AM and give a detailed account of the putative role of AM in those clinical areas in which the best therapeutic opportunities might exist.
Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:18
Adrenergic Agonists: Therapeutic Classification
Vasopressor or pressor agents: They increase blood pressure and function as cardiac stimulants. Examples include endogenous catecholamines (norepinephrine and dopamine) and synthetic agents (phenylephrine).
Bronchodilators: β2-agonists can relax bronchial muscles and widen airways. They are commonly used for treating obstructive pulmonary...
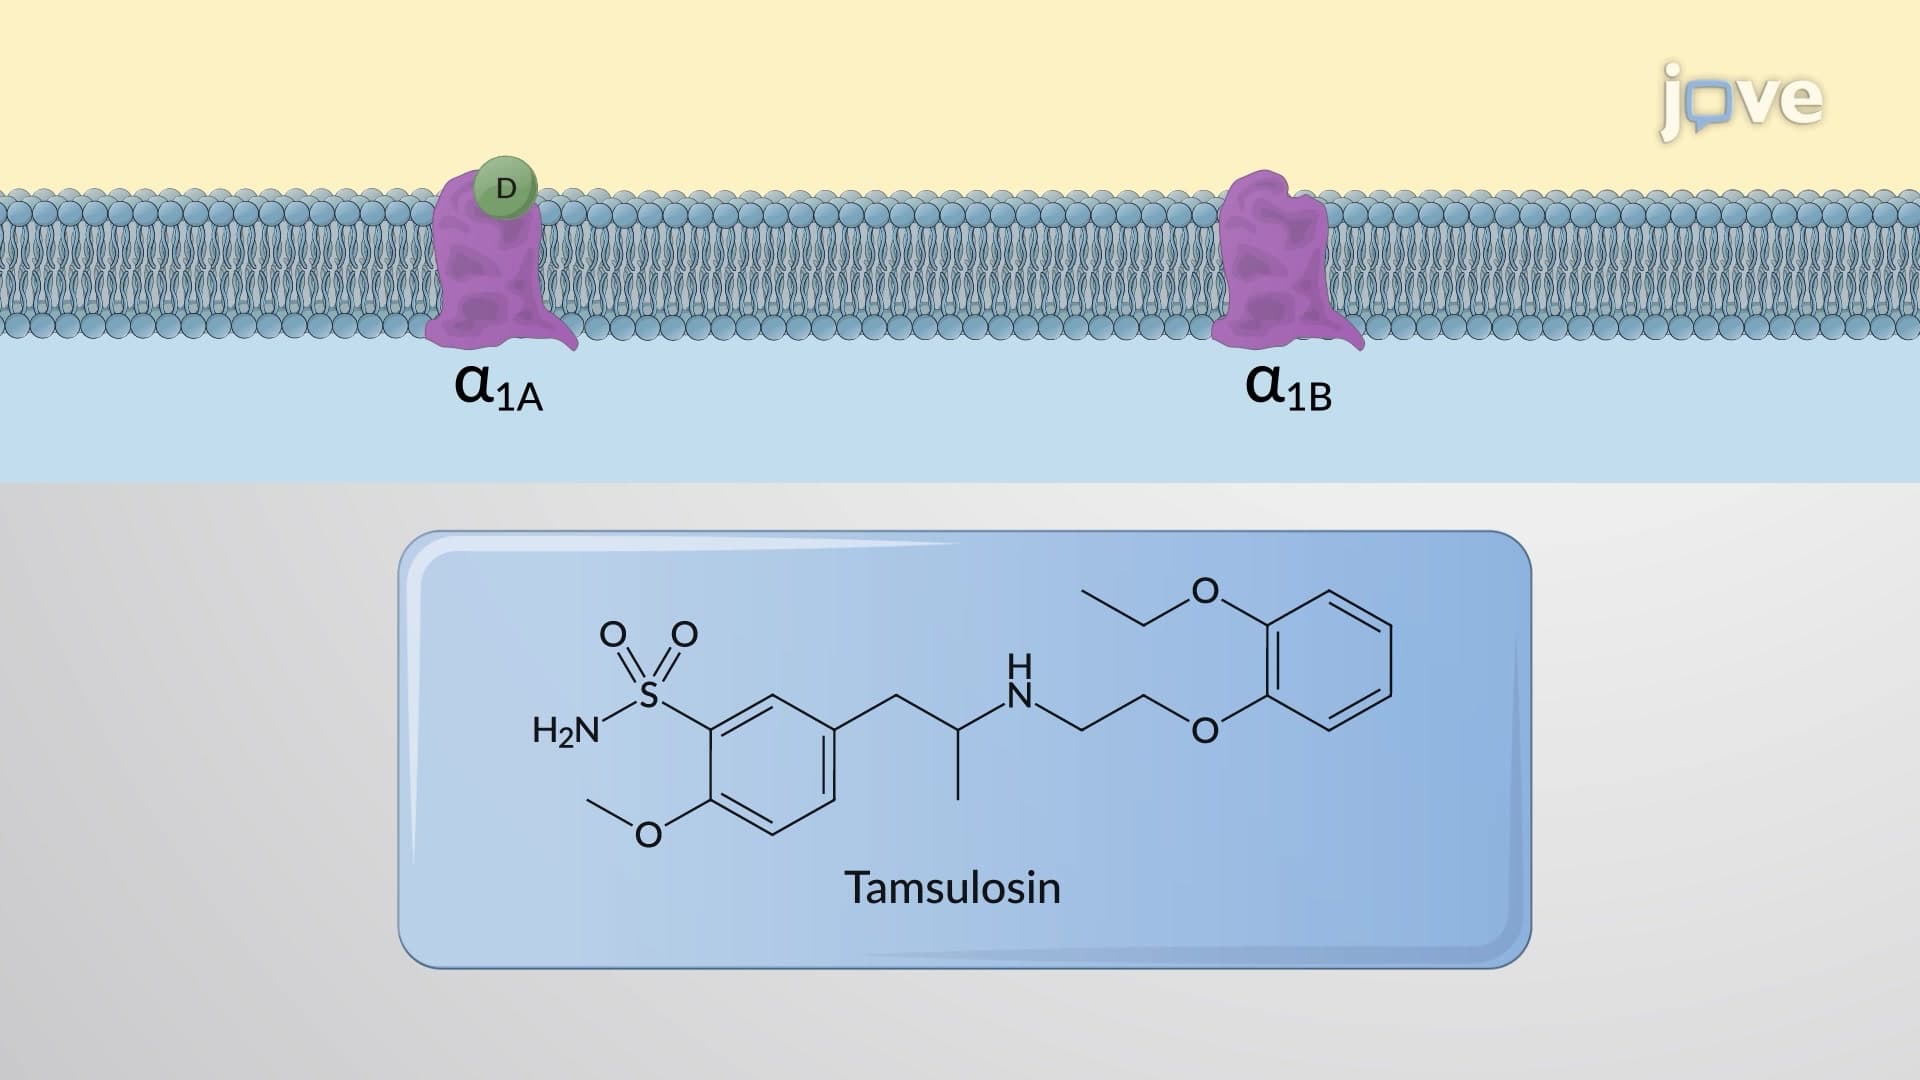 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:26
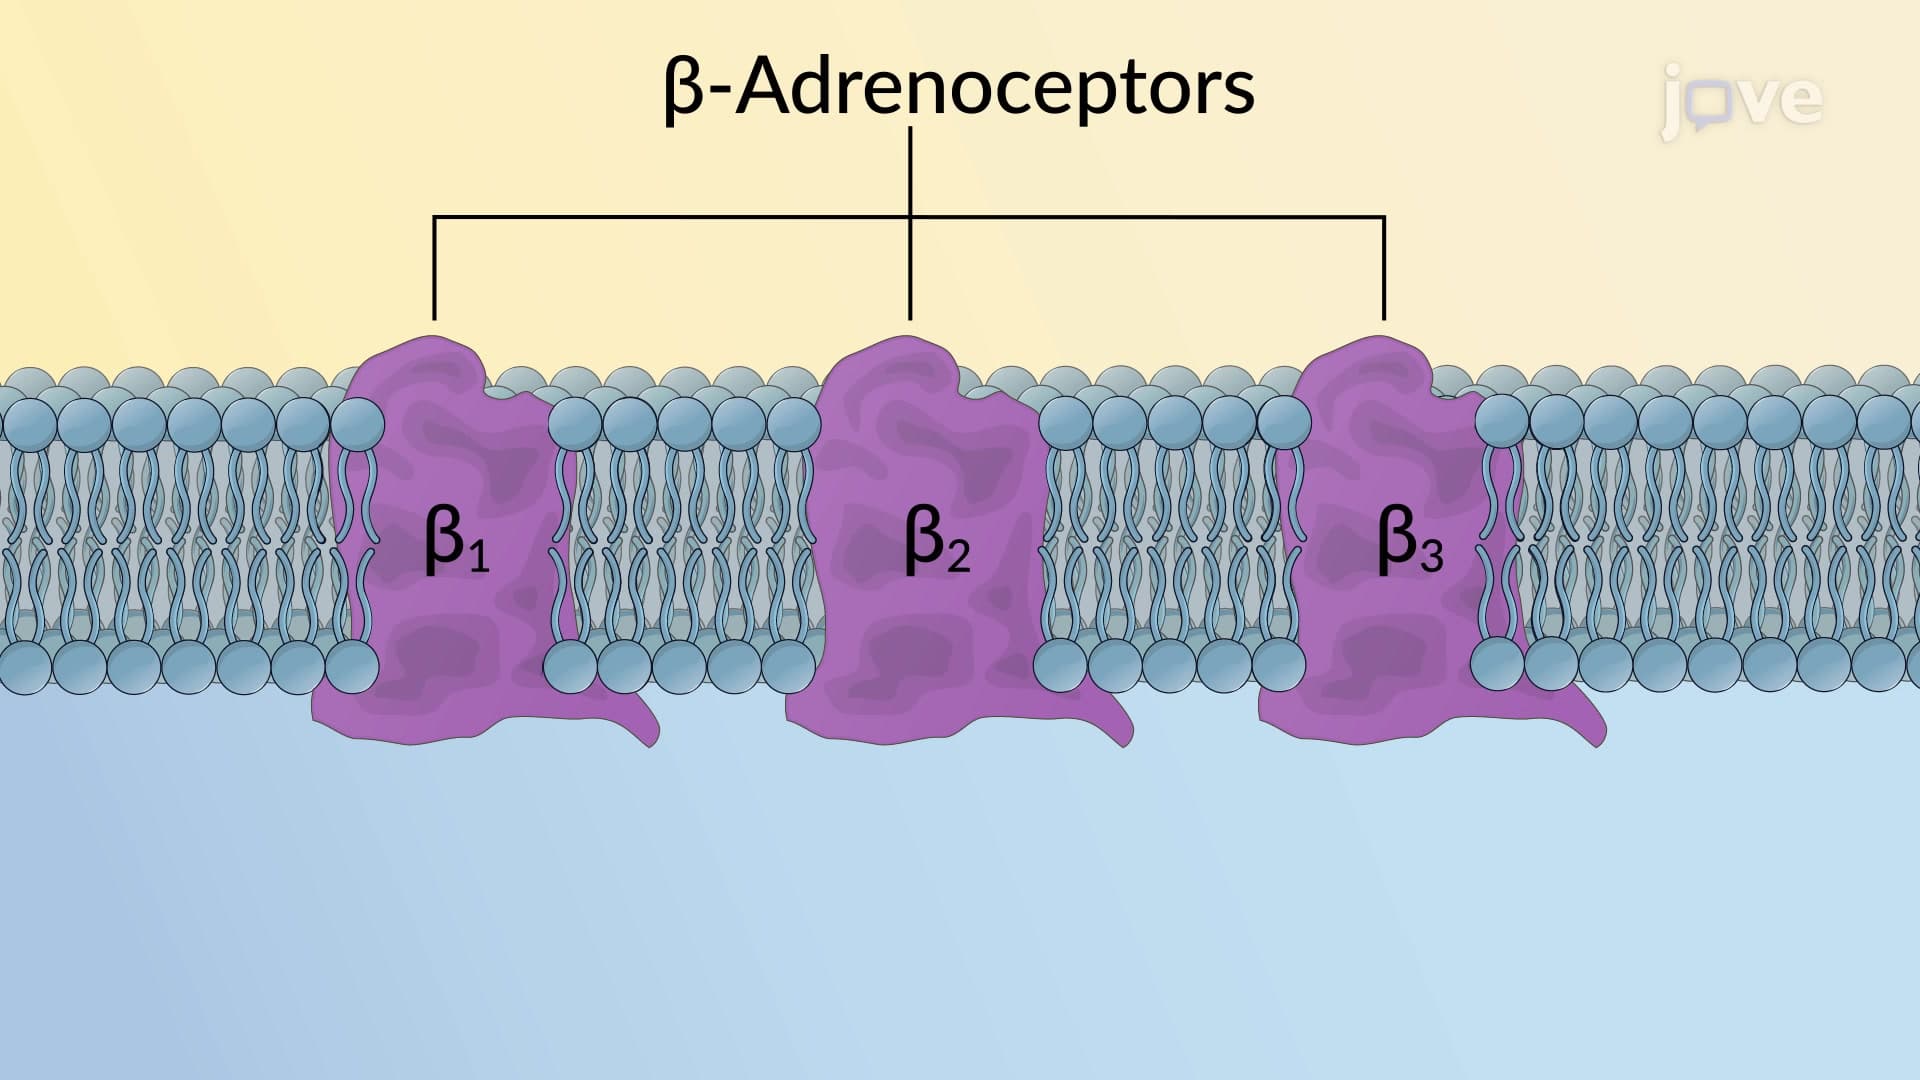
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...