Related Experiment Video
Updated: Aug 21, 2026

Murine Isolated Heart Model of Myocardial Stunning Associated with Cardioplegic Arrest
Published on: August 6, 2015
Postischemic stunning after adenosine vasodilator stress
Regina S Druz1, Olakunle A Akinboboye, Roger Grimson
1The Heart Center, Cardiac Imaging Research Group, Saint Francis Hospital, Roslyn, NY 11576-1348, USA. rdruzmd@aol.com

Insights
Myocardial stunning, a form of ischemia, can occur after adenosine stress testing, even in patients without coronary artery disease. This dysfunction was observed in one third of patients with severe reversible perfusion defects.
Area of Science:
- Cardiology
- Nuclear Cardiology
- Cardiovascular Imaging
Background:
- Ischemic left ventricular (LV) dysfunction is uncommon after vasodilator stress.
- Adenosine stress is generally considered less likely to induce ischemia than exercise stress.
Purpose of the Study:
- To evaluate the prevalence of LV dysfunction after adenosine stress.
- To correlate LV dysfunction with reversible perfusion defects and coronary artery disease (CAD).
Main Methods:
- 86 patients underwent adenosine dual-isotope gated single-photon emission computed tomography.
- Patients were categorized into groups based on reversible perfusion defects or absence of CAD.
- Left ventricular ejection fraction, volumes, and wall thickening were quantified using QGS.
Main Results:
- 32% of patients with extensive reversible perfusion defects (summed difference score >= 8) showed depressed post-adenosine LV ejection fraction.
- These patients also exhibited abnormal segmental wall thickening and end-systolic dilation.
- Extensive coronary artery disease was confirmed in these individuals.
Conclusions:
- Myocardial stunning, indicated by LV dysfunction, occurred in one third of patients with severe reversible perfusion defects after adenosine stress.
- This finding is consistent with exercise-induced ischemia, challenging the notion that vasodilator stress is less likely to cause ischemia.
Background:
Ischemic left ventricular (LV) dysfunction may occur after exercise but is regarded as uncommon after vasodilator stress. We evaluated the prevalence of LV dysfunction after adenosine stress in relation to reversible perfusion defects and angiographic coronary artery disease (CAD).
Methods And Results:
We studied 86 patients referred for clinically indicated adenosine dual-isotope gated single photon emission computed tomography: 43 with 1 or more reversible perfusion defects (reversible defect group) and 43 age- and sex-matched patients with no known CAD and normal LV perfusion and function (control group). Coronary angiography was performed in 36 of 43 patients (84%) in the reversible defect group. Perfusion was interpreted based on 20-segment/5-point summed rest and stress scores. The extent of reversibility was defined by the summed difference score. LV ejection fraction and volumes at rest and 60 minutes after adenosine and segmental wall thickening were quantified by QGS (Cedars-Sinai Medical Center, Los Angeles, Calif). In patients with extensive reversible perfusion defects (summed difference score > or =8), 8 of 25 (32%) demonstrated depressed post-adenosine LV ejection fraction, abnormal segmental wall thickening, end-systolic dilation, and extensive CAD.
Conclusion:
Adenosine is believed to be less likely than exercise to induce ischemia. However, myocardial stunning occurred in one third of the patients with severe reversible defects, consistent with ischemia.

Related Concept Videos
 01:26
Exercise Stress Test
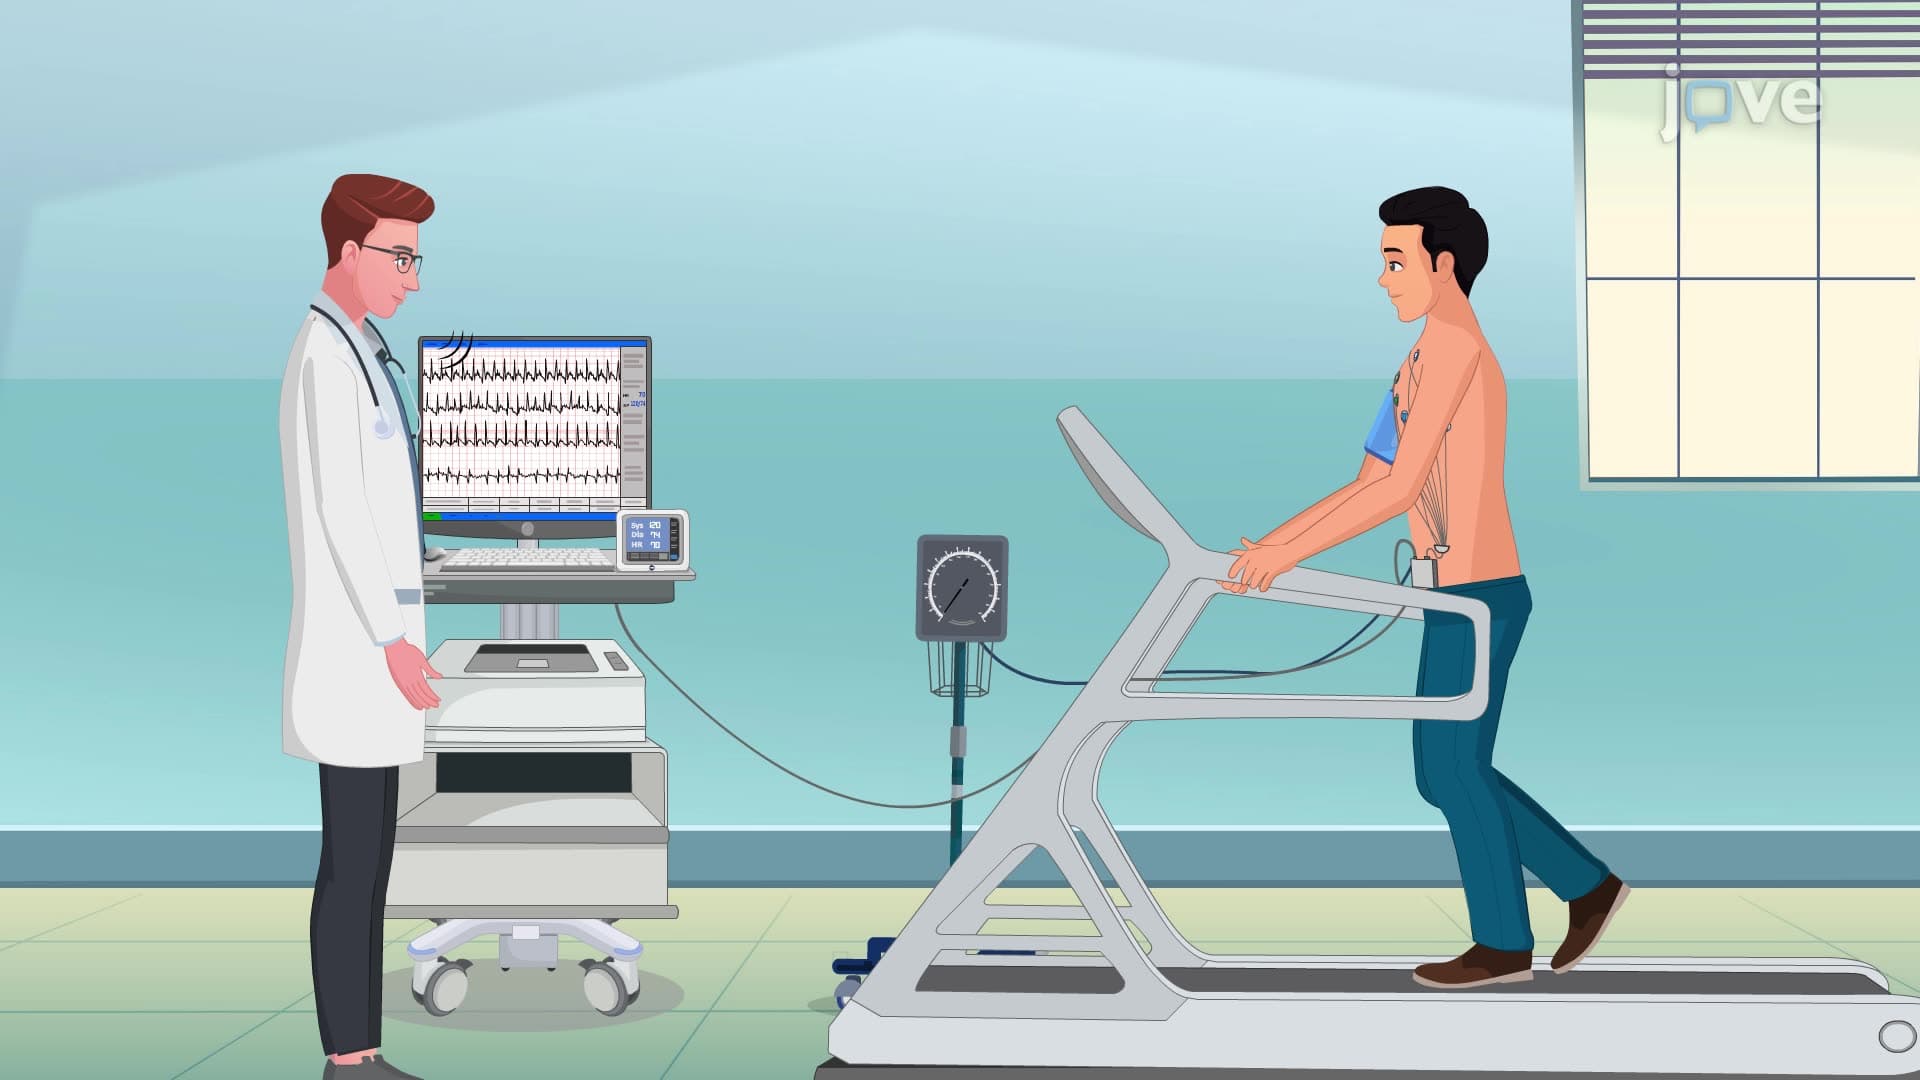
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management