Low exhaled nitric oxide in school-age children with bronchopulmonary dysplasia and airflow limitation
Related Experiment Video
Updated: Aug 8, 2026
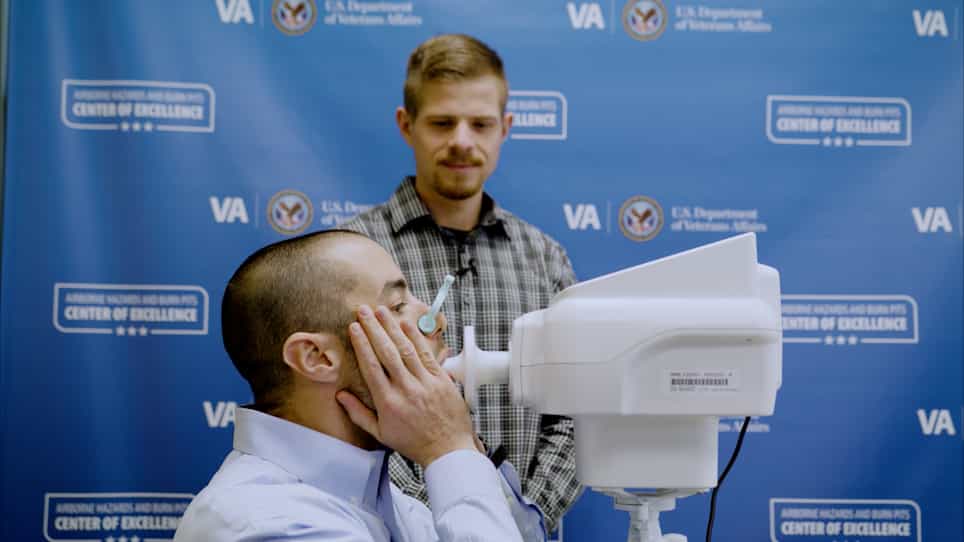
Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Eugenio Baraldi1, Gea Bonetto, Franco Zacchello
1Department of Pediatrics, School of Medicine, University of Padova, Via Giustiniani 3, 35128 Padova, Italy. baraldi@pediatria.unipd.it

Insights
School-age survivors of bronchopulmonary dysplasia (BPD) exhibit persistent airflow limitation. Unlike asthma patients, these children show low exhaled nitric oxide (FeNO) levels and no response to beta(2)-agonists, suggesting unique airway pathology.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Neonatology
Background:
- Bronchopulmonary dysplasia (BPD) is a chronic lung disease in premature infants.
- BPD survivors may experience long-term airflow limitation and asthma-like symptoms.
- The underlying pathological mechanisms of these respiratory issues remain unclear.
Purpose of the Study:
- To investigate exhaled nitric oxide (FeNO) levels and lung function in school-age survivors of BPD.
- To compare respiratory parameters in BPD survivors with healthy controls and children with asthma.
Main Methods:
- Measured FeNO and performed lung function tests (including FEV1) in 31 school-age BPD survivors.
- Compared results with healthy term-born controls, preterm children without BPD, and 31 children with asthma.
Main Results:
- BPD survivors displayed airflow obstruction (mean FEV1 77.8% predicted), unresponsive to beta(2)-agonists in 72%.
- FeNO levels in BPD survivors (7.7 ppb) were significantly lower than in healthy controls (10.7 ppb) and preterm children without BPD (9.9 ppb).
- BPD survivors had FeNO levels four times lower than children with comparable airflow limitation due to asthma (24.9 ppb).
Conclusions:
- School-age BPD survivors exhibit airflow limitation with low FeNO and lack of bronchodilator reversibility.
- These findings differ from asthma and suggest airway pathology related to early-life structural changes in BPD.
- Low FeNO may indicate distinct inflammatory or structural pathways in BPD-related chronic lung disease.
Abstract:
Bronchopulmonary dysplasia (BPD), the chronic lung disease of prematurity, may be associated with long-term airflow limitation. Survivors of BPD may develop asthma-like symptoms in childhood, with a variable response to beta(2)-agonists. However, the pathologic pathways underlying these respiratory manifestations are still unknown. The aim of this study was to measure exhaled nitric oxide (FE(NO)) and lung function in a group of 31 school-age survivors of BPD. They showed variable degrees of airflow obstruction (mean FEV(1) 77.8 +/- 2.3% predicted) unresponsive to beta(2)-agonists in 72% of the subjects. Their FE(NO) values (geometric mean [95% confidence interval]: 7.7 [+/- 1.1] ppb) were significantly lower than in a group of healthy matched control subjects born at term (10.7 [+/- 1.1] ppb, p < 0.05) and a group of preterm children without BPD (9.9 [+/- 1.1] ppb, p < 0.05). The children with BPD were also compared with a group of 31 patients with asthma with a comparable airflow limitation (FEV(1) 80.2 +/- 2.1% predicted) and showed FE(NO) values four times lower than in those with asthma (24.9 [+/- 1.2] ppb, p < 0.001). In conclusion, unlike children with asthma, school-age survivors of BPD have airflow limitation associated with low FE(NO) values and lack of reversibility to beta(2)-agonists, probably as a result of mechanisms related to early life structural changes in the airways.

Related Concept Videos
 01:05
Breathing
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:17
Pulmonary Cycle: Exhalation
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
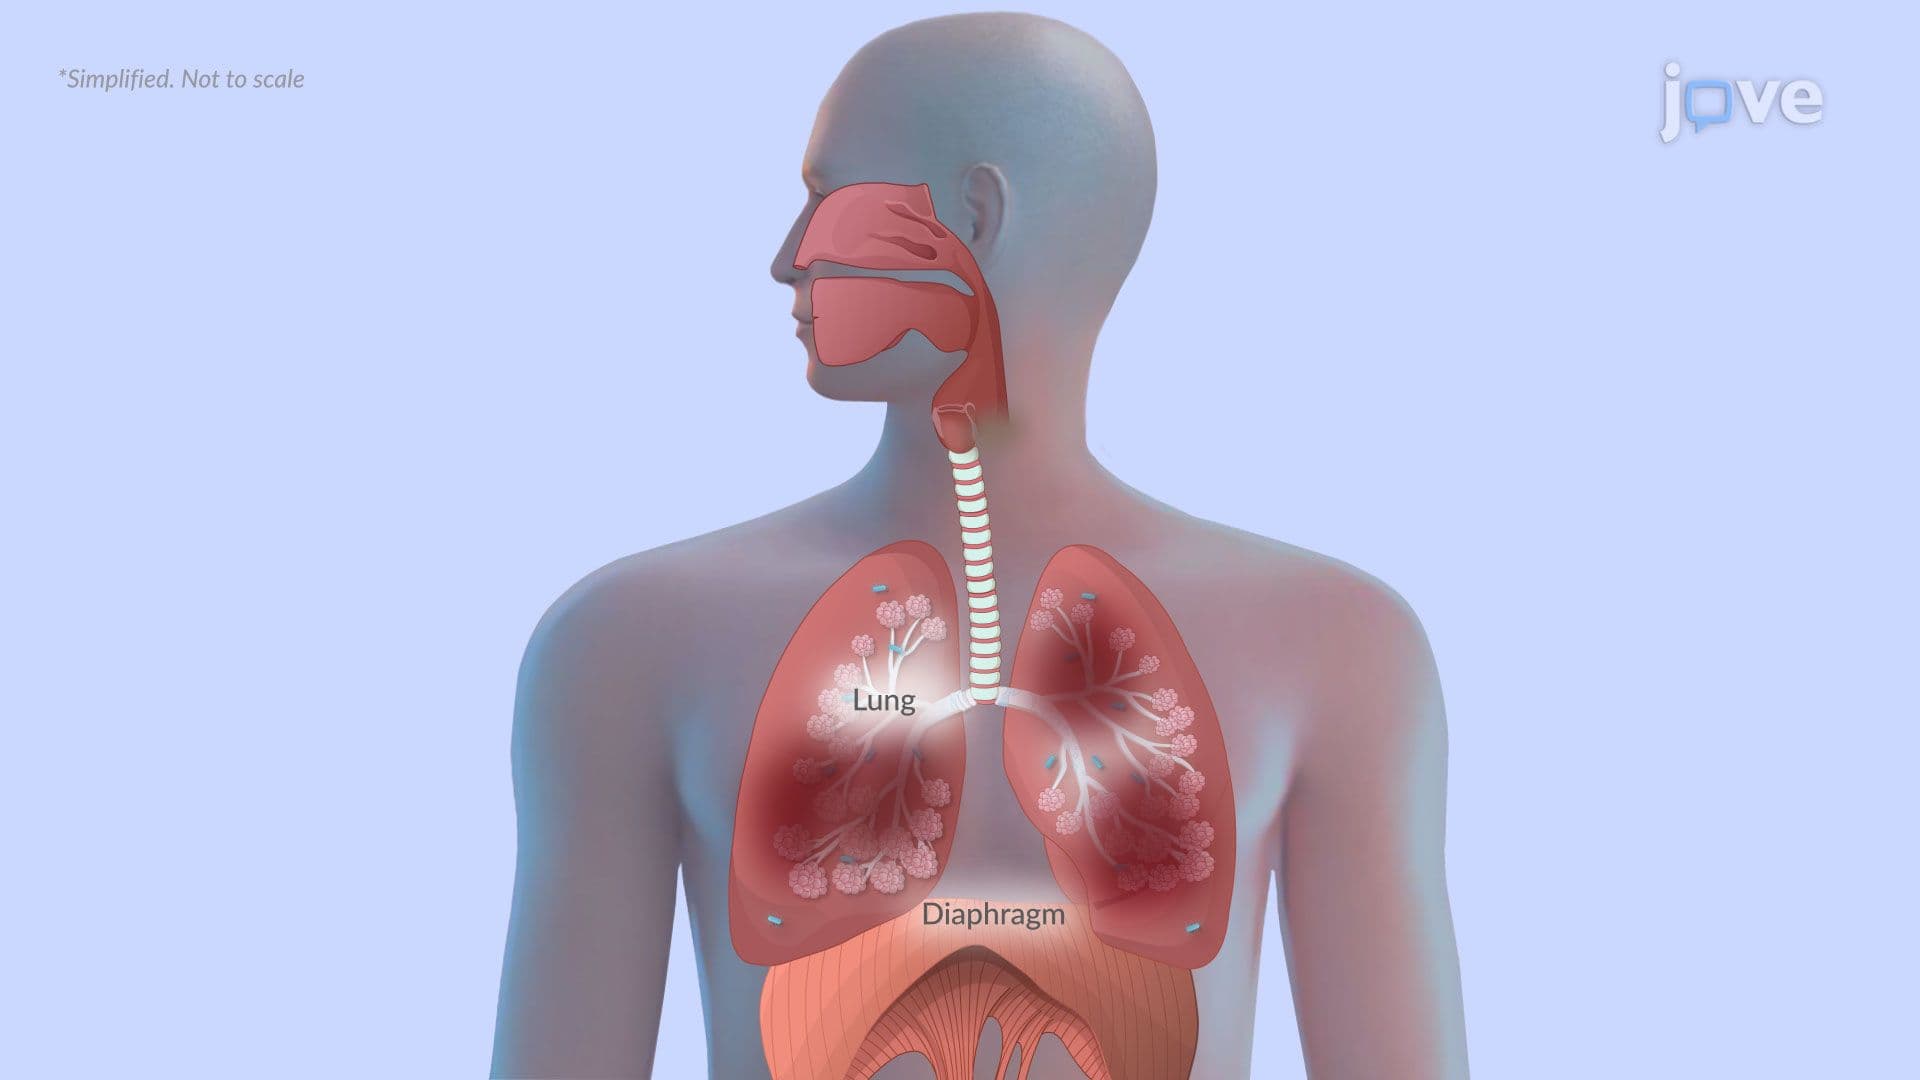
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features