Related Experiment Video
Updated: Jun 1, 2026


Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
[Water-electrolyte and endocrine disorders after craniopharyngomectomy in a child]

Insights
This study details a child
Area of Science:
- Pediatric Endocrinology
- Neurosurgery
- Intensive Care Medicine
Background:
- Craniopharyngioma removal can lead to complex endocrine and neurological complications.
- Syndrome of Inadequate Secretion of Antidiuretic Hormone (SIADH) is a potential post-operative risk.
Observation:
- A child developed a three-phase course of diabetes insipidus with SIADH post-craniopharyngioma surgery.
- Clinical status correlated with cerebral blood flow, hormonal levels, and homeostatic changes.
Findings:
- SIADH presented with impaired consciousness, seizures, and widespread edema, including pulmonary edema.
- Progressive adrenal and thyroid insufficiency occurred concurrently with SIADH.
Implications:
- Management of SIADH requires intensive care, especially when associated with polyhormonal deficiency and edema.
- Understanding these complications is crucial for post-operative neurosurgical and endocrine care in children.
Abstract:
The paper considers a type of three-phase course of diabetes insipidus with the development of the syndrome of inadequate secretion of antidiuretic hormone (SIADH) in a child after radical removal of endosupracellar craniopharyngoma. The parameters of cerebral blood flow, homeostatic fluctuations, the blood levels of thyroid hormones were compared with the time course of changes in the patient's clinical status. SIADH was accompanied by impaired consciousness, convulsion, developed common edematous syndrome, including interstitial edema of the lung, progressive suprarenal and thyroid insufficiency. The concurrence of SIADH with polyhormonal deficiency and the edematous syndrome determined the lines of intensive care.


Related Concept Videos
 01:29
Disorder of Water Balance
Dehydration
Dehydration occurs when the body loses fluids (particularly water).
Causes:
The major causes of dehydration include excessive sweating, fever, vomiting, diarrhea, and diuresis.
Signs and Symptoms:
Symptoms primarily include intense...
 01:22
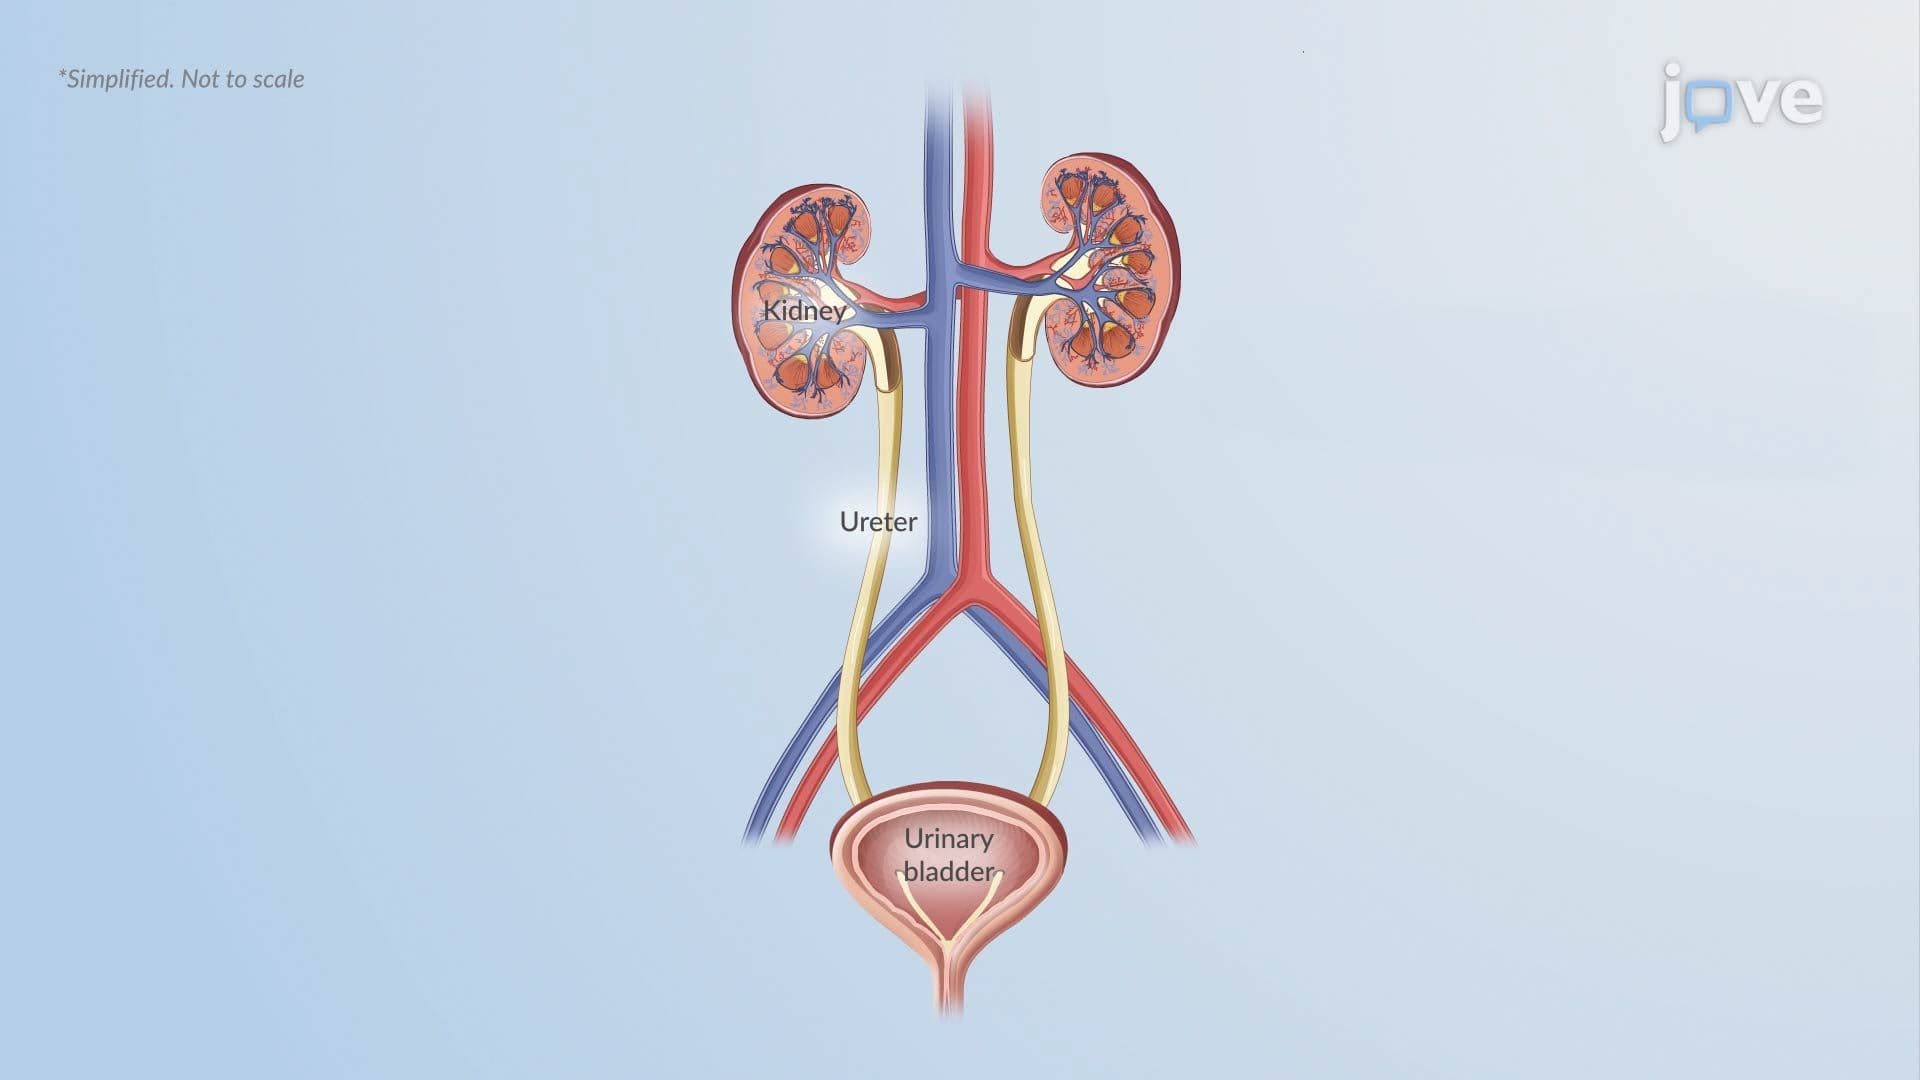
Diabetes Insipidus II: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:19
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:21
Cytotoxic Edema: Pathophysiology