Related Experiment Video
Updated: Aug 21, 2026


Metabolic Profiling to Determine Bactericidal or Bacteriostatic Effects of New Natural Products using Isothermal Microcalorimetry
Published on: October 29, 2020
Pharmacokinetics of oral ciprofloxacin in continuous cycling peritoneal dialysis
Sharon M Yeung1, Scott E Walker, Sandra A N Tailor
1Department of Pharmacy, Sunnybrook & Women's College Health Sciences Centre, Toronto, Ontario, Canada. yeungs@smh.toronto.on.ca

Background:
In order to avoid aminoglycosides, the International Society for Peritoneal Dialysis recommends cefazolin and ceftazidime for empirical treatment of peritonitis. Ciprofloxacin covers relevant gram-negative pathogens without the resistance associated with ceftazidime. However, ciprofloxacin pharmacokinetic data in patients on continuous cycling peritoneal dialysis (CCPD) are lacking.
Objectives:
(1) To determine the pharmacokinetics of oral ciprofloxacin in CCPD patients, (2) to compare serum and dialysate ciprofloxacin concentrations with minimum inhibitory concentrations (MIC) of the gram-negative bacteria associated with peritonitis, and (3) to establish oral ciprofloxacin dosing guidelines for the empirical treatment of peritonitis in patients receiving CCPD.
Methods:
Eligible CCPD patients received 2 doses of ciprofloxacin: 750 mg orally every 12 hours. Serial blood and end-of-dwell dialysate samples were collected during the first 12-hour interval; an end-of-dwell dialysate sample from the overnight dwell and a final blood sample were collected at the end of the second 12-hour interval. Ciprofloxacin concentrations were determined using a liquid chromatographic (HPLC)-fluorescence method. Pharmacokinetic calculations were completed assuming a one-compartment model.
Results:
Eight patients completed the study. The pharmacokinetic parameters determined for ciprofloxacin were (mean +/- SEM) serum half-life 10.1 +/- 1.2 hours, maximum serum concentration 2.7 +/- 0.5 mg/L, time to maximum serum concentration 1.6 +/- 0.1 hours after the first dose, and peritoneal clearance 1.2% +/- 0.1% of the mean calculated total body clearance. While all patients achieved serum area under the concentration-time curve:MIC > 125 for Escherichia coli and Klebsiella species after the first dose, only 2 patients achieved this goal for Pseudomonas aeruginosa. End-of-dwell dialysate concentrations were above the MIC for E. coli, Klebsiella spp, and P. aeruginosa after the second dose.
Conclusion:
Ciprofloxacin 750 mg orally every 12 hours in CCPD patients may be useful for empirical gram-negative coverage of CCPD peritonitis and for treatment of documented peritonitis caused by sensitive E. coli or Klebsiella species. While ceftazidime may be required for documented pseudomonal peritonitis, the oral ciprofloxacin regimen achieved adequate serum concentrations to treat systemic gram-negative infections caused by sensitive E. coli or Klebsiella species.
Insights
Oral ciprofloxacin at 750 mg every 12 hours shows promise for treating gram-negative peritonitis in continuous cycling peritoneal dialysis (CCPD) patients. This regimen provides adequate serum concentrations for sensitive E. coli and Klebsiella species, but may require additional agents for Pseudomonas aeruginosa.
Area of Science:
- Pharmacokinetics and infectious disease research.
- Clinical pharmacology in renal replacement therapy.
Background:
- International guidelines recommend cefazolin and ceftazidime for peritonitis, but resistance is a concern.
- Ciprofloxacin offers broad gram-negative coverage, but its use in CCPD patients lacks pharmacokinetic data.
Purpose of the Study:
- Determine oral ciprofloxacin pharmacokinetics in CCPD patients.
- Compare drug concentrations to bacterial MICs.
- Establish dosing guidelines for CCPD peritonitis.
Main Methods:
- Eight CCPD patients received 750 mg oral ciprofloxacin every 12 hours.
- Serial blood and dialysate samples were analyzed using HPLC.
- Pharmacokinetic parameters were calculated using a one-compartment model.
Main Results:
- Mean serum half-life was 10.1 hours; time to peak concentration was 1.6 hours.
- Adequate serum concentrations (AUC:MIC > 125) were achieved for E. coli and Klebsiella after the first dose.
- Dialysate concentrations exceeded MICs for E. coli, Klebsiella, and P. aeruginosa after the second dose.
Conclusions:
- Oral ciprofloxacin 750 mg every 12 hours may be effective for empirical gram-negative coverage in CCPD peritonitis.
- The regimen is suitable for treating infections caused by sensitive E. coli or Klebsiella species.
- Ceftazidime might still be necessary for documented Pseudomonas aeruginosa peritonitis.

Related Concept Videos
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...
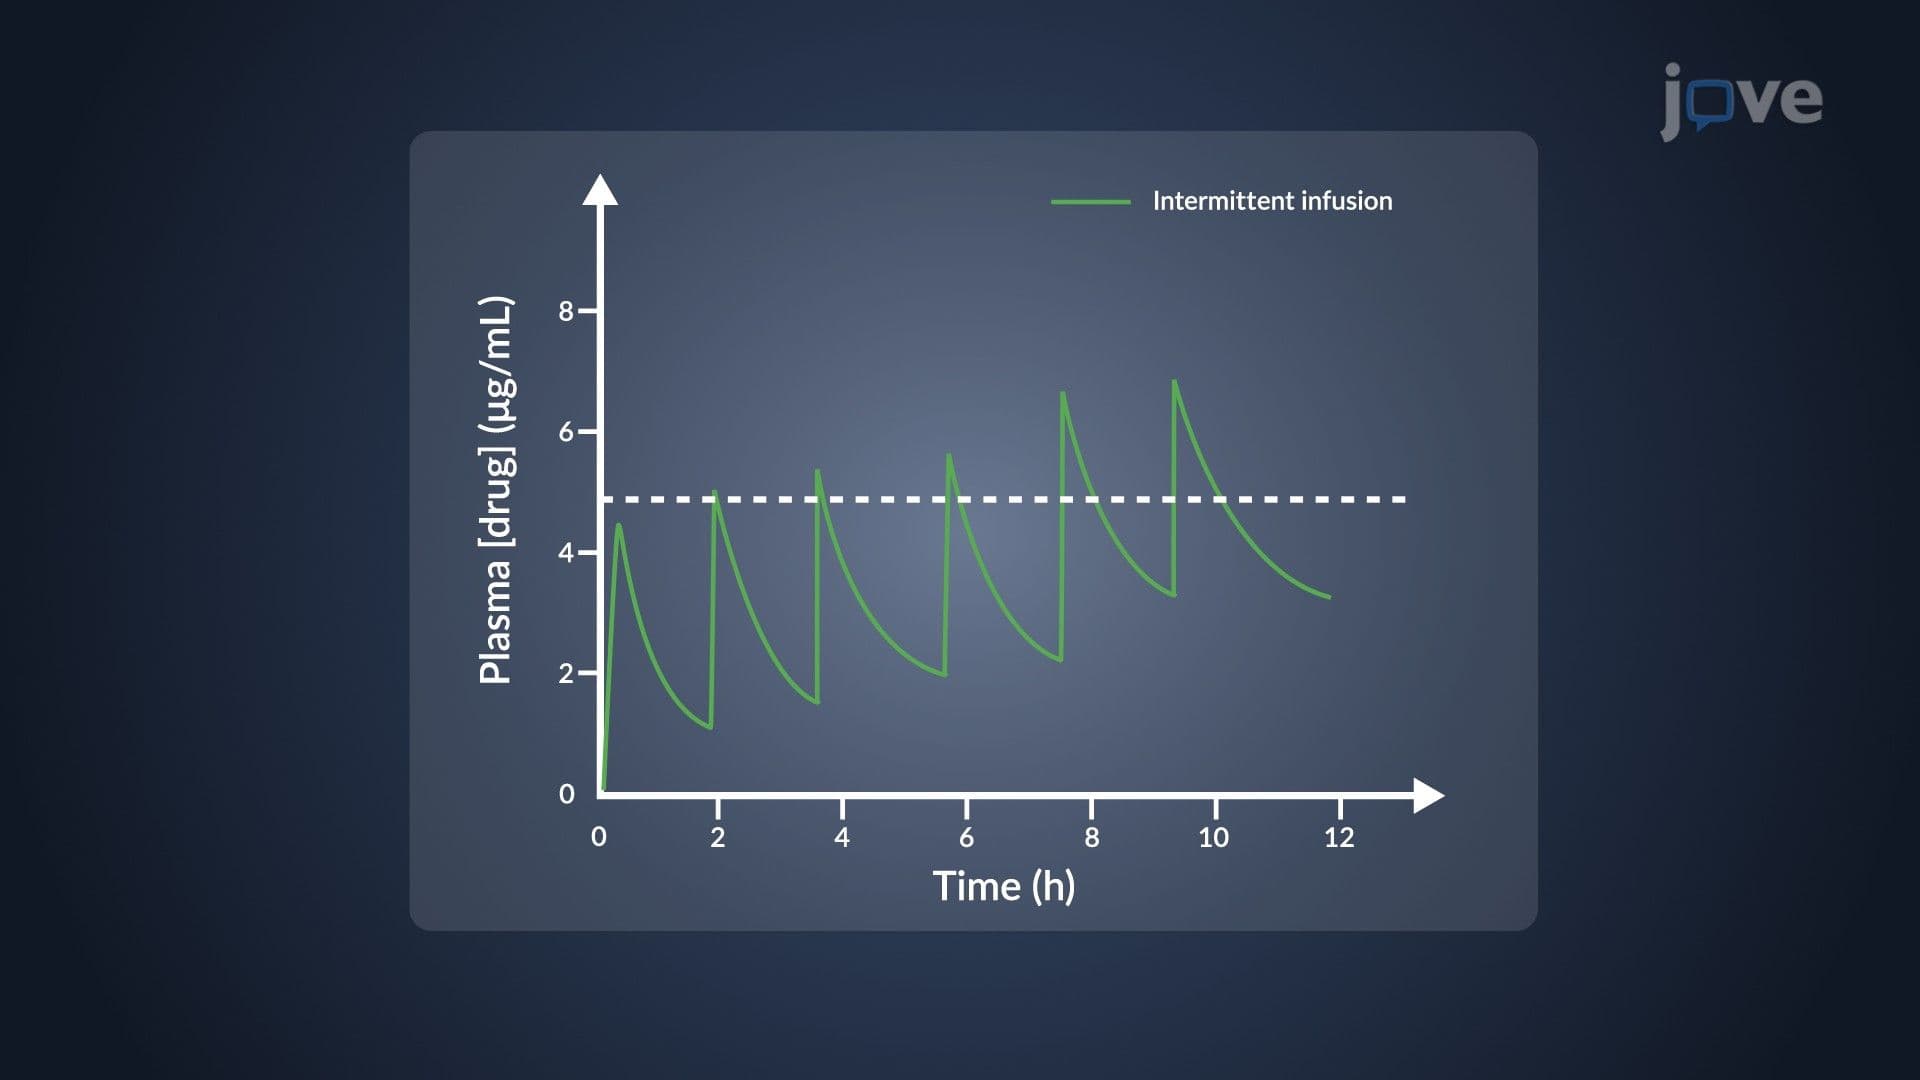 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
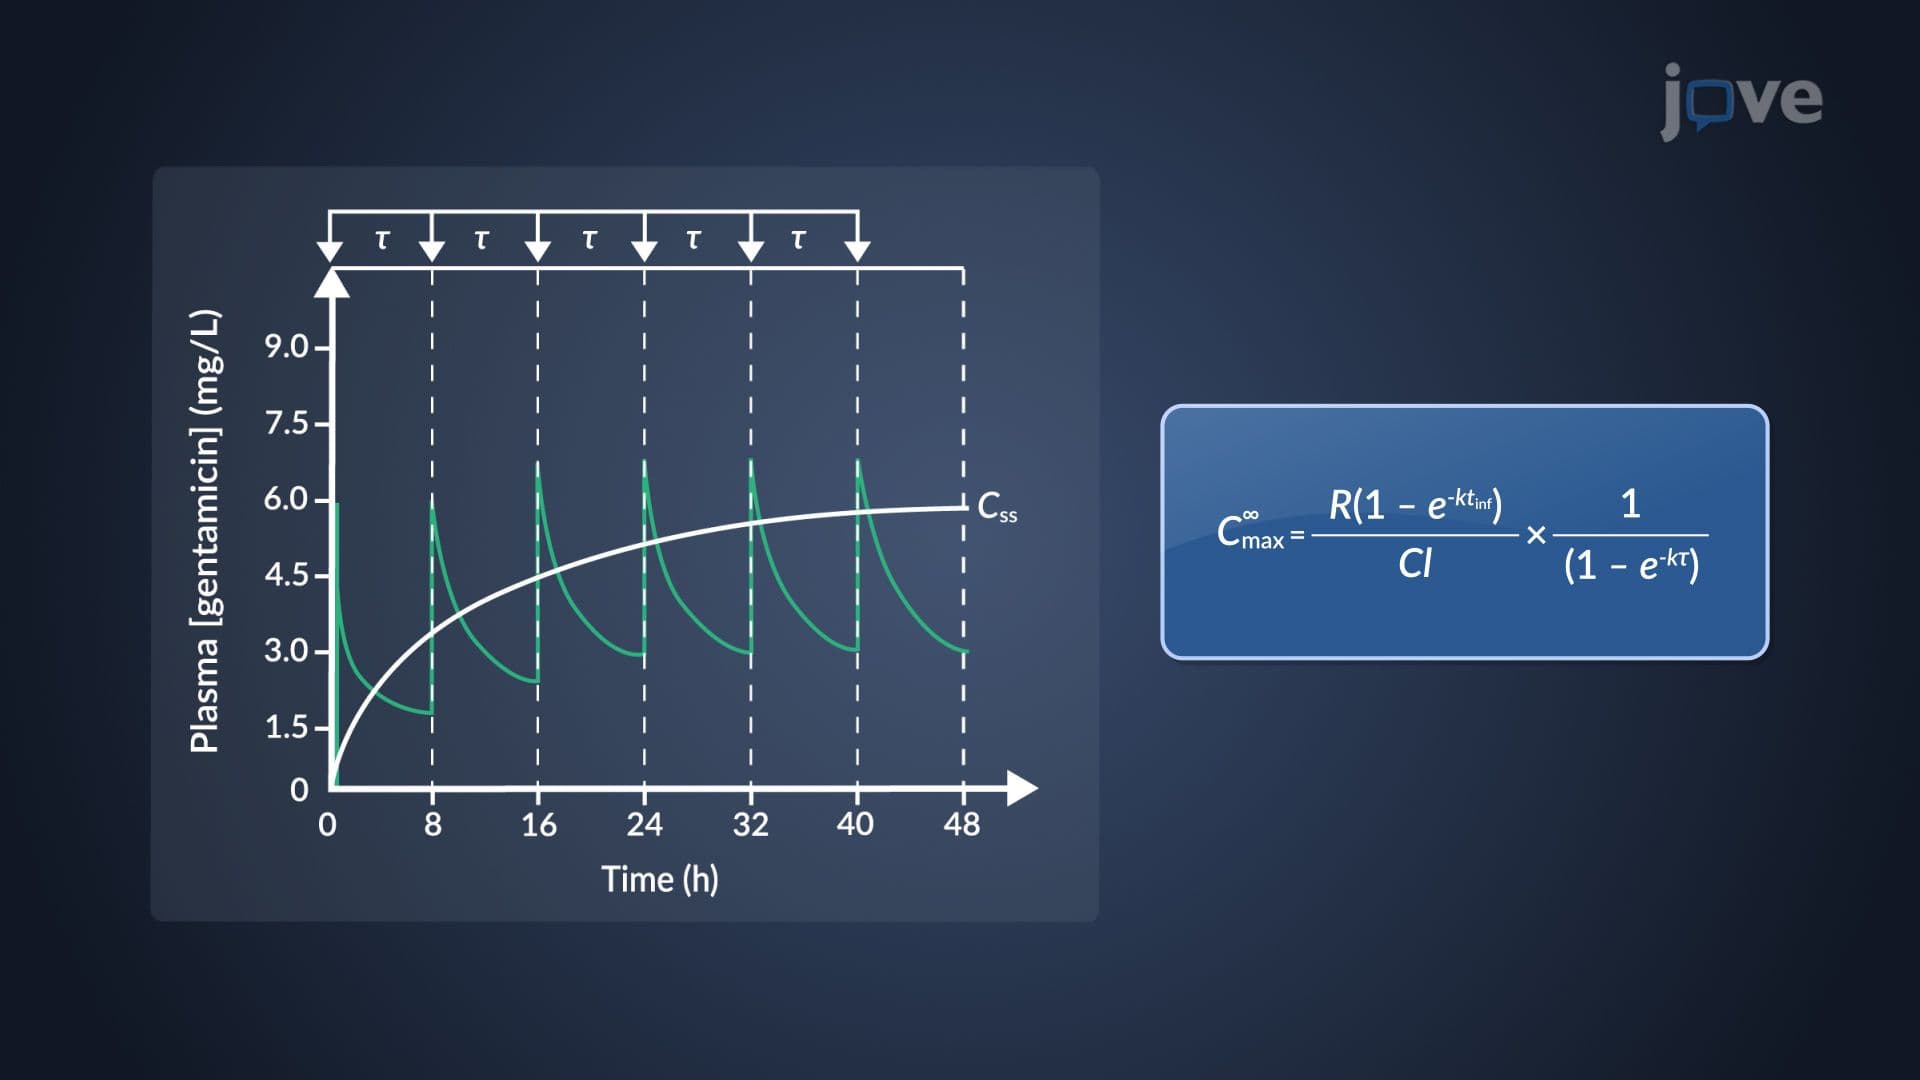 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
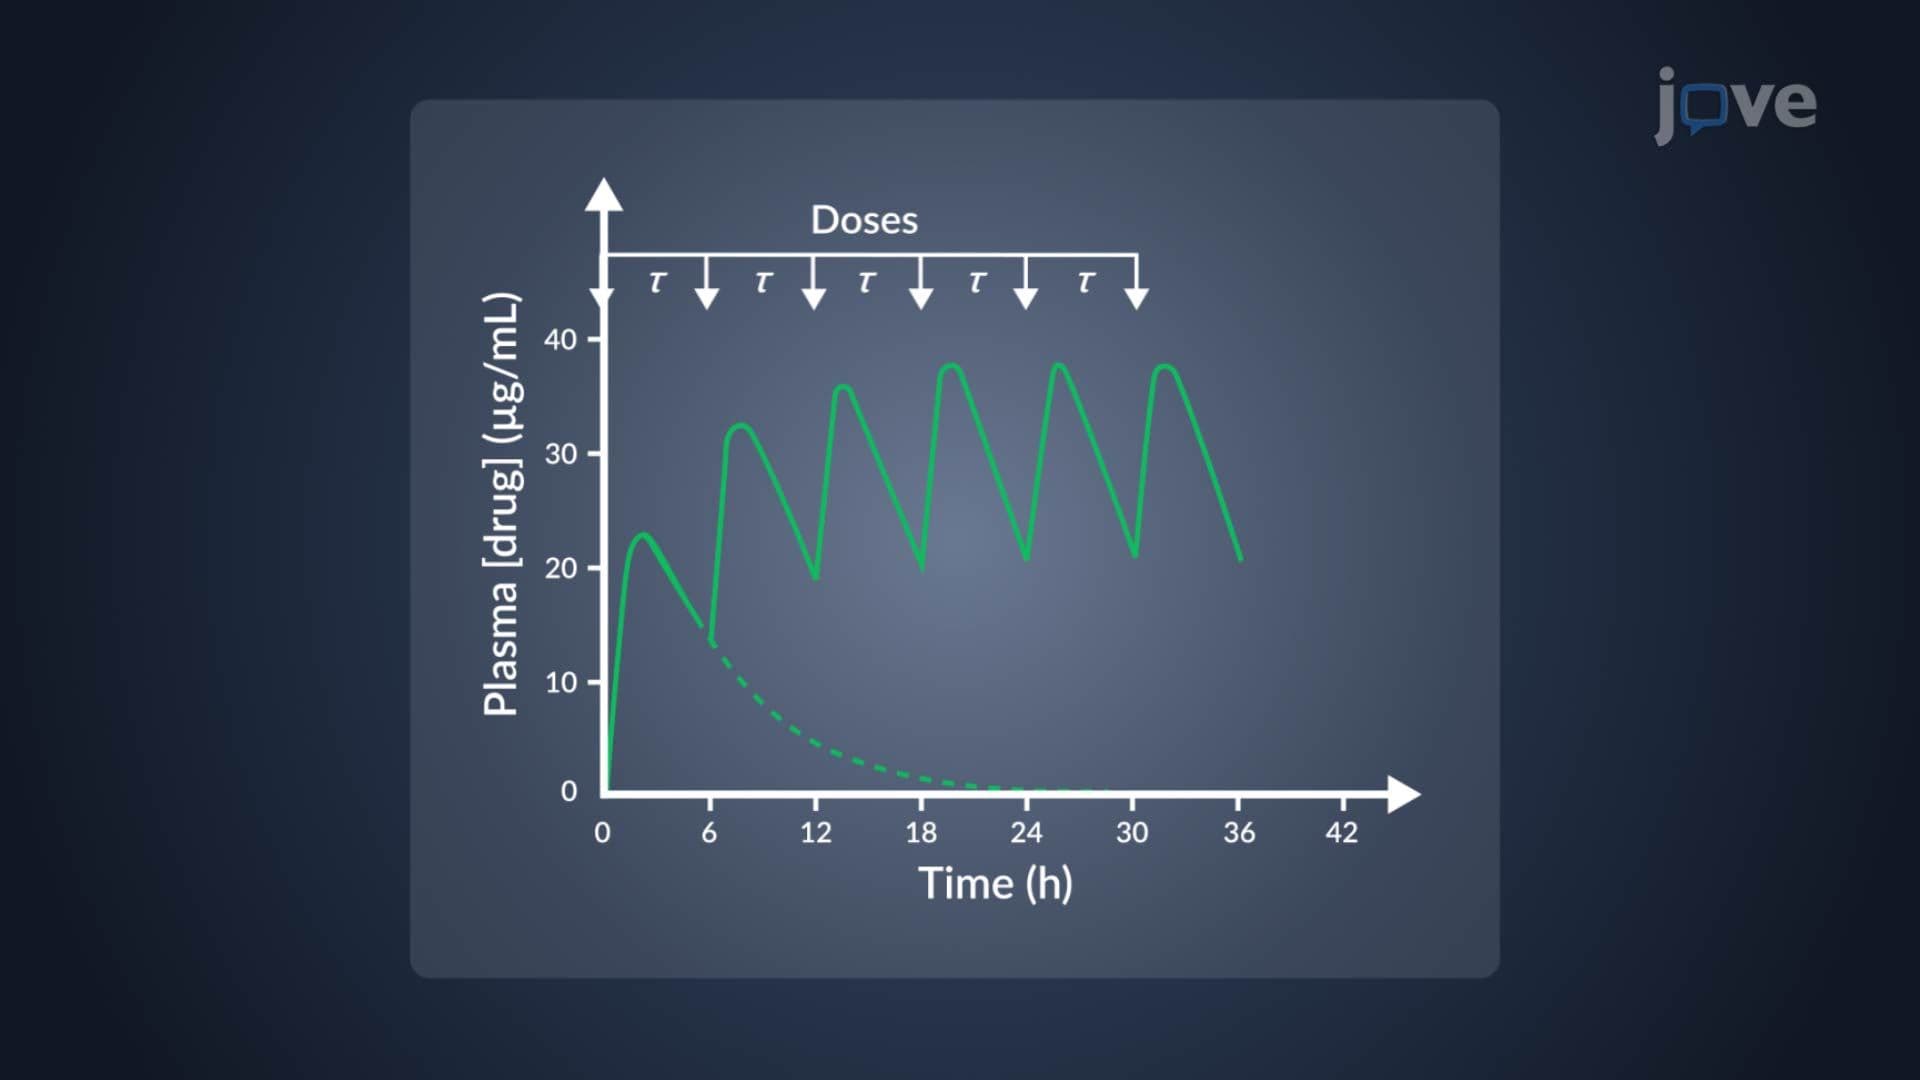 01:25
Dosage Regimen: Multiple Oral Dosage
 01:15
Drug Elimination by Renal Route: Tubular Secretion