Related Experiment Video
Updated: Aug 14, 2026

Contractions of Human-iPSC-derived Cardiomyocyte Syncytia Measured with a Ca-sensitive Fluorescent Dye in Temperature-controlled 384-well Plates
Published on: October 18, 2018
Cardiotonic steroids differentially affect intracellular Na+ and [Na+]i/[K+]i-independent signaling in C7-MDCK cells
Olga A Akimova1, Alexei Y Bagrov, Olga D Lopina
1Centre de recherche, Centre hospitalier de l'Université de Montréal, Montreal, Quebec H2W 1T7, Canada.

Abstract:
Recently, we reported that ouabain kills renal epithelial and vascular endothelial cells independently of elevation of the [Na(+)](i)/[K(+)](i) ratio. These observations raised the possibility of finding cardiotonic steroids (CTS) that inhibit the Na(+),K(+) pump without attenuating cell survival and vice versa. To test this hypothesis, we compared CTS action on Na(+),K(+) pump, [Na(+)](i) content, and survival of Madin-Darby canine kidney cells. At a concentration of 1 microM, ouabain and other tested cardenolides, as well as bufadienolides such as bufalin, cinobufagin, cinobufotalin, and telobufotoxin, led to approximately 10-fold inhibition of the Na(+),K(+) pump, a 2-3-fold decrease in staining with dimethylthiazol-diphenyltetrazolium (MTT), and massive death indicated by detachment of approximately 80% of cells and caspase-3 activation. In contrast, Na(+),K(+) pump inhibition and elevation of [Na(+)](i) seen in the presence of 3 microM marinobufagenin (MBG) and marinobufotoxin did not affect MTT staining and cell survival. Inhibition of the Na(+),Rb(+) pump in K(+)-free medium was not accompanied by a decline of MTT staining and cell detachment but increased sensitivity to CTS. In K(+)-free medium, half-maximal inhibition of (86)Rb influx was observed in the presence of 0.04 microM ouabain and 0.1 microM MBG, whereas half-maximal detachment and decline of MTT staining were detected at 0.03 and 0.004 microM of ouabain versus 10 and 3 microM of MBG, respectively. Both ouabain binding and ouabain-induced [Na(+)](i),[K(+)](i)-independent signaling were suppressed in the presence of MBG. Thus, our results show that CTS exhibit distinctly different potency in Na(+),K(+) pump inhibition and triggering of [Na(+)](i)/[K(+)](i)-independent signaling, including cell death.
Insights
Cardiotonic steroids (CTS) show varied effects on cell survival. Marinobufagenin inhibits the Na+,K+-pump without causing cell death, unlike ouabain, revealing distinct signaling pathways.
Area of Science:
- Biochemistry
- Cell Biology
- Pharmacology
Background:
- Cardiotonic steroids (CTS) are known to inhibit the Na+,K+-pump.
- Previous findings suggested ouabain induces cell death independently of Na+,K+-pump inhibition.
- This raises the possibility of CTS with differential effects on pump activity and cell survival.
Purpose of the Study:
- To compare the effects of various CTS on Na+,K+-pump activity, intracellular sodium ([Na+](i)) levels, and cell survival.
- To investigate the mechanisms underlying CTS-induced cell death and signaling.
Main Methods:
- Madin-Darby canine kidney cells were treated with different CTS (ouabain, bufadienolides, marinobufagenin).
- Na+,K+-pump inhibition was assessed by measuring 86Rb influx.
- Cell viability was evaluated using MTT assays and caspase-3 activation.
- Intracellular sodium ([Na+](i)) content was measured.
Main Results:
- Ouabain and other cardenolides/bufadienolides inhibited the Na+,K+-pump, decreased MTT staining, and induced significant cell death.
- Marinobufagenin (MBG) inhibited the Na+,K+-pump and increased [Na+](i) but did not affect cell survival or MTT staining.
- MBG suppressed ouabain-induced [Na+](i)/[K+](i)-independent signaling and cell death.
Conclusions:
- CTS exhibit distinct potencies in inhibiting the Na+,K+-pump and triggering [Na+](i)/[K+](i)-independent signaling pathways.
- Marinobufagenin represents a CTS that inhibits the Na+,K+-pump without inducing cell death, suggesting separable mechanisms of action.
- These findings differentiate CTS based on their impact on cell survival and pump inhibition, offering potential for targeted therapeutic development.


Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:26
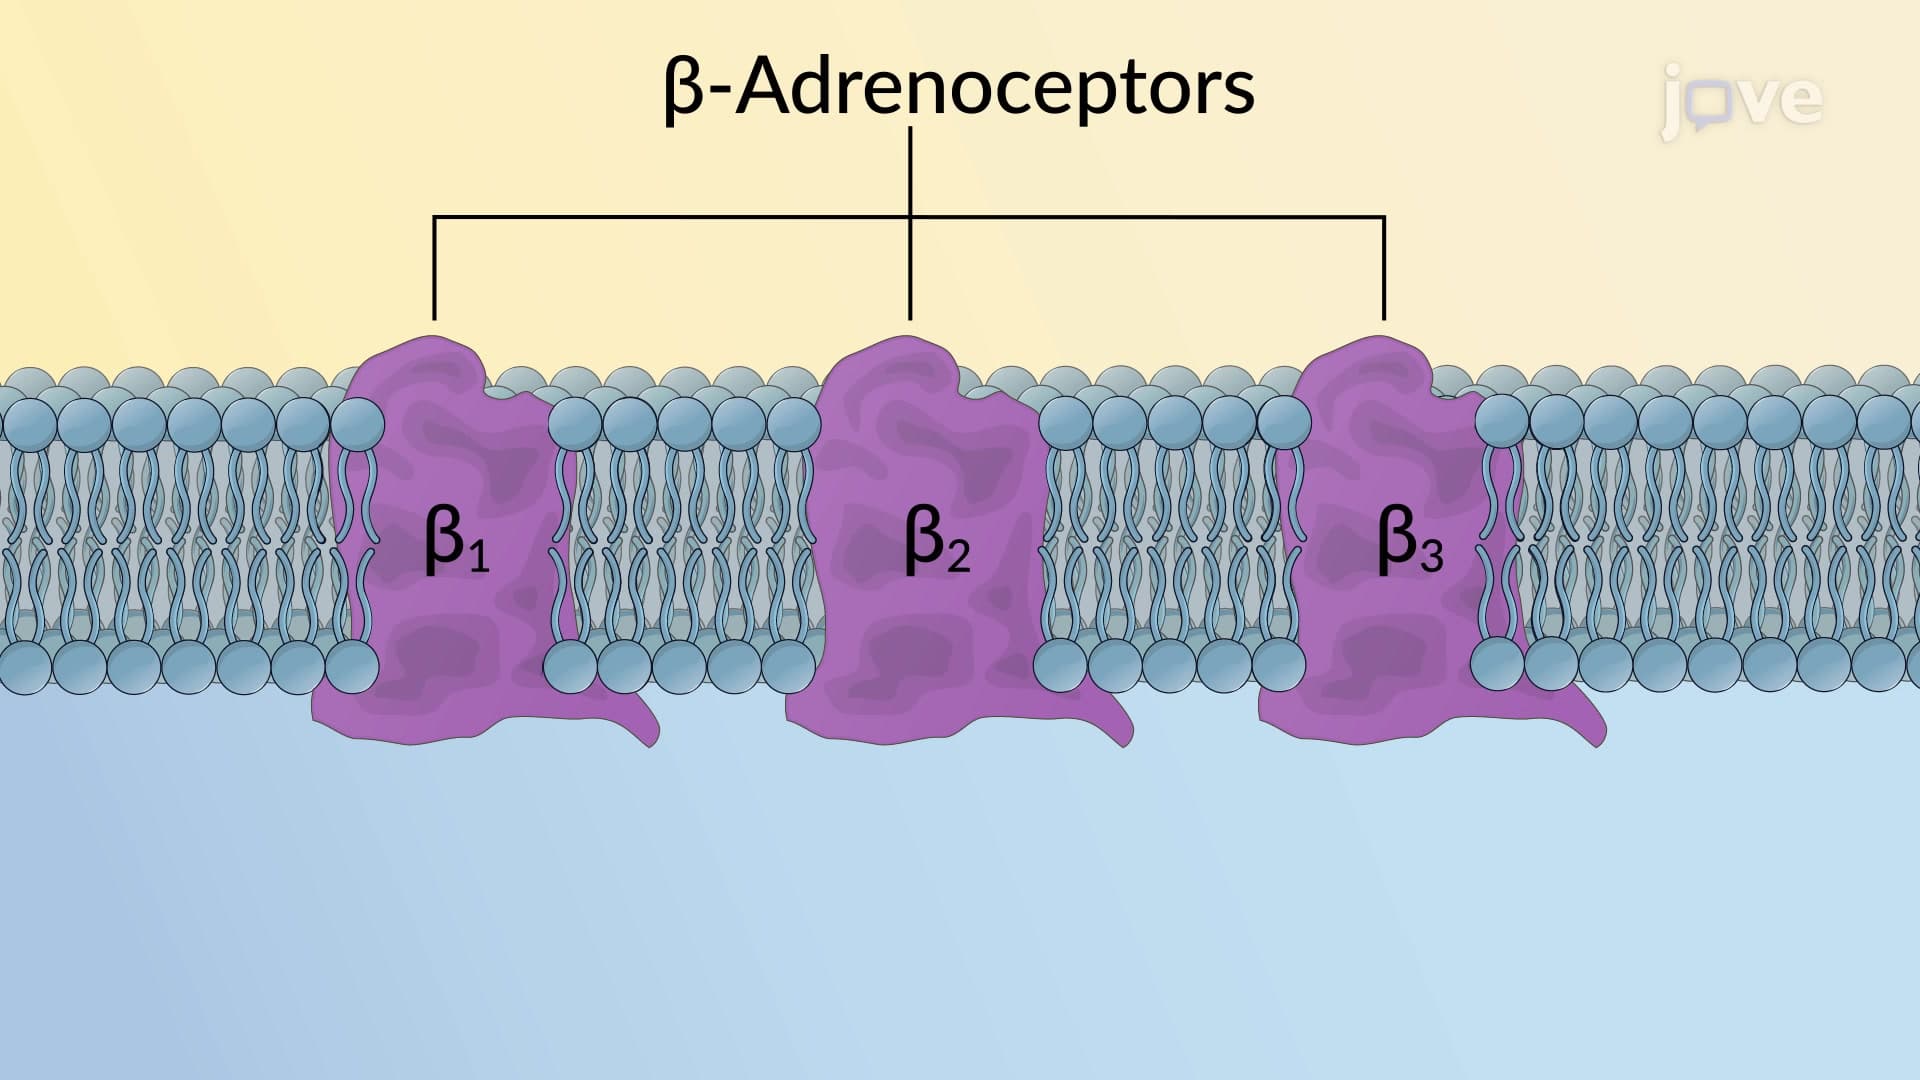
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:26
Heart Failure Drugs: Inotropic Agents