Related Experiment Video
Updated: Aug 21, 2026

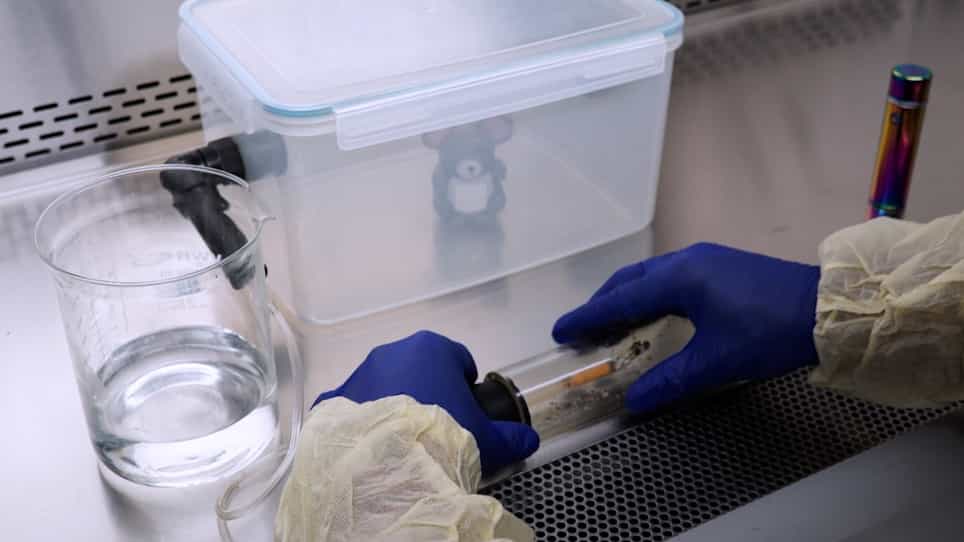
Methods to Evaluate Cytotoxicity and Immunosuppression of Combustible Tobacco Product Preparations
Published on: January 10, 2015
Effects of smokeless tobacco "Maras powder" use on respiratory functions
Mehmet Akif Buyukbese1, Nurhan Koksal, Aytekin Guven
1Department of Internal Medicine, Kahramanmaras Sutcu Imam University, Faculty of Medicine, 46050 Kahramanmaras, Turkey. akif_buyukbese@yahoo.com.

Abstract:
In Turkey, "Maras Powder," which is a kind of powder yielded from the shields of tobacco, is widely used as smokeless tobacco through buccal mucosa or together with cigarette. Maras powder, composed of ash and a plant named Nicotiana Rustica Linn, is sometimes used to give up smoking. The present study was aimed to investigate the effects of Maras powder use on respiratory functions of healthy subjects who do not have any chronic disease. We found statistically significant differences in percentage of forced expiratory volume in the first second (FEV(1)%) (p = 0.001), the ratio of FEV(1) to forced vital capacity (FEV(1)/FVC) (p = 0.024), percent of maximum expiratory flow rate (FEF(25-75)%) (p = 0.002) and percent of peak expiratory flow (PEF%) (p = 0.037) between cigarette smokers with Maras powder use (n = 23) and control subjects (n = 24). Likewise, when cigarette smokers (n = 24) and control subjects were compared, the differences for all these parameters were significant (p = 0.022, p = 0.048, p = 0.011 and p = 0.047, respectively). Only FEV(1)% and FEF(25-75)% were significantly lower in cigarette smokers with Maras powder use than in Maras powder users (n = 28) (p = 0.011 and p = 0.022, respectively). There was a negative correlation between forced vital capacity and Maras powder use (r = -0.315, p = 0.03). The present study suggests that Maras powder does not cause serious bronchial obstruction. This may be due to usage of the smokeless tobacco through buccal mucosa but not through inhalation as in case of cigarette smoking.
Related Concept Videos
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:23
Drugs Acting on Autonomic Ganglia: Stimulants
Ganglionic stimulants activate NM nicotinic receptors in autonomic ganglia, falling into two categories: nicotine mimetics [e.g., lobeline, dimethylpiperazine, tetramethylammonium] and muscarinic receptor agonists [e.g., muscarine, methacholine]. The first category's action is rapid and blocked by nicotinic receptor antagonists, while the second category's action is delayed and blocked by atropine-like agents. Nicotine, an alkaloid, affects the heart rate by stimulating sympathetic or...
 01:29
Stimulants
Cocaine can be administered via snorting, injection, or smoking. It primarily functions by blocking the reuptake of dopamine, resulting in a euphoric high characterized by an intense sensation of happiness and...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features