
Physiological hyperinsulinemia in dogs augments access of macromolecules to insulin-sensitive tissues
Martin Ellmerer1, Stella P Kim, Marianthe Hamilton-Wessler
1Department of Physiology and Biophysics, University of Southern California School of Medicine, 1333 San Pablo St., MMR 626, Los Angeles, CA 90033, USA.

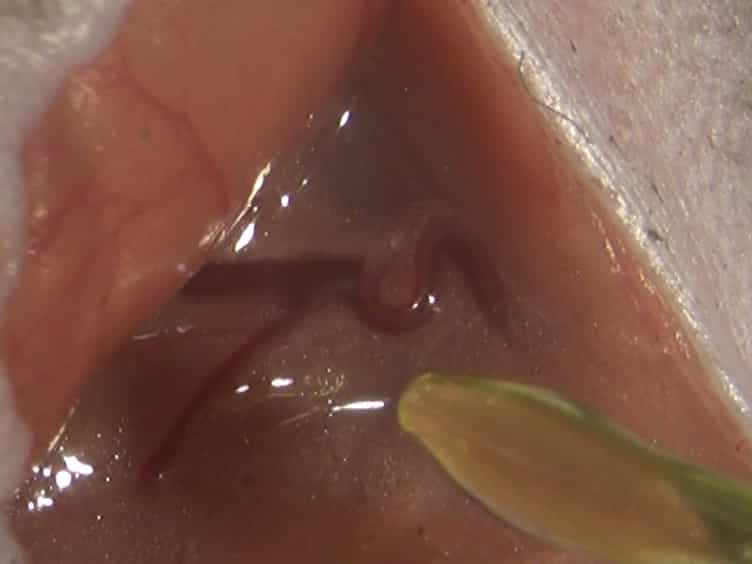
Pharmacological doses of insulin increase limb blood flow and enhance tissue recruitment for small solutes such as glucose. We investigated whether elevating insulin within the physiological range (68 +/- 6 vs. 425 +/- 27 pmol/l) can influence tissue recruitment of [(14)C]inulin, an inert diffusionary marker of molecular weight similar to that of insulin itself. During hyperinsulinemic-euglycemic clamps, transport parameters and distribution volumes of [(14)C]inulin were determined in conscious dogs by applying a three-compartment model to the plasma clearance data of intravenously injected [(14)C]inulin (0.8 microCi/kg). In a second set of experiments in anesthetized dogs with direct cannulation of the hindlimb skeletal muscle lymphatics, we measured a possible effect of physiological hyperinsulinemia on the response of the interstitial fluid of skeletal muscle to intravenously injected [(14)C]inulin and compared this response with the model prediction from plasma data. Physiological hyperinsulinemia caused a 48 +/- 10% (P < 0.005) and a 35 +/- 15% (P < 0.05) increase of peripheral and splanchnic interstitial distribution volumes for [(14)C]inulin. Hindlimb lymph measurements directly confirmed the ability of insulin to enhance the access of macromolecules to the peripheral interstitial fluid compartment. The present results show that physiological hyperinsulinemia will enhance the delivery of a substance of similar molecular size to insulin to previously less intensively perfused regions of insulin-sensitive tissues. Our data suggest that the delivery of insulin itself to insulin-sensitive tissues could be a mechanism of insulin action on cellular glucose uptake independent of and possibly synergistic with either enhanced blood flow distribution or GLUT4 transporter recruitment to enhance glucose utilization. Because of the differences between inulin and insulin itself, whether delivery of the bioactive hormone is increased remains speculative.
Pharmacological doses of insulin increase limb blood flow and enhance tissue recruitment for small solutes such as glucose. We investigated whether elevating insulin within the physiological range (68 +/- 6 vs. 425 +/- 27 pmol/l) can influence tissue recruitment of [(14)C]inulin, an inert diffusionary marker of molecular weight similar to that of insulin itself. During hyperinsulinemic-euglycemic clamps, transport parameters and distribution volumes of [(14)C]inulin were determined in conscious dogs by applying a three-compartment model to the plasma clearance data of intravenously injected [(14)C]inulin (0.8 microCi/kg). In a second set of experiments in anesthetized dogs with direct cannulation of the hindlimb skeletal muscle lymphatics, we measured a possible effect of physiological hyperinsulinemia on the response of the interstitial fluid of skeletal muscle to intravenously injected [(14)C]inulin and compared this response with the model prediction from plasma data. Physiological hyperinsulinemia caused a 48 +/- 10% (P < 0.005) and a 35 +/- 15% (P < 0.05) increase of peripheral and splanchnic interstitial distribution volumes for [(14)C]inulin. Hindlimb lymph measurements directly confirmed the ability of insulin to enhance the access of macromolecules to the peripheral interstitial fluid compartment. The present results show that physiological hyperinsulinemia will enhance the delivery of a substance of similar molecular size to insulin to previously less intensively perfused regions of insulin-sensitive tissues. Our data suggest that the delivery of insulin itself to insulin-sensitive tissues could be a mechanism of insulin action on cellular glucose uptake independent of and possibly synergistic with either enhanced blood flow distribution or GLUT4 transporter recruitment to enhance glucose utilization. Because of the differences between inulin and insulin itself, whether delivery of the bioactive hormone is increased remains speculative.


Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:24
Type II Diabetes II: Pathophysiology
 01:28
Insulin: The Receptor and Signaling Pathways
 01:15
Hypoglycemia and Glucagon