Related Experiment Video
Updated: Aug 21, 2026
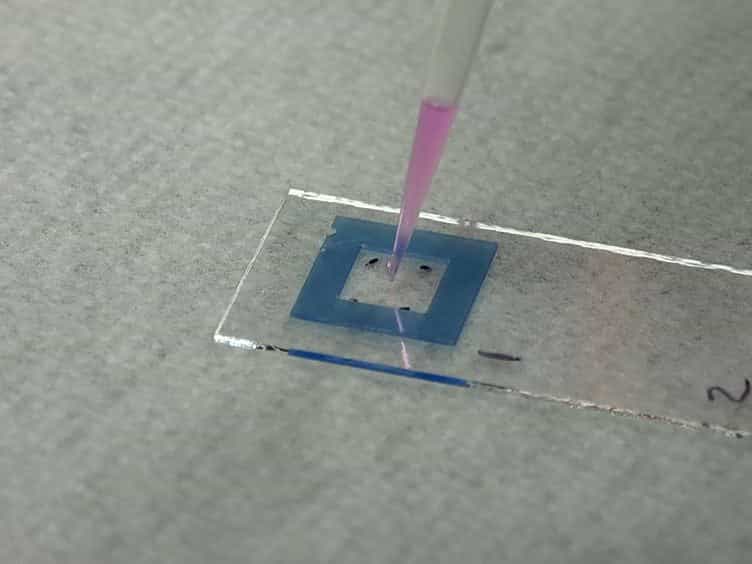

Demonstrating a Multi-drug Resistant Mycobacterium tuberculosis Amplification Microarray
Published on: April 25, 2014
Tuberculosis in Australia: bacteriologically confirmed cases and drug resistance, 2002: a report of the Australian
Richard Lumb1, Ivan Bastian, William Chew
1Infectious Diseases Laboratories, Institute of Medical and Veterinary Science, Adelaide, South Australia. richard.lumb@imvs.sa.gov.au

Abstract:
The Australian Mycobacterium Reference Laboratory Network collected and analysed laboratory data on new cases of disease caused by Mycobacterium tuberculosis complex in the year 2002. A total of 712 cases were identified by bacteriology, representing an annual reporting rate of 3.6 cases of laboratory-confirmed tuberculosis per 100,000 population. The most commonly encountered culture-positive specimens were sputum (n=325), lymph node (n=142) and bronchoscopy (n=100). Smears containing acid fast bacilli were present in sputum (53.2%), bronchoscopy (37.9%) and lymph node (21.2%). Eight children (male n=3, female n=5) under 10 years of age had bacteriologically-confirmed tuberculosis. A total of 55 isolates (7.7%) of M. tuberculosis were resistant to at least one of the standard anti-tuberculosis agents. Resistance to at least isoniazid and/or rifampicin was noted for 53 isolates (7.4%), with multidrug-resistance (MDRTB) observed in 12 (1.9%) isolates. Of the 12 MDRTB isolates, eight were from the respiratory tract and five were from smear positive specimens. Of the patients with drug resistant M. tuberculosis isolates, 51/55 (92.7%) were classified as having initial resistance, none had acquired resistance during treatment in Australia. The country of birth was known for 54 of 55 such patients; four were Australian-born, and 50 (90.9%) had migrated from a total of 17 countries. Nucleic acid amplification testing (NAAT) was performed on 139 (19.5%) of the 712 culture-positive specimens. Of smear positive respiratory specimens, 74/80 (92.5%) were NAAT positive. For smear negative respiratory specimens, 12/17 (70.6%) reported a NAAT positive result. Importantly, false-negative NAAT results were obtained from 1/16 and 5/64 of smear positive bronchoscopy and sputum specimens respectively.

Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:23
Tuberculosis
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...