Related Experiment Video
Updated: Jan 29, 2026
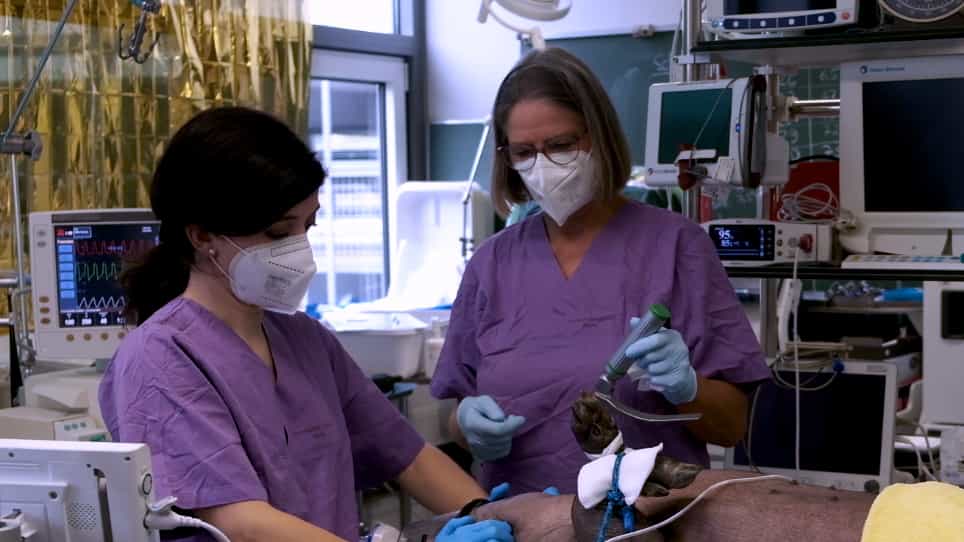

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
[Successful tracheal intubation in a child with facial multi-clefts and difficult airway: case report.]
Qing-sheng Geng1, Hui Xu, Hong Jiang
1Department of Anesthesiology, Ninth People's Hospital, Shanghai Second Medical University, Shanghai 200011, China.

Insights
Managing airway challenges in pediatric plastic surgery is crucial. This case highlights difficulties with tracheal intubation in a child with severe facial clefts and undiagnosed bilateral anodontia.
Area of Science:
- Anesthesiology
- Pediatric Surgery
- Craniofacial Surgery
Background:
- A 7-year-old male patient presented for plastic surgery due to severe facial abnormalities from combined facial clefts.
- Preoperative assessment did not identify bilateral anodontia, a condition of missing teeth.
Observation:
- Induction of general anesthesia led to dyspnea and hypoventilation, requiring an oropharyngeal airway.
- Direct laryngoscopy revealed laryngospasm, managed with airway insertion and ventilation.
- Multiple attempts at blind nasal tracheal intubation were unsuccessful.
Findings:
- Tracheal intubation was ultimately achieved via blind oral intubation with direct laryngoscope assistance.
- Severe facial abnormalities and undiagnosed bilateral anodontia complicated airway management.
Implications:
- This case underscores the importance of thorough preoperative airway evaluation in pediatric patients with craniofacial anomalies.
- Anesthesiologists must be prepared for difficult airway management strategies in complex pediatric cases.
- Early recognition and management of airway complications are vital for patient safety during surgery.
Abstract:
A male patient, aged 7 years, was intended to undergo plastic surgery under general anesthesia with tracheal intubation for his severe facial abnormities as a result of 5, 6, 7 combined facial clefts. Because of his severe facial abnormities and preoperative undetected bilateral antiadoncus, during the period of induction, dyspnoea and dysventilation took place, which were relieved by inserting a medium-sized oropharyngeal airway with difficulty; during euthyphoirally exploring his endolarynx with direct laryngoscope, laryngospasm occurred, which was relieved through inserting airway and pressurizing ventilation; repetitively attempted to blindly insert tracheal intubation through nostril, but failed. Finally, his intubation was achieved by blindly intubating through oral cavity under the assistance of direct laryngoscope.


Related Concept Videos
 02:17
Ecological Succession
 01:14
Muscles for Facial Expressions
 01:24
Facial Feedback Hypothesis
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:24
Data Reporting and Recording
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required