Related Experiment Video
Updated: Aug 21, 2026
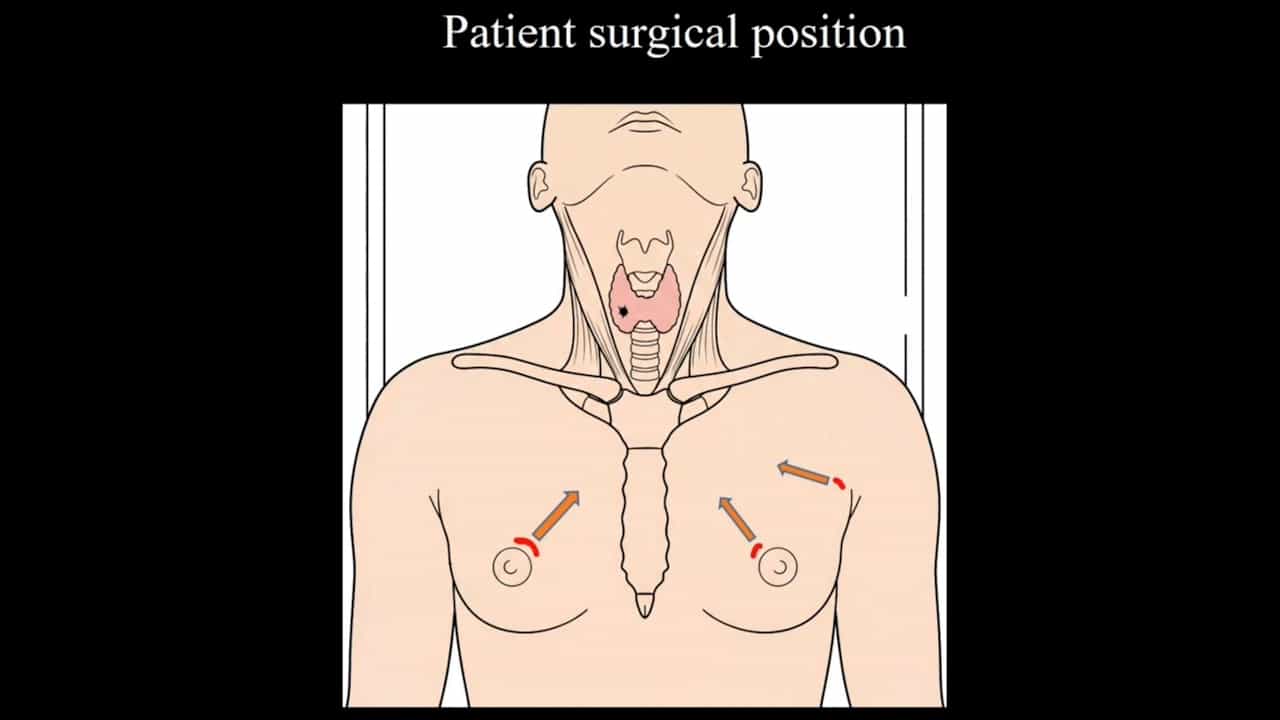

A Novel Contralateral Axillo-Bilateral-Breast Approach for Endoscopic Thyroid Surgery
Published on: July 28, 2026
Single center experience in primary surgery for medullary thyroid carcinoma
Jörg Ukkat1, Oliver Gimm, Michael Brauckhoff
1Department of General Surgery, Martin-Luther-University Halle-Wittenberg, Ernst-Grube-Strasse 40, D-06097 Halle/Saale, Germany.

Abstract:
Medullary thyroid carcinoma (MTC) is a rare disease, and most studies are either based on small numbers or multicenter studies with their inherent difficulties. Since 1995, a total of 440 patients with MTC underwent surgery in our clinic. A primary operation was performed in 188 patients (43% of 440). In 60 patients, the primary operation was performed because of a germline RET mutation ("prophylactic surgery"). Most (84%, 158/188) of the patients had pathologic calcitonin levels. Notably, MTC was found in almost 10% (3/30) of patients with normal calcitonin levels. However, all patients with lymph node metastases (LNMs) had elevated calcitonin levels. Total thyroidectomy (TTx) was performed in all patients. Lymph node dissection (LND) was performed at various extensions: one-compartment LND in 35% (66/188), three-compartment LND in 31% (58/188), and four-compartment LND in 29% (22/188). In general, lymph node dissection increased the likelihood of complications. LNM and distant metastases (DM) correlated with the extent of the primary tumor (pT category). The presence of LNM ranged from 17% (pT1 tumor) to 100% (pT4 tumor), whereas the presence of DM ranged from 0% (pT1 tumor) to 81% (pT4 tumor). Biochemical cure (normal calcitonin levels) was obtained in 72% (137/188) of patients. All 60 patients undergoing prophylactic surgery (tumor stage pT0/pT1) were biochemically cured. In contrast, only 60% (77/128) of the remaining patients were cured. The data suggest that primary surgery should be scheduled as soon as possible to treat patients at a node-negative stage. In the case of normal basal and elevated stimulated calcitonin levels, TTx and cervicocentral LND is recommended. If the basal calcitonin level is elevated, LND should include the cervicolateral compartment.
More Related Videos
 04:01
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
 07:45
"Sun's Seven-Step Technique" for Endoscopic En-Bloc Resection of Thyroid Cancer via the Chest-Breast Approach
Published on: November 28, 2025