Related Experiment Video
Updated: Aug 20, 2026
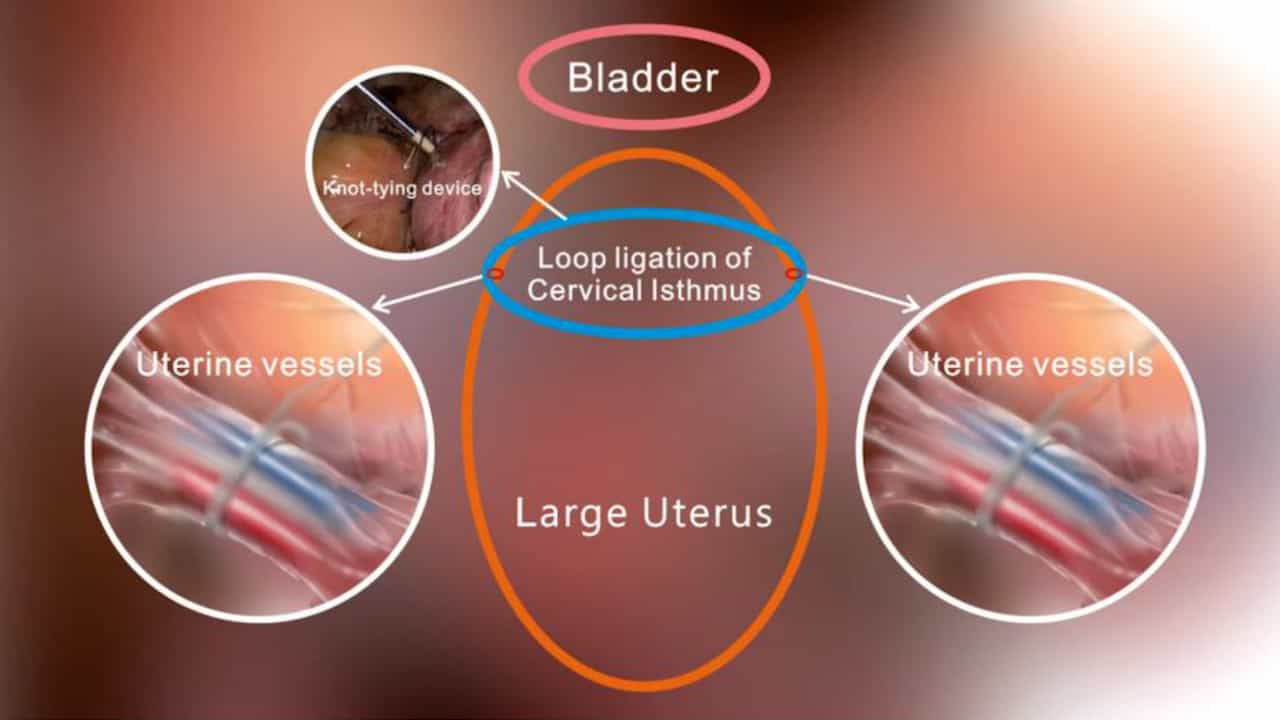

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Outpatient laparoscopic hysterectomy in a rural ambulatory surgery center
John E Morrison1, Volker R Jacobs
1Department of Surgery, Lamar Regional Healthcare Center, Sulligent, Alabama, USA.

Study Objective:
To evaluate a cost-optimized operative technique for outpatient laparoscopic hysterectomy in a rural ambulatory surgery center focusing on shortening hospital stay and substitution of expensive disposable laparoscopic instruments with standard surgical techniques.
Design:
Prospective feasibility and observational study (Canadian Task Force classification II-3).
Setting:
Rural ambulatory surgery center in Lamar, Alabama.
Patients:
Fifty-two women.
Intervention:
Outpatient laparoscopic hysterectomy.
Measurements And Main Results:
From September 2001 through September 2003, 52 consecutive procedures with a modified classical intrafascial supracervical hysterectomy (CISH) technique without disposable instruments have been performed on patients with an average age of 42.2 years (range 25-62 years) and a follow-up of 12.5 months (range 0.4-23.6 months). Mean postoperative length of stay was 6 hours, 79 minutes (range 3 hours, 10 minutes-17 hours, 30 minutes), and overall length of stay was 11 hours, 37 minutes (range 6 hours, 45 minutes-22 hours, 50 minutes). Five patients (9.6%) stayed overnight, three for medical and two for social reasons. With an average of 2 hours, 14 minutes, the operating room time was about 1 hour longer than with disposable instruments. Health insurance reimbursement for the ambulatory surgery center was on average $1814.11. No complications occurred, and no readmission to the hospital was necessary.
Conclusion:
Outpatient laparoscopic hysterectomy is feasible and safe and can be performed cost effectively in ambulatory surgery centers, even in rural areas. Development of a protocol with patient selection, preoperative and postoperative patient teaching, caring family environment, and round-the-clock medical telephone backup is necessary.
