Guidelines for blood test monitoring of methotrexate toxicity in juvenile idiopathic arthritis
Related Experiment Videos
Oliva Ortiz-Alvarez1, Kimberly Morishita, Glenda Avery
1Division of Rheumatology, Department of Pediatrics, University of British Columbia, Vancouver, British Columbia, Canada.

Objective:
To assess the utility of the American College of Rheumatology guidelines for monitoring methotrexate (MTX)-related toxicity in a cohort of children with juvenile idiopathic arthritis (JIA).
Methods:
Eighty-nine patients with JIA treated with MTX were monitored prospectively: aspartate aminotransferase (AST), alanine aminotransferase (ALT), complete blood count (CBC), and differential blood count were measured prior to starting MTX, and then monthly. Significantly abnormal blood tests (SABT) were prospectively defined as (1) significantly elevated liver enzymes (SELE) greater than twice the upper limit of normal; (2) granulocyte count < 1.5 109/l; (3) lymphocyte count < 0.9 109/l; or (4) hemoglobin decreased by > 2 g/l from previous level. Clinical interventions, current and cumulative MTX dose, duration of treatment, comorbidity, and concurrent medications at the time of the first SABT identification were recorded. Independent t tests and chi-squared tests were used for comparisons, and the probability of developing a SABT was calculated by Kaplan-Meier survival analysis.
Results:
Forty percent of patients had a SABT: 26% had hematological abnormalities and 14% had SELE. Ninety-five percent of patients with SABT had symptoms consistent with a viral infection when the SABT was drawn and MTX dose was withheld until results had normalized on repeat testing. SABT persisting beyond one month occurred in only 2 patients, and their abnormalities resolved by 6 months with no specific identified cause; they resumed MTX at a later time without recurrence of SABT. There were no differences between patients with and without SABT with respect to current or cumulative MTX dose, duration of treatment, and concurrent medications at the time of the SABT. The probability of developing a SABT was estimated to be 11% at 3 months, compared to 10% probability of having an abnormal blood test by chance alone.
Conclusion:
Routine blood tests every 4 to 8 weeks in children with JIA are unnecessarily frequent.
Insights
Routine blood tests for monitoring methotrexate toxicity in children with juvenile idiopathic arthritis (JIA) may be too frequent. Most abnormal results were transient and linked to viral infections, suggesting less frequent monitoring may suffice.
Area of Science:
- Pediatric Rheumatology
- Clinical Toxicology
- Pharmacovigilance
Background:
- Methotrexate (MTX) is a cornerstone therapy for juvenile idiopathic arthritis (JIA).
- Monitoring for MTX-related toxicity is crucial, guided by American College of Rheumatology (ACR) guidelines.
- Current guidelines recommend frequent laboratory monitoring.
Purpose of the Study:
- To evaluate the clinical utility of ACR guidelines for monitoring MTX-related toxicity in pediatric JIA patients.
- To determine the actual frequency and nature of significantly abnormal blood tests (SABT) in this population.
Main Methods:
- Prospective monitoring of 89 children with JIA treated with MTX.
- Monthly assessment of liver enzymes (AST, ALT), complete blood count (CBC), and differential blood count.
- Defined SABT criteria including elevated liver enzymes, low granulocyte/lymphocyte counts, or decreased hemoglobin.
Main Results:
- 40% of patients experienced at least one SABT (14% liver, 26% hematologic).
- 95% of SABTs were associated with viral infections; abnormalities normalized after MTX dose withholding.
- No significant differences in MTX dose, duration, or concurrent medications were found between patients with and without SABT.
Conclusions:
- The frequency of routine blood tests recommended by ACR guidelines may be excessive for monitoring MTX toxicity in JIA.
- Less frequent monitoring could be considered, balancing safety with resource utilization.
Related Concept Videos
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:26
Therapeutic Drug Monitoring: Drug Analysis Methods
 01:29
Drug Dosing: Infants and Children
 01:18
Chronic Kidney Disease IV: Nursing Management
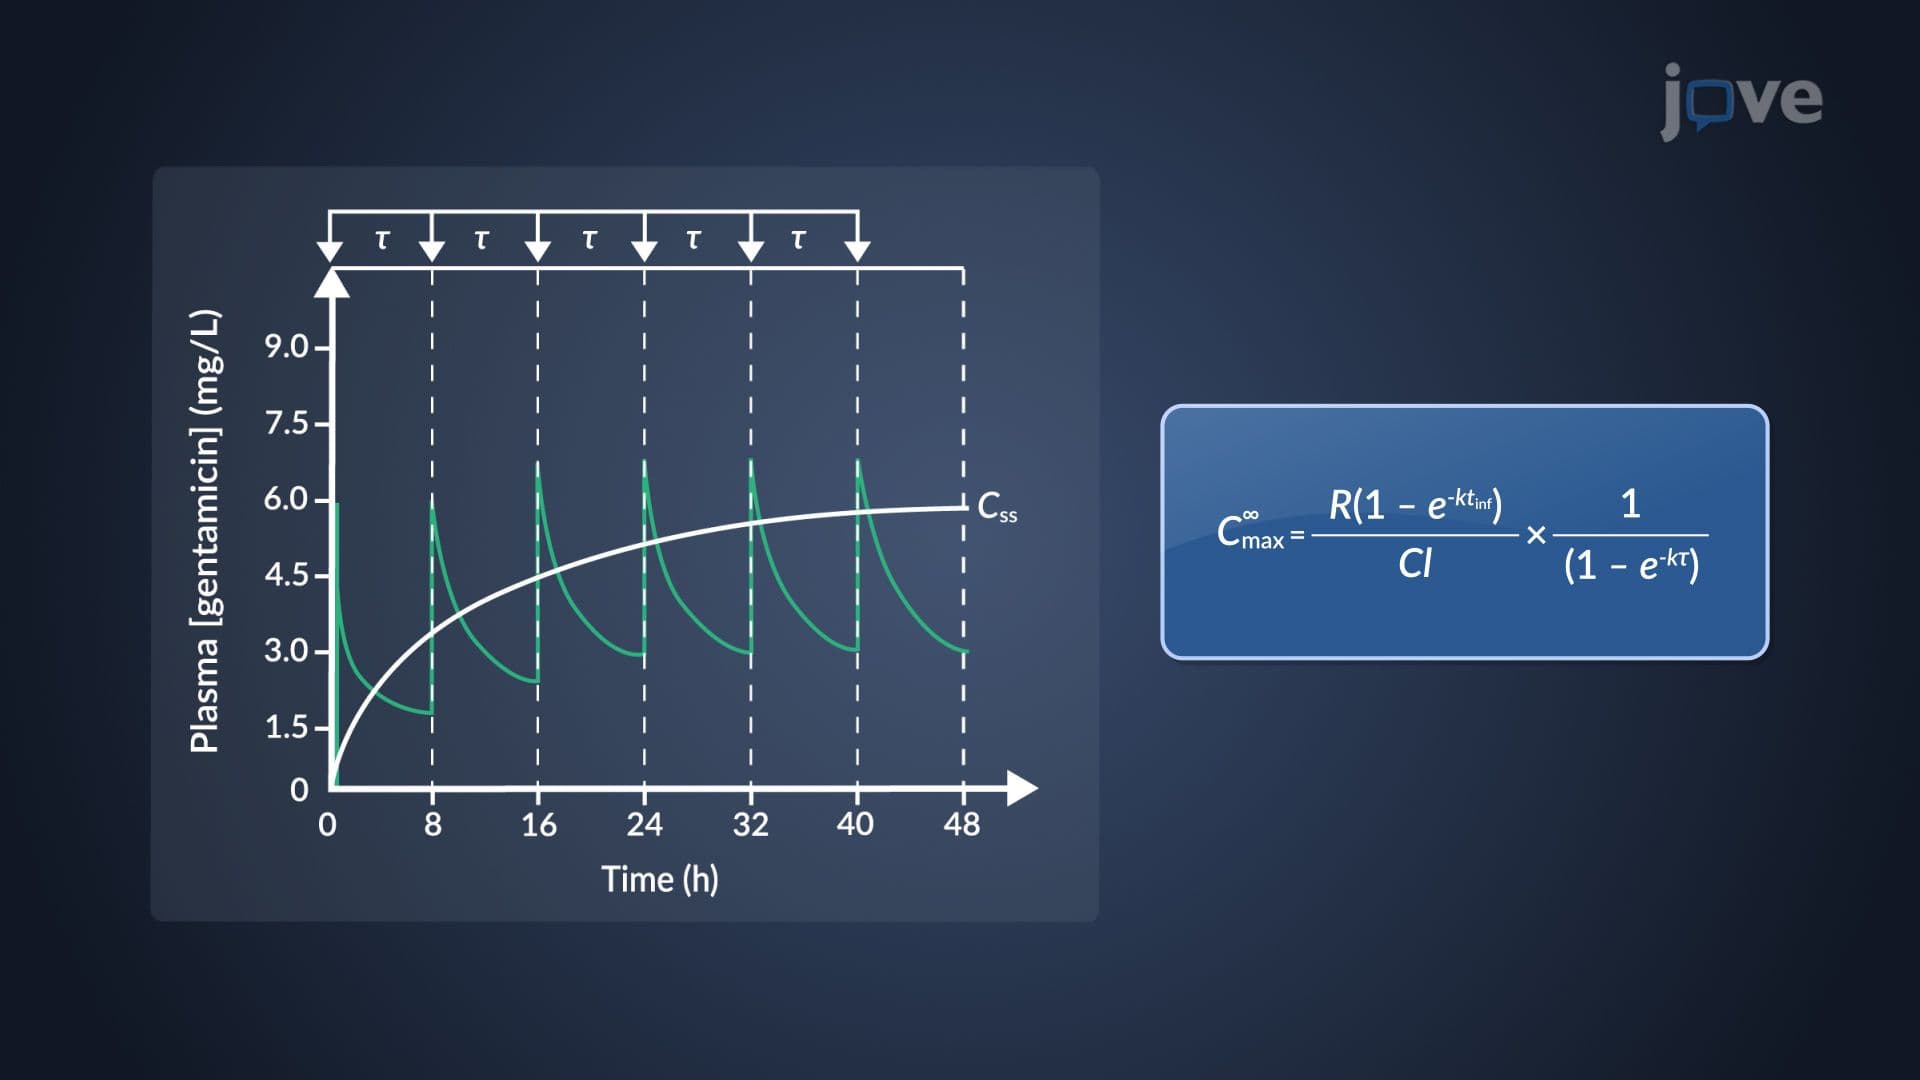 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations