Related Experiment Video
Updated: Aug 20, 2026

Absorption of Nasal and Bronchial Fluids: Precision Sampling of the Human Respiratory Mucosa and Laboratory Processing of Samples
Published on: January 21, 2018
Differential effects of fluticasone and montelukast on allergen-induced asthma
M Palmqvist1, C Bruce, M Sjöstrand
1Section of Allergy, The Lung Pharmacology Group, Department of Respiratory Medicine and Allergology, Göteborg University, Gothenburg, Sweden.

Abstract:
Early asthmatic responses (EAR) and late asthmatic responses (LAR) to allergen are induced by the local release of a series of bronchoconstrictor mediators, including leukotrienes and histamine. Both anti-leukotrienes and other anti-asthma drugs, such as inhaled glucocorticoids, have been shown to reduce both EAR and LAR. The aim of the present study was to directly compare the effects of regular treatment with an oral anti-leukotriene, montelukast (Mont; 10 mg once daily, for 8 days), and an inhaled glucocorticoid [fluticasone propionate (FP) 250 microg twice daily for 8 days] on the EAR and LAR to an inhaled allergen challenge. Patients with a documented EAR and LAR at a screening visit were randomized to these treatments, or placebo, in a double-blind, double-dummy, crossover fashion. Allergen challenge at a dose causing both an EAR and LAR was given on the eighth day of treatment. The maximum fall in FEV1 during the EAR was 17.8% during placebo treatment, 8.3% during Mont and 16.3% during FP (P <0.05 for Mont vs placebo). The maximum fall during the EAR was 13.8% during placebo treatment, 11.8% during Mont and 2% during FP treatment (P <0.05 for FP vs placebo and FP vs Mont). PC20 methacholine was significantly higher 24 h after allergen challenge during FP-treatment compared with Mont (P <0.05). Both montelukast and fluticasone reduced the relative amount of sputum eosinophils after allergen compared with placebo treatment. This study shows that anti-leukotrienes are effective to attenuate the EAR, whereas inhaled glucocorticoids are more effective than anti-leukotrienes in attenuating the EARs and improves bronchial hyperresponsiveness to a greater extent. In conclusion, inhaled glucocorticoids have overall greater efficacy than oral anti-leukotrienes to attenuate allergen-induced airway responses in mild asthmatic patients.
Related Concept Videos
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:20
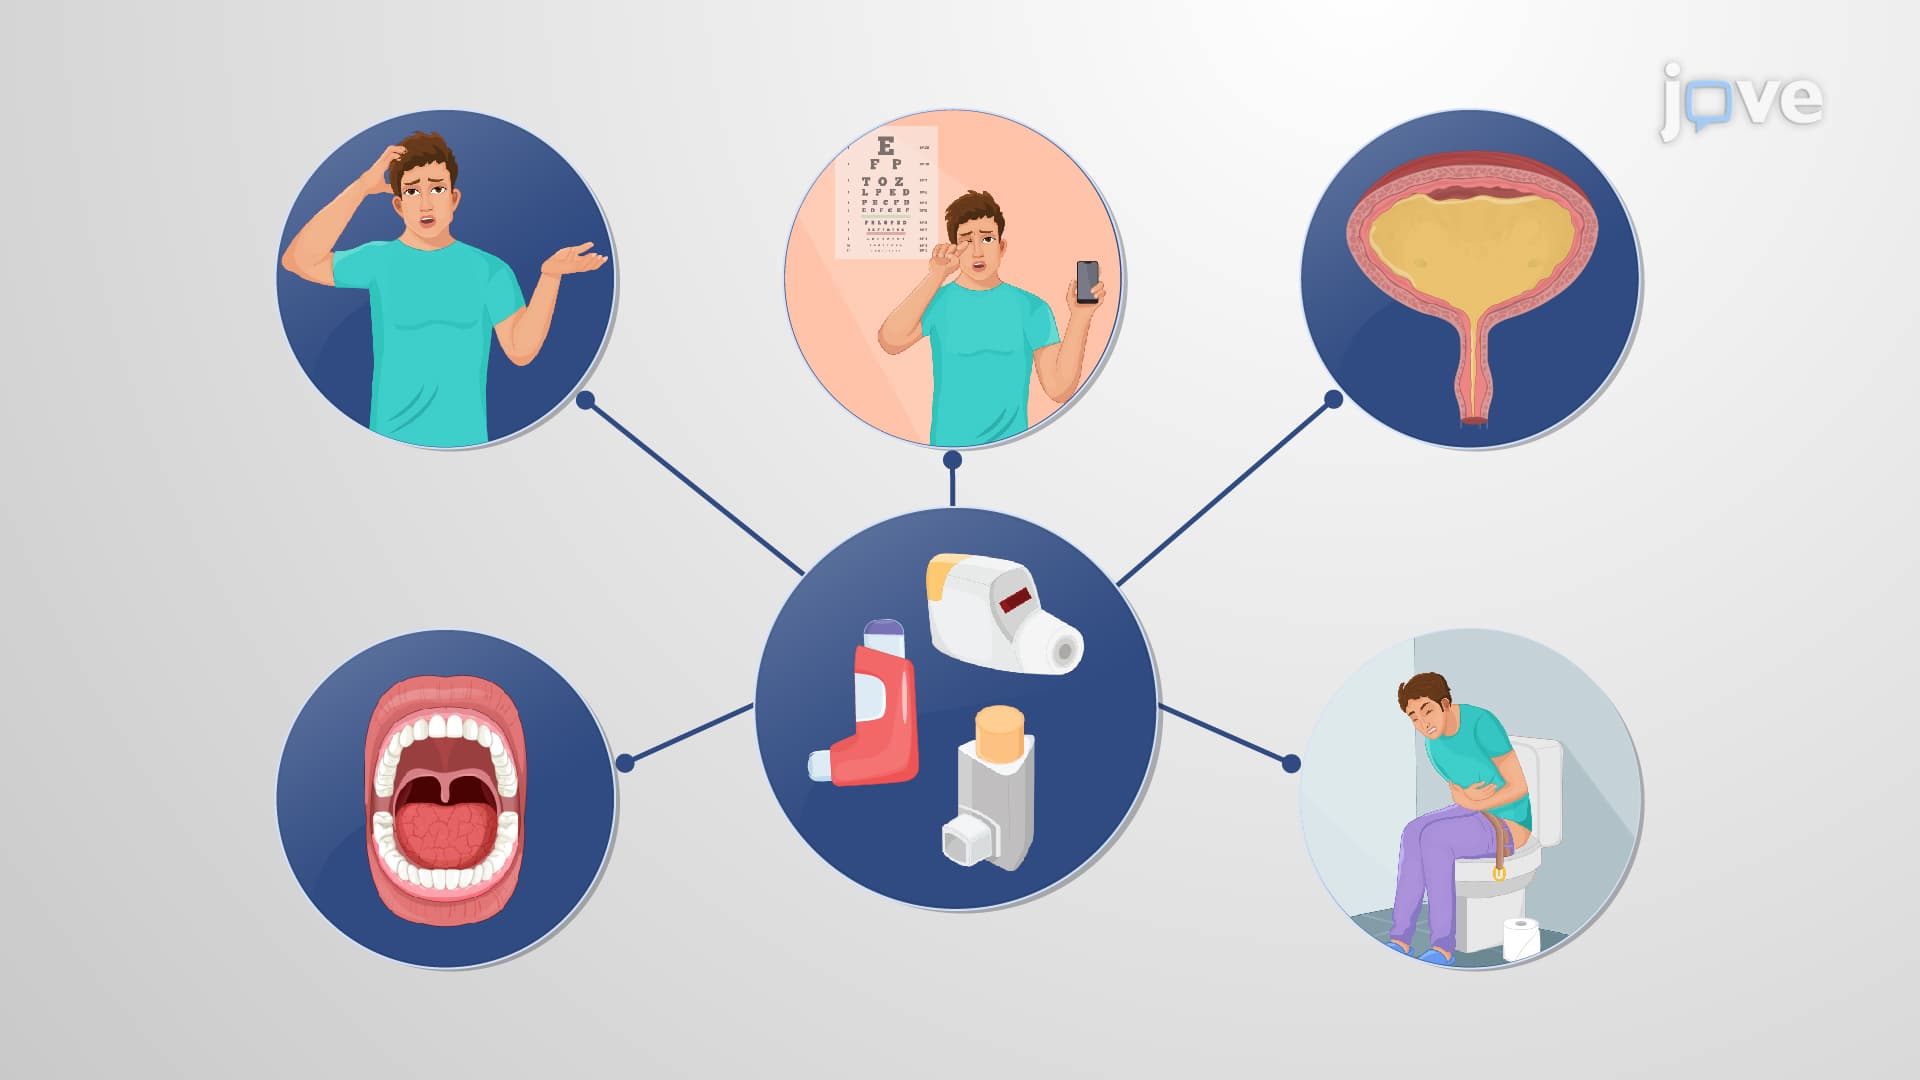
Antiasthma Drugs: Muscarinic Receptor Antagonists
Antimuscarinic agents compete with ACh for the same binding site on the muscarinic receptors. By binding to these receptors, they inhibit the downstream effects of ACh and block the parasympathetic...