
Insulin sensitivity and coronary vasoreactivity: insulin sensitivity relates to adenosine-stimulated coronary flow
1Cardiology Clinic, University of Essen, Essen, Germany. nikolaosdagres@yahoo.de

Objective:
Diabetes is associated with coronary microvasculature abnormalities and impaired coronary flow reserve (CFR). CFR is the ratio of coronary flow under maximal vasodilation to basal flow and is a measure for coronary vasoreactivity. Insulin resistance is the central defect in the development of type 2 diabetes, preceding its onset by 10-20 years. Thus, the relationship between insulin sensitivity and CFR in nondiabetic subjects is particularly interesting. The aim of the study was to investigate this relationship.
Design:
Cross-sectional study.
Patients:
The study population consisted of 18 nondiabetic subjects without coronary artery stenosis on coronary angiography. We excluded patients with structural heart disease or with conditions affecting CFR or insulin sensitivity such as low density lipoprotein (LDL)-cholesterol > or = 4.14 mmol/l, smoking, hypertension or obesity with a body mass index (BMI) > 28 kg/m(2).
Measurements And Results:
CFR was 3.1 +/- 0.8 (range 1.7-4.8), as assessed by intracoronary Doppler measurements in the left anterior descending coronary arteries after adenosine stimulation. Intravascular ultrasound revealed zero to moderate coronary atherosclerotic changes. Whole-body insulin sensitivity (M-value) was 7.5 +/- 2.9 mg/kg/min (range 2.2-12.6), as assessed by the hyperinsulinaemic-euglycaemic clamp test. Subjects with low CFR (< 3.0) had a significantly lower M-value than subjects with normal CFR (> 3.0) (6.0 +/- 2.5 vs. 9.0 +/- 2.5 mg/kg/min, P = 0.021). Univariate linear regression demonstrated a strong correlation between CFR and M-value (r = 0.76, P < 0.001). In multiple regression analysis, the significant association of CFR with M-value was independent of potential confounders (sex, age, BMI, LDL-cholesterol and plaque burden on intravascular ultrasound). Bootstrap analysis corroborated this finding.
Conclusions:
Whole-body insulin sensitivity relates to coronary vasoreactivity. Across a wide range of both insulin sensitivity and coronary flow reserve from markedly abnormal to normal values, an increase in insulin sensitivity appears to be associated with an increase in coronary flow reserve. Insulin resistance is therefore associated with coronary microvasculature abnormalities in nondiabetics.

Related Concept Videos
 01:31
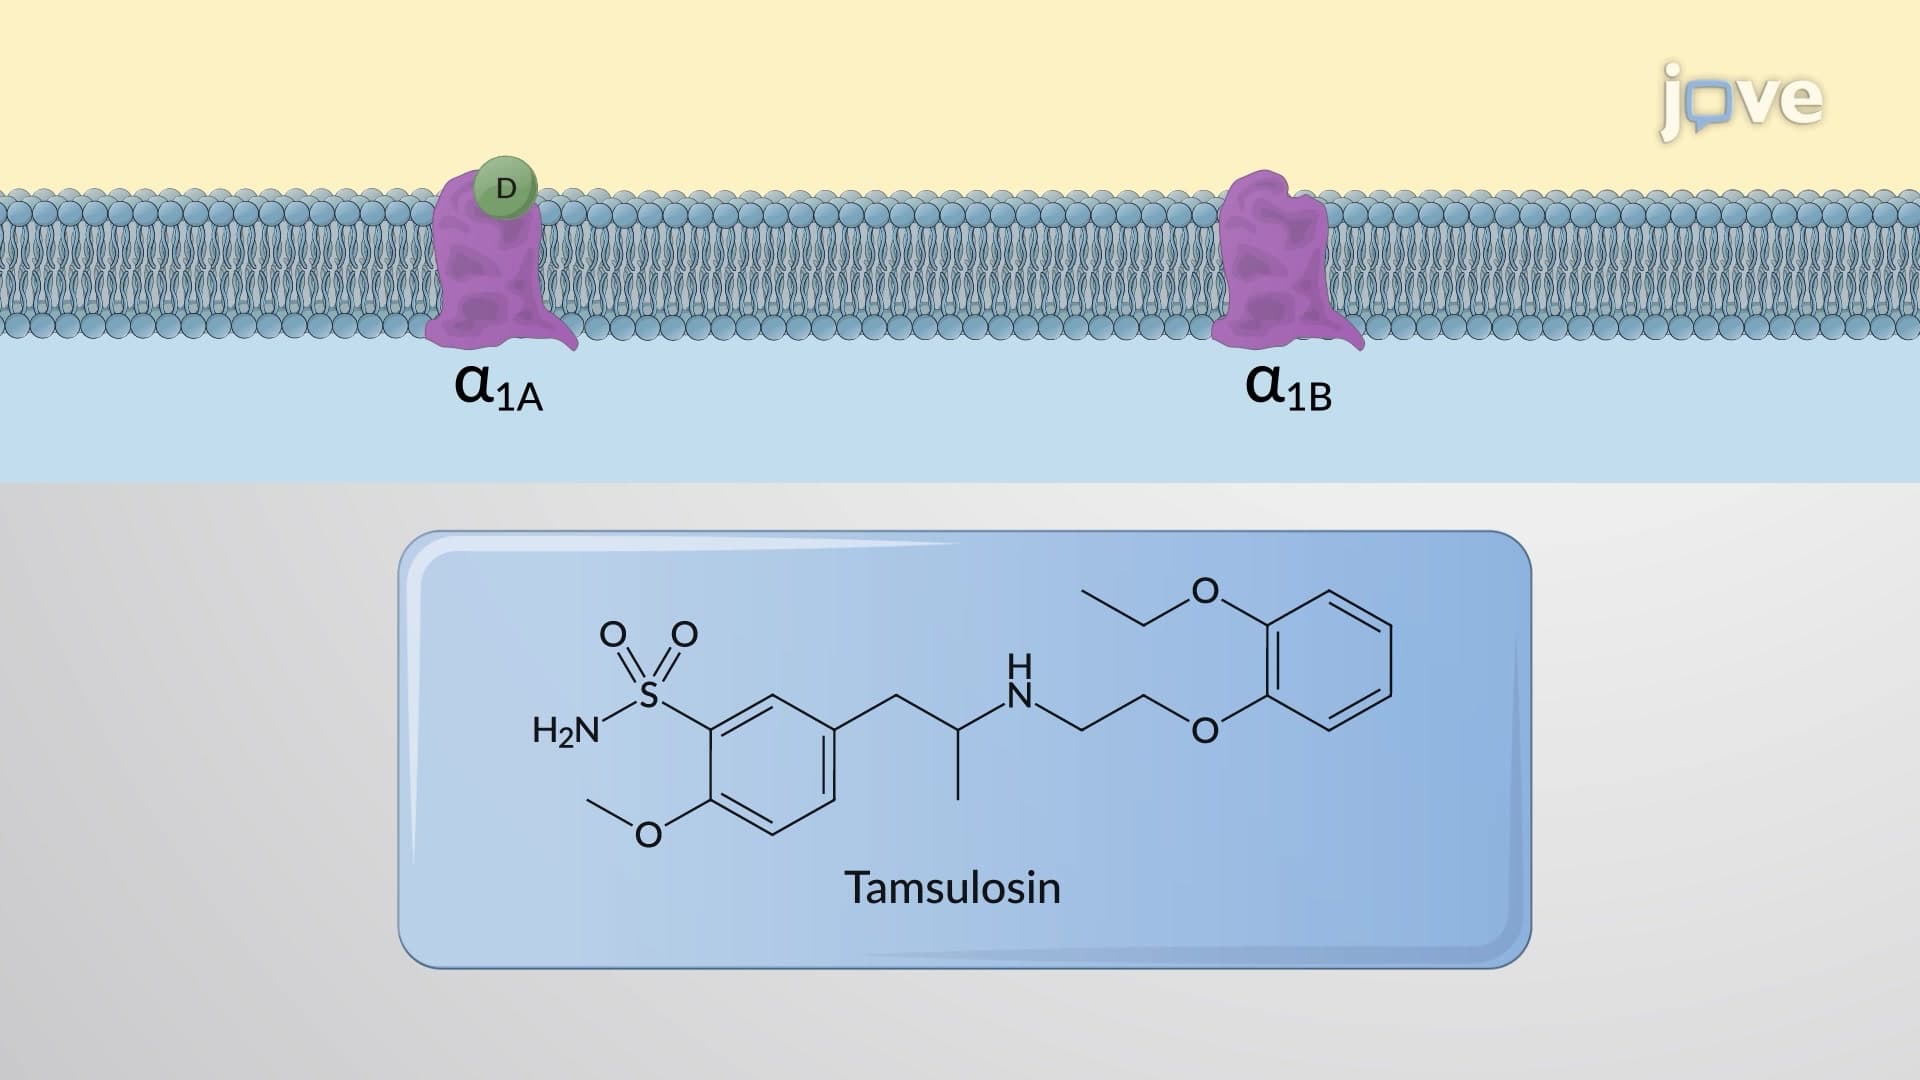
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
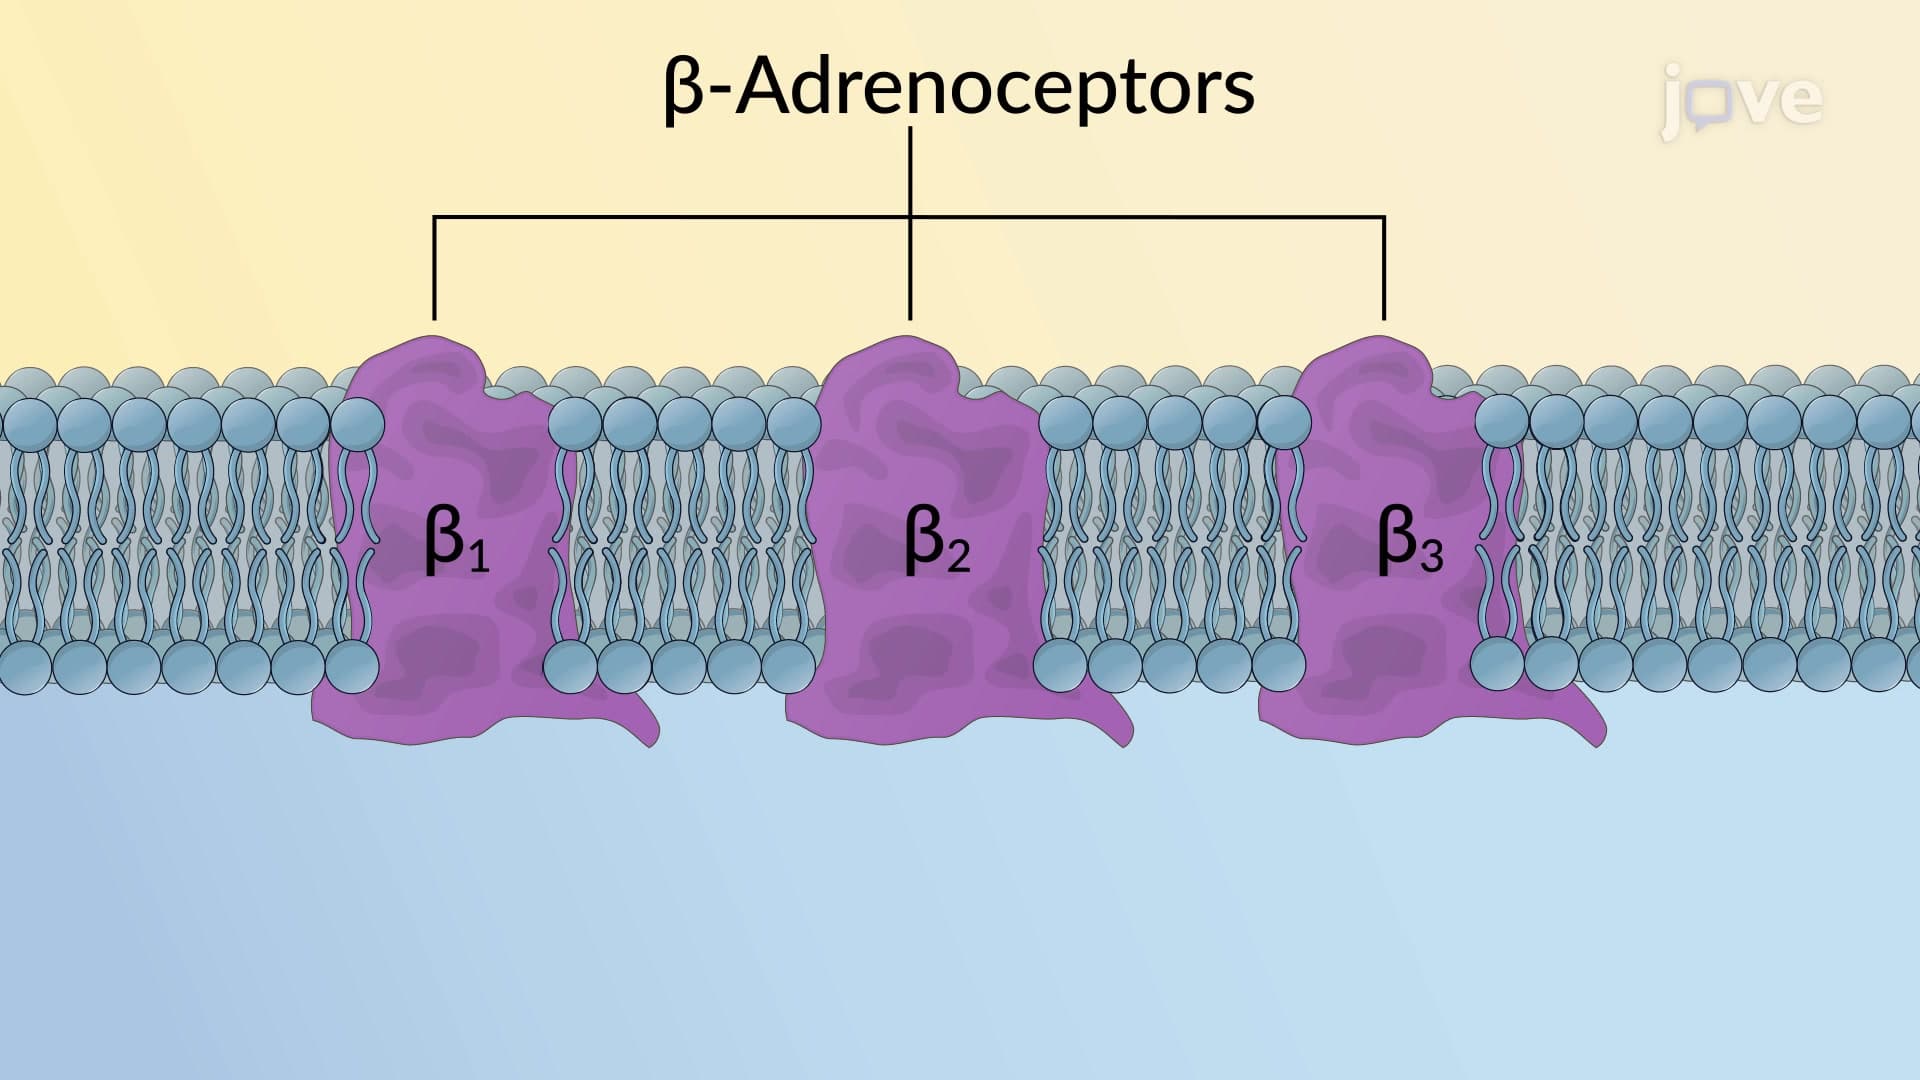
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:29
Pathophysiology of Cardiac Performance
 01:30
Acute Coronary Syndrome III: Diagnostic Studies