Related Experiment Video
Updated: Aug 20, 2026
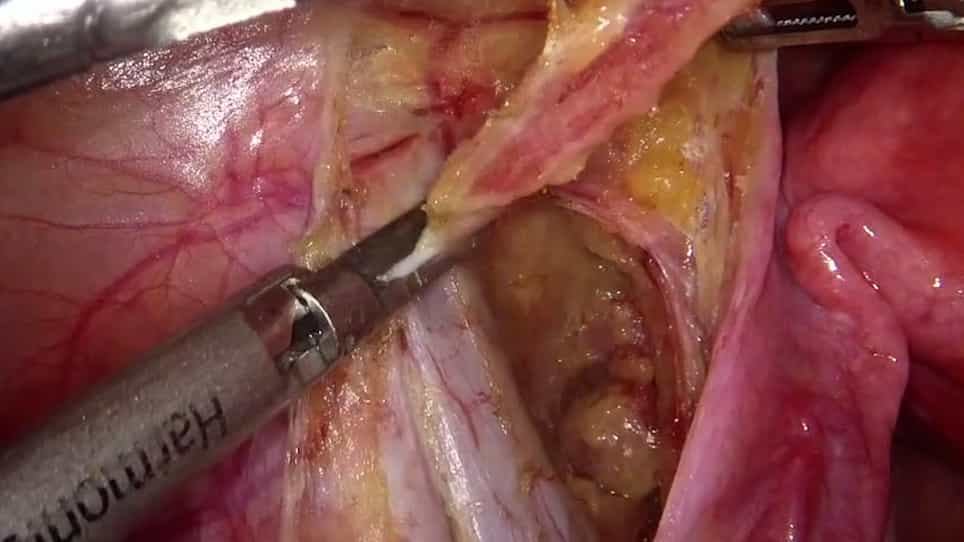
Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
Total laparoscopic radical hysterectomy with intraoperative sentinel node identification in patients with early
Antonio Gil-Moreno1, Berta Díaz-Feijoo, Isabel Roca
1Unit of Gynecologic Oncology, Department of Obstetrics and Gynecology, Hospital Materno-infantil Vall d'Hebron, Passeig Vall d'Hebron 119-129, E-08035 Barcelona, Spain. agil@cs.vhebron.es

Objectives:
To describe the feasibility and results of total laparoscopic radical hysterectomy with intraoperative sentinel lymph node identification in patients with early cervical cancer.
Methods:
Between March 2001 and October 2003, 12 patients with FIGO stage IA(2) (n = 1) or IB(1) (n = 11) cancer of the cervix underwent surgical treatment through the laparoscopic route. All patients underwent a laparoscopic sentinel node identification with preoperative lymphoscintigraphy (technetium-99 m colloid albumin injection around the tumor) and intraoperative lymphatic mapping with isosulfan blue dye and a laparoscopic gamma probe followed by systematic bilateral pelvic lymphadenectomy and laparoscopic type II (n = 5) or type III (n = 7) hysterectomy.
Results:
A mean of 2.5 sentinel nodes per patient (range 1-4) was detected, with a mean of 2.33 nodes per patient by gamma probe and a mean of 2 per patient after blue injection (combined detection rate 100%). The most frequent localization of the nodes was the interiliac region. Histopathologic examination of sentinel nodes including cytokeratin immunohistochemical analysis did not show metastasis. Microscopic nodal metastases were not found. The mean number of resected pelvic nodes was 18.6 per patient (range 10-28). The operation was performed entirely by laparoscopy in all patients and no case of laparotomy conversion was recorded. The mean duration of operation was 271 min (range 235-300), with a mean blood loss of 445 mL (range 240-800), and a mean length of stay of 5.25 days (range 3-10). No major intraoperative complications occurred. After a median follow-up of 20 months (range 5-34), all patients are free of disease.
Conclusions:
This study shows the feasibility of the combination of laparoscopic intraoperative sentinel node mapping and laparoscopic radical surgery in the context of minimally invasive surgery for the management of patients with early cervical cancer.
More Related Videos
 06:37
Multispectral Real-time Fluorescence Imaging for Intraoperative Detection of the Sentinel Lymph Node in Gynecologic Oncology
Published on: October 20, 2010
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023