Related Experiment Video
Updated: Aug 20, 2026
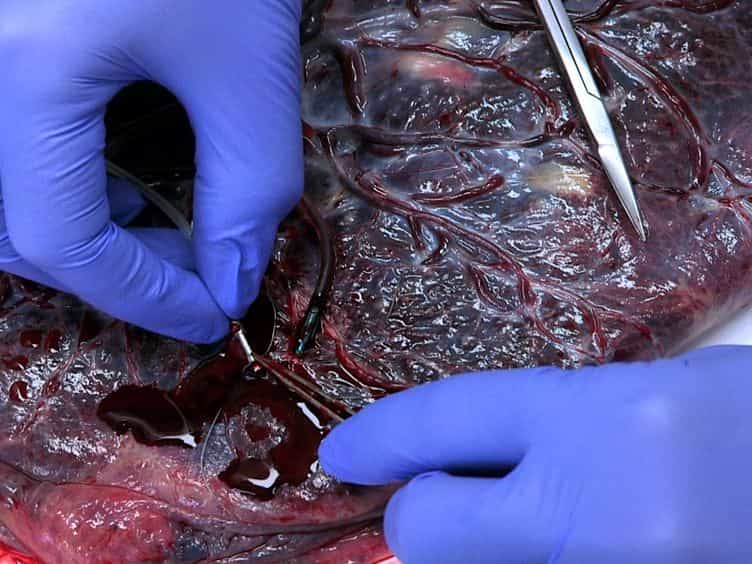

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
National Institute on Drug Abuse Conference report on placental proteins, drug transport, and fetal development
Pushpa V Thadani1, Jerome F Strauss, Sudhansu K Dey
1Division of Neuroscience and Behavioral Research. National Institute on Drug Abuse (NIDA), National Institutes of Health, 6001 Executive Boulevard, Room 4282, MSC 9555, Bethesda, MD 20892-9555, USA. pt24e@nih.gov

Abstract:
The use of illicit and licit drugs during pregnancy is a major public health concern because of potential adverse effects on the fetus and the risk to maternal health. Because the placenta is the primary link between the mother and the conceptus and is essential for the growth and survival of the fetus, abnormalities in placental formation and function resulting from drug use could have a major influence on pregnancy outcome. At present, little information is available on the impact of abused drugs on placental biology alone or in combination with other "host" factors (eg, stress, infections). This prompted the National Institute on Drug Abuse (NIDA) to convene a meeting of experts in placental biology to review cutting-edge research with the mission to translate existing information to new clinical and research initiatives in the drug abuse field. This report summarizes the presentations and research recommendations resulting from the workshop discussions.
More Related Videos


Related Concept Videos
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:29
Drug Distribution: Plasma Protein Binding
 01:07
Teratogenicity
 01:21
Factors Affecting Drug Response: Overview
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution