Related Experiment Video
Updated: Aug 18, 2026
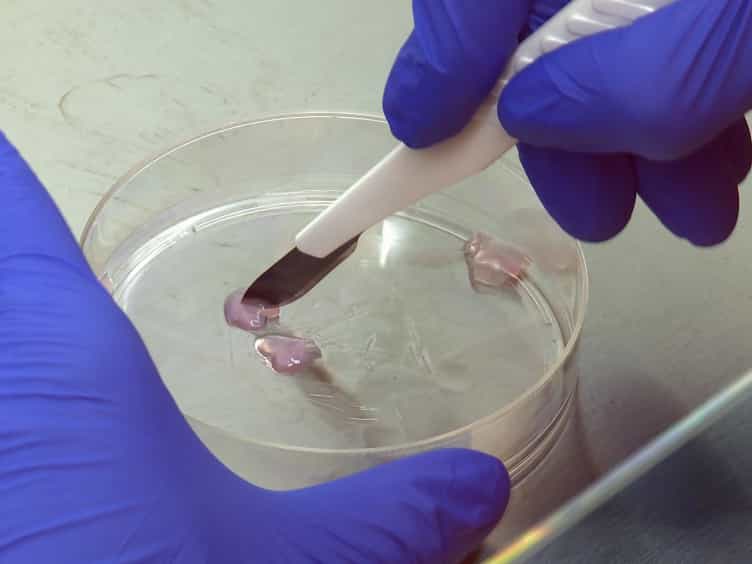
A 3D Human Lung Tissue Model for Functional Studies on Mycobacterium tuberculosis Infection
Published on: October 5, 2015
The relationship between disease pattern and disease burden by chest radiography, M. tuberculosis Load, and HIV
G Aderaye1, J Bruchfeld, G Assefa
1Dept. of Internal Medicine, Faculty of Medicine, Black Lion University Hospital, P.O. Box 2380, Addis Ababa, Ethiopia. getadera@hotmail.com

Background:
We evaluated the impact of HIV coinfection on the chest radiographic pattern and extent of disease and its relation to the load of Mycobacterium tuberculosis in Ethiopian out-patients with pulmonary tuberculosis.
Patients And Methods:
A total of 168 patients with cultureverified pulmonary tuberculosis had their chest X-rays (CXR) reviewed for the site, pattern, and extent of disease and the findings were correlated to (a) the mycobacterial culture count and bacillus load after sputum concentration and (b) the HIV status of the patients.
Results:
HIV-positive patients were less likely to have cavitary disease (p < 0.001) and more likely to have pleural effusion (p = 0.08), miliary (p < 0.05), and interstitial (p < 0.01) patterns. A total of 15 (9.2%) patients had normal chest X-rays. HIV-infected patients had a CXR classified as normal or with minimal involvement (p = 0.059) and a reduced mycobacterial colony count (p = 0.002) compared to HIV-negative patients. Middle and lower lung involvement were more common in HIV-positive patients.
Conclusion:
CXR findings in the setting of an underlying HIV infection tend to be more atypical and could present as either normal or with minimal involvement. In general, HIV-positive patients had lower colony count of M. tuberculosis than HIV-negative patients. Of particular interest is the finding of a large number of normal chest X-rays in HIV-infected patients. With the rising incidence of both tuberculosis and HIV infection in Ethiopia, the finding of a normal chest X-ray and a negative smear poses a challenge for the diagnosis of pulmonary tuberculosis.


Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:23
Tuberculosis