Related Experiment Video
Updated: Aug 20, 2026
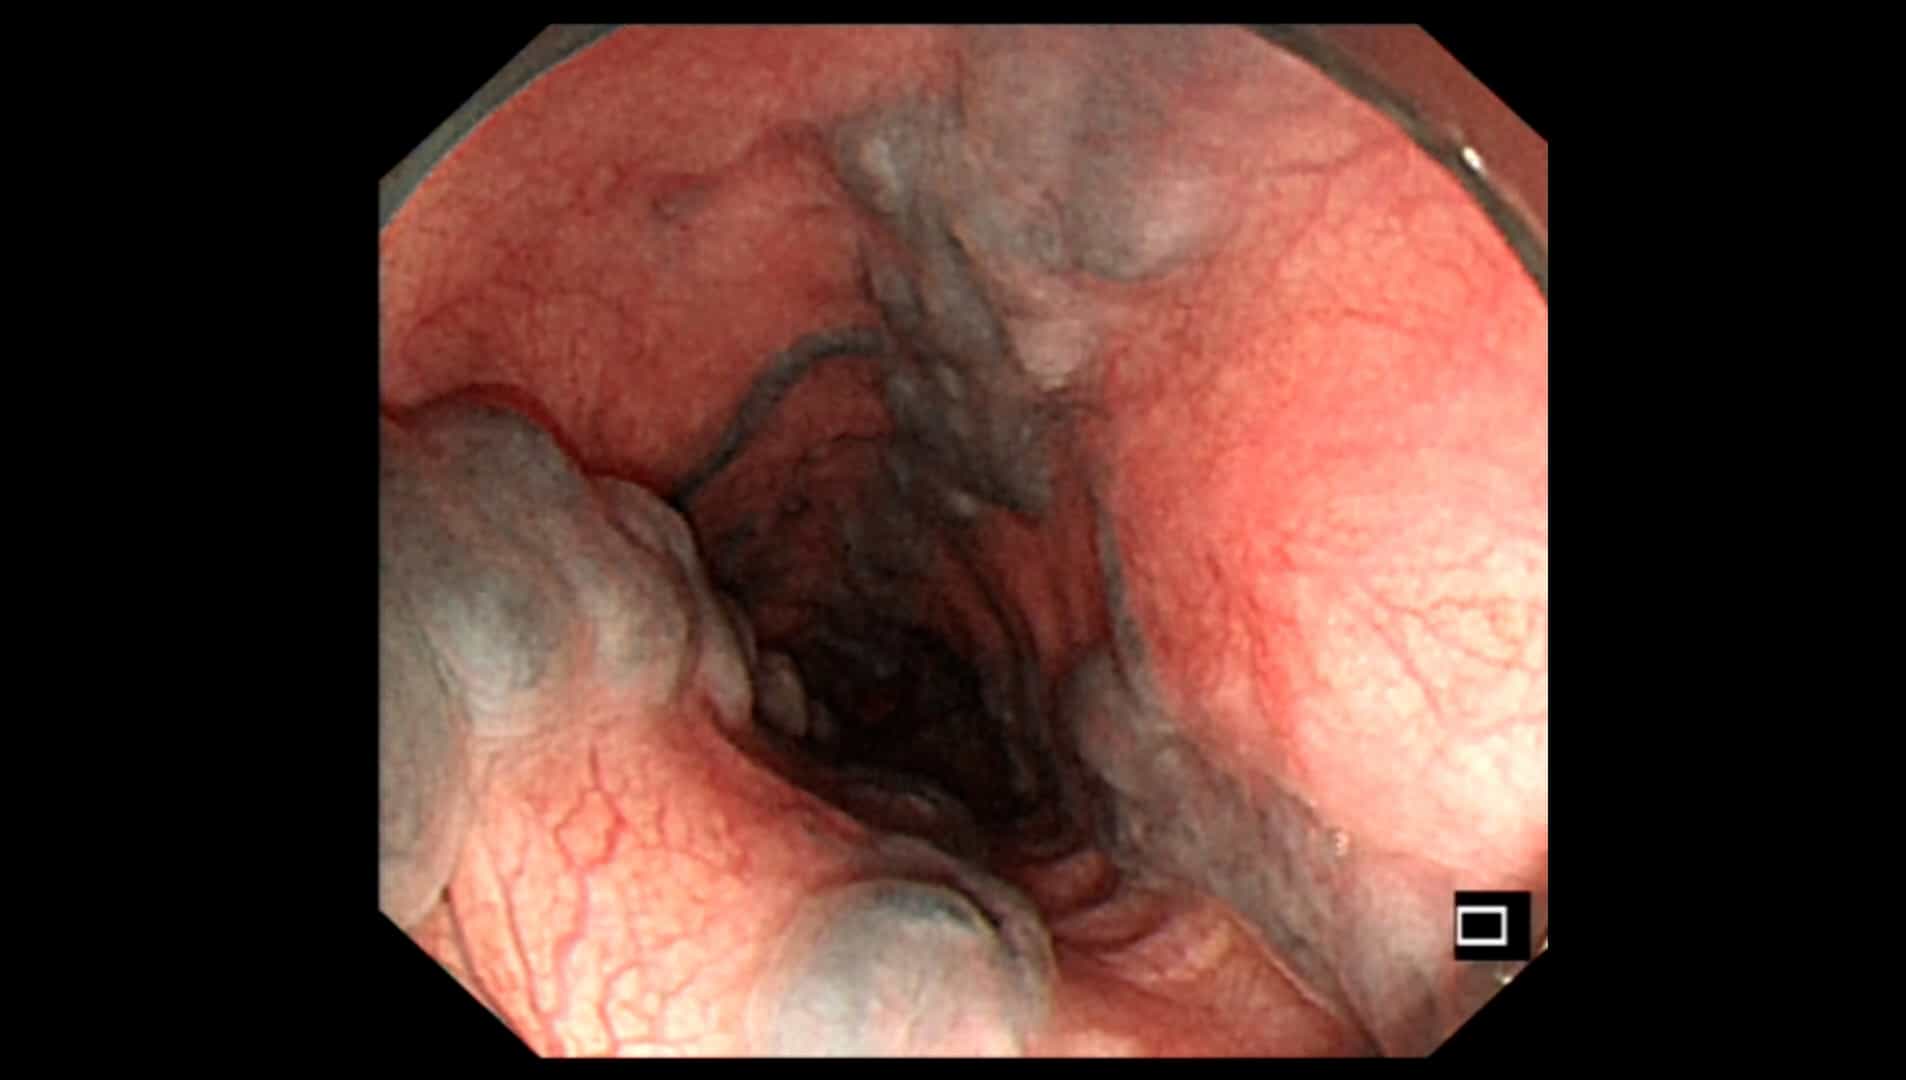
Underwater Endoscopic Injection Sclerotherapy for Gastroesophageal Varices
Published on: August 1, 2025
Optimal injection volume of epinephrine for endoscopic prevention of recurrent peptic ulcer bleeding
Chang-Hwan Park1, Soo-Jung Lee, Jeong-Ho Park
1Division of Gastroenterology, Department of Internal Medicine, Chonnam National University Medical School, 8 Hak-dong, Dong-ku, Gwangju 501-757, Korea.

Background:
Although the initial rate of hemostasis achieved by endoscopic epinephrine injection for peptic ulcer bleeding is high, bleeding recurs in 14.6% to 35.5% of patients. The aim of this study was to compare rates of recurrent bleeding after endoscopic injection of two different volumes of epinephrine in patients with peptic ulcer bleeding.
Methods:
A total of 72 patients with peptic ulcer with active bleeding or a non-bleeding visible vessel were randomly assigned to 15 to 25 mL or 35 to 45 mL injections of a 1:10,000 solution of epinephrine.
Results:
The two groups were similar with respect to all background variables. The mean volume of epinephrine injected was 19.4 mL: 95% CI [18.7, 20.1] in the 15 to 25 mL group and 41.1 mL: 95% CI [40.0, 42.2] in the 35 to 45 mL group. Initial hemostasis was achieved in 35 of 36 patients (97.2%) in the 15 to 25 mL group and in all 36 patients in the 35 to 45 mL group. The 35 to 45 mL volume was significantly more effective in preventing recurrent bleeding than the 15 to 25 mL volume (0% vs. 17.1%; p < 0.05). For ulcers in the gastric body, the 35 to 45 mL volume was significantly more effective in preventing recurrent bleeding than the 15 to 25 mL volume (0% vs. 31.6%; p = 0.003). For ulcers in other locations, including the gastric antrum and the duodenum, there were no significant differences in the rate of recurrent bleeding between the two groups.
Conclusions:
Injection of 35 to 45 mL of a 1:10,000 solution of epinephrine is more effective than injection of 15 to 25 mL of the same solution for prevention of recurrent bleeding from ulcers in the body of the stomach.


Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:13
Acid Suppressive Drugs for Peptic Ulcer Disease: Proton Pump Inhibitors
Gastric acid, a potent cocktail of hydrogen and chloride ions, is produced in specialized parietal cells within the...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management