Related Experiment Video
Updated: Aug 20, 2026
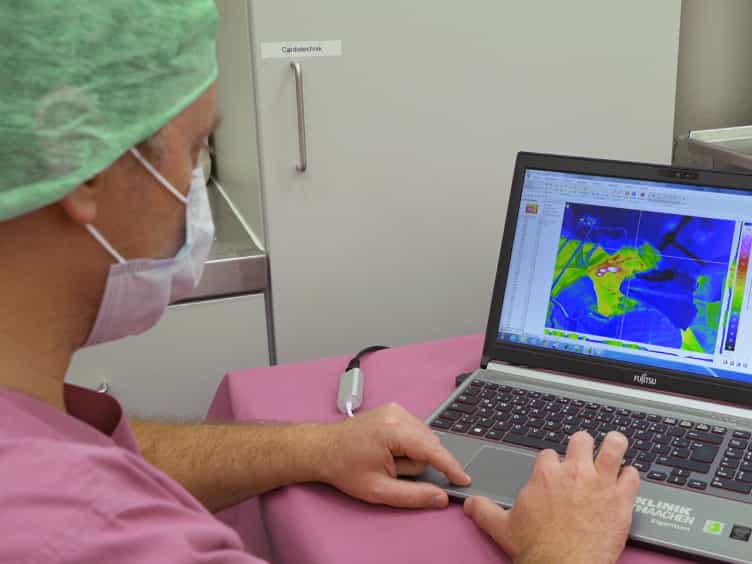

Assessment of Plasma Coagulation on Liver Tissue in a Large Animal Model In Vivo
Published on: August 4, 2018
Argon plasma coagulation for prevention of recurrent bleeding from GI angiodysplasias
Jorge Atilio Olmos1, Mariano Marcolongo, Valeria Pogorelsky
1Gastroenterology Service, Department of Internal Medicine, Hospital Italiano de Buenos Aires, Gascón 450, 1181 Buenos Aires, Argentina.

Background:
Angiodysplasia is a frequent cause of GI bleeding. Argon plasma coagulation has been shown to arrest bleeding, but its efficacy for prevention of recurrent bleeding has not been thoroughly evaluated. This study assessed the effectiveness and the safety of argon plasma coagulation for prevention of recurrent bleeding from GI angiodysplasias.
Methods:
A total of 60 patients with GI bleeding caused by angiodysplasia were included. The endoscopic intervention was considered successful if there was no further overt bleeding and if the Hb level stabilized. Recurrent bleeding was defined as any detectable bleeding episode (hematemesis, melena, or hematochezia) or a decrease in Hb level.
Results:
Overt bleeding was resolved, and the Hb level stabilized without transfusion or supplemental iron therapy in 50 of the 60 patients (83%) at a median follow-up of 18 months (range 6-38 months). In the subgroup of patients with anemia, mean Hb level increased from 8.6 g/dL (range 5.1-12.2 g/dL) to 12 g/dL (range 8.0-15.2 g/dL) ( p < 0.01). The estimated probability of remaining free of recurrent bleeding at 1- and 2-year follow-up was 86%: 95% CI [73%, 93%] and 80%: 95% CI [64%, 89%], respectively. Among 72 procedures, only two were associated with a complication (2.8%).
Conclusions:
Endoscopic argon plasma coagulation is both effective and safe for prevention of recurrent bleeding from GI angiodysplasia.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care