Related Experiment Video
Updated: Aug 17, 2026
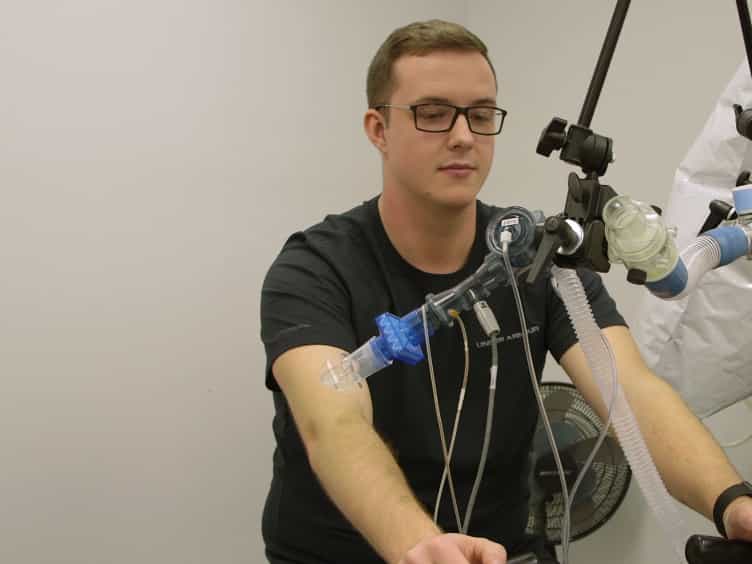
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Role of arterial blood gas abnormalities in oedema formation in COPD
Fisun Karadag1, Mehmet Polatli, Hatice Ozcan
1Adnan Menderes University, School of Medicine, Department of Chest Diseases, Aydin, Turkey. fisunkaradag@yahoo.com

Objective:
Renal and hormonal abnormalities, manifesting as oedema or hyponatraemia, are often seen in patients with COPD. The aim of this study was to investigate the effect of airflow obstruction and arterial blood gas abnormalities on oedema formation in COPD patients.
Methodology:
A total of 58 COPD patients hospitalized for treatment of COPD exacerbation were admitted to the study. Of these, 38 patients had peripheral oedema (group 1) and 20 patients had no oedema (group 2).
Results:
The mean age was 68 +/- 9 years in group 1 and 68 +/- 8 years in group 2. On the first day of admission, serum urea was 29.18 +/- 12.25 mg/dL and creatinine was 1.62 +/- 0.46 mg/dL in group 1, while urea was 15.50 +/- 4.59 mg/dL and creatinine was 1.07 +/- 0.10 mg/dL in group 2. Hyponatraemia occurred in five patients (13%) in group 1 and one patient (5%) in group 2. There was no difference in severity of airflow obstruction in the two groups; FEV1 was 44 +/- 15% of predicted and FEV1/FVC was 53 +/- 14 in group 1, while FEV1 was 45 +/- 16% of predicted and FEV1/FVC was 54 +/- 20 in group 2. There were statistically significant differences in pH (7.32 vs. 7.39; P= 0.013) and in PaCO2 (62 +/- 10 mmHg vs. 42 +/- 6; P= 0.048) for group 1 compared with group 2. PaO2 (62 +/- 17 mmHg vs. 82 +/- 27) and SaO2 (87 +/- 9%vs. 90 +/- 13) were found to be lower in group 1 compared with group 2 but the difference did not reach statistical significance.
Conclusion:
Alterations in pH and PaCO2 (respiratory acidosis and hypercapnia) appear to have more prominent roles than hypoxaemia in oedema formation in COPD patients.


Related Concept Videos
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...
 01:30
Acute Respiratory Failure-III
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:10
Atelectasis II: Pathophysiology
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:18
Pulmonary Edema II: Pathophysiology