Related Experiment Video
Updated: Aug 20, 2026
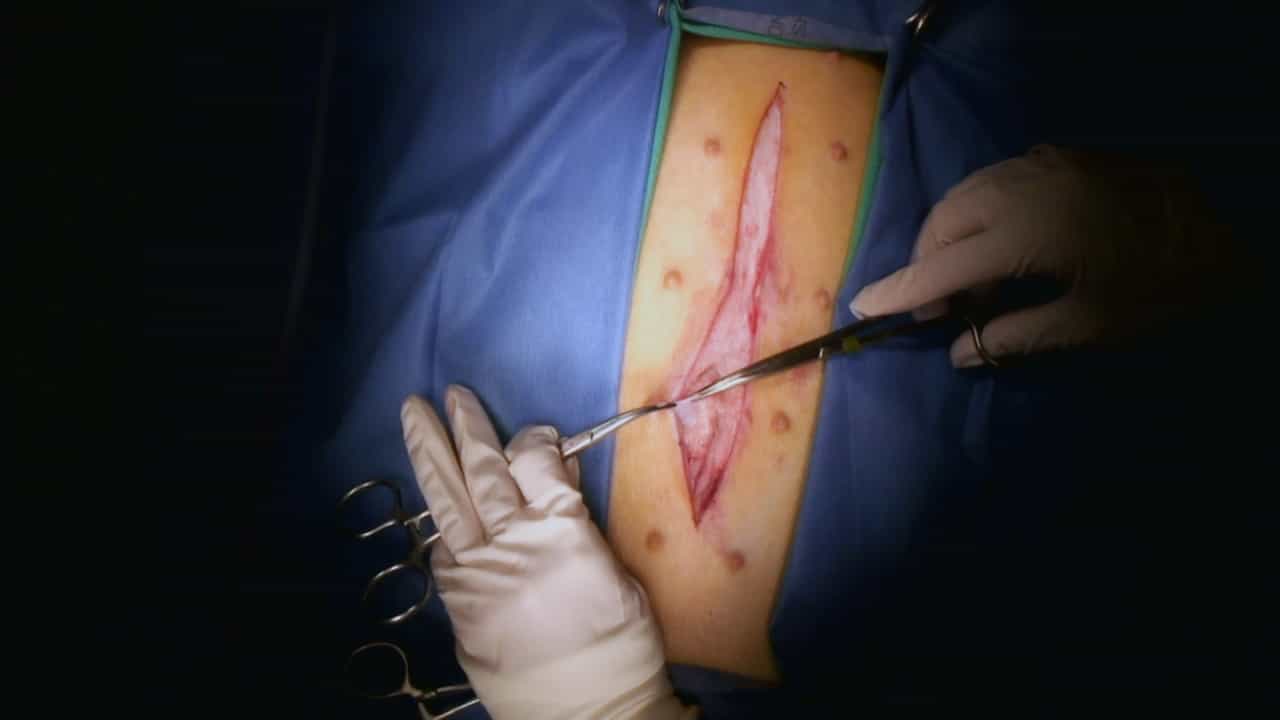
A Translational Surgical Porcine Model for Postoperative Intra-Abdominal Adhesion Formation
Published on: March 13, 2026
Gonadotropin-releasing hormone agonists for prevention of postoperative adhesions: an overview
1Institute for Medical Research and Education, Essen, Germany.

Abstract:
Adhesion formation is of major concern to the pelvic surgeon. Most patients develop postoperative adhesions regardless of whether the mode of access to the abdominal cavity is by laparoscopy or laparotomy. Infertility is related to adhesions in the pelvis in 15-20% of cases. Peritoneal adhesions are the main cause of mechanical bowel obstruction in 65-80% of cases and contribute to a large extent to health-care expenditures. To prevent the formation of postoperative adhesions, a variety of medications have been studied such as glucocorticoids, heparin, dextran 70, saline solution, antibiotics, promethazine, antihistamines, prostaglandin synthesis inhibitors, Ringer's lactate solution, calcium-channel blockers and barriers such as Interseed and Gore-Tex. Such adhesions can be induced when operating on myomas and endometriosis. Experimental and clinical studies have demonstrated various mechanisms of action to be involved in adhesion prevention when gonadotropin-releasing hormone agonists (GnRH-a) are used for treatment. The following have been demonstrated and suggested: (1) Hypoestrogenic condition was found in rats to be associated with decreased adhesion formation. This could be related to the influence on estrogen-dependent growth factors and growth modulators by reliable and constant inhibition of ovarian estradiol biosynthesis and secretion, but also non-competitive estrogen antagonism seems to play a role. (2) Treatment with GnRH-a reduces the growth hormone release stimulated by growth hormone-releasing hormone. (3) GnRH-a treatment influences neoangiogenesis by affecting vascular endothelial growth factor and basic fibroblastic growth factor. (4) GnRH-a reduce the basal rate of coagulatory processes. The frequency and extent of fibrin-generating and degrading processes are reduced. Activity of the plasminogen activating inhibitor is reduced, suggesting an improvement infibrinolytic reactivity. (5) GnRH-a use alters the vascular resistance index, pulsatility index and vascular peak velocity, and possible immune response. (6) Avoidance of bleeding can reduce fibrin and therefore decreases the matrix for invasion by fibroblasts. (7) GnRH-a reduce the degree of inflammation postoperatively. Adhesion prevention seems to be at its best when pre- and postoperative GnRH-a treatment is administered. At present, there are trends to operate without prior treatment with GnRH-a. Based upon the data available, it seems worthwhile to consider preoperative and also postoperative treatment with GnRH-a: pretreatment for at least 2-3 months seems to be indicated, and a similar time after operation, to block the events associated with adhesion formation.
Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:18
Adrenergic Agonists: Therapeutic Classification
Vasopressor or pressor agents: They increase blood pressure and function as cardiac stimulants. Examples include endogenous catecholamines (norepinephrine and dopamine) and synthetic agents (phenylephrine).
Bronchodilators: β2-agonists can relax bronchial muscles and widen airways. They are commonly used for treating obstructive pulmonary...