Related Experiment Video
Updated: Aug 20, 2026

Monitoring Cell-to-cell Transmission of Prion-like Protein Aggregates in Drosophila Melanogaster
Published on: March 12, 2018
Fatal familial insomnia with an unusual prion protein deposition pattern: an autopsy report with an experimental
K Sasaki1, K Doh-ura, Y Wakisaka
1Department of Neuropathology, Neurological Institute, Graduate School of Medical Sciences, Kyushu University, Fukuoka 812-8582, Japan. ksasaki@np.med.kyushu-u.ac.jp

Abstract:
We recently performed a post-mortem examination on a Japanese patient who had a prion protein gene mutation responsible for fatal familial insomnia (FFI). The patient initially developed cerebellar ataxia, but finally demonstrated insomnia, hyperkinetic delirium, autonomic signs and myoclonus in the late stage of the illness. Histological examination revealed marked neuronal loss in the thalamus and inferior olivary nucleus; however, prion protein (PrP) deposition was not proved in these lesions by immunohistochemistry. Instead, PrP deposition and spongiform change were both conspicuous within the cerebral cortex, whereas particular PrP deposition was also observed within the cerebellar cortex. The abnormal protease-resistant PrP (PrP(res)) molecules in the cerebral cortex of this case revealed PrP(res) type 2 pattern and were compatible with those of FFI cases, but the transmission study demonstrated that a pathogen in this case was different from that in a case with classical FFI. By inoculation with homogenate made from the cerebral cortex, the disease was transmitted to mice, and neuropathological features that were distinguishable from those previously reported were noted. These findings indicate the possibility that a discrete pathogen was involved in the disease in this case. We suggest that not only the genotype of the PrP gene and some other as yet unknown genetic factors, but also the variation in pathogen strains might be responsible for the varying clinical and pathological features of this disease.
Insights
Fatal familial insomnia (FFI) can present with varied symptoms due to potential prion strain variations. Post-mortem analysis revealed distinct neuropathological features and a transmissible agent different from classical FFI.
Area of Science:
- Neuroscience
- Pathology
- Genetics
Background:
- Fatal familial insomnia (FFI) is a rare, inherited prion disease.
- It is characterized by progressive insomnia, autonomic dysfunction, and neurological decline.
Observation:
- Post-mortem examination of a Japanese FFI patient revealed cerebellar ataxia progressing to insomnia, delirium, and myoclonus.
- Histopathology showed neuronal loss in the thalamus and inferior olivary nucleus, with prion protein (PrP) deposition and spongiform changes in the cerebral and cerebellar cortex.
Findings:
- Prion protein (PrP) deposition was type 2, consistent with FFI.
- Transmission studies in mice revealed distinct neuropathological features, suggesting a different pathogen strain than classical FFI.
- The patient's prion protein gene mutation was linked to FFI.
Implications:
- This case suggests that variations in prion pathogen strains, alongside genetic factors, may contribute to the diverse clinical and pathological presentations of FFI.
- Further research into prion strain diversity is crucial for understanding and potentially treating FFI.

Related Concept Videos
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
03:03Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
 01:23
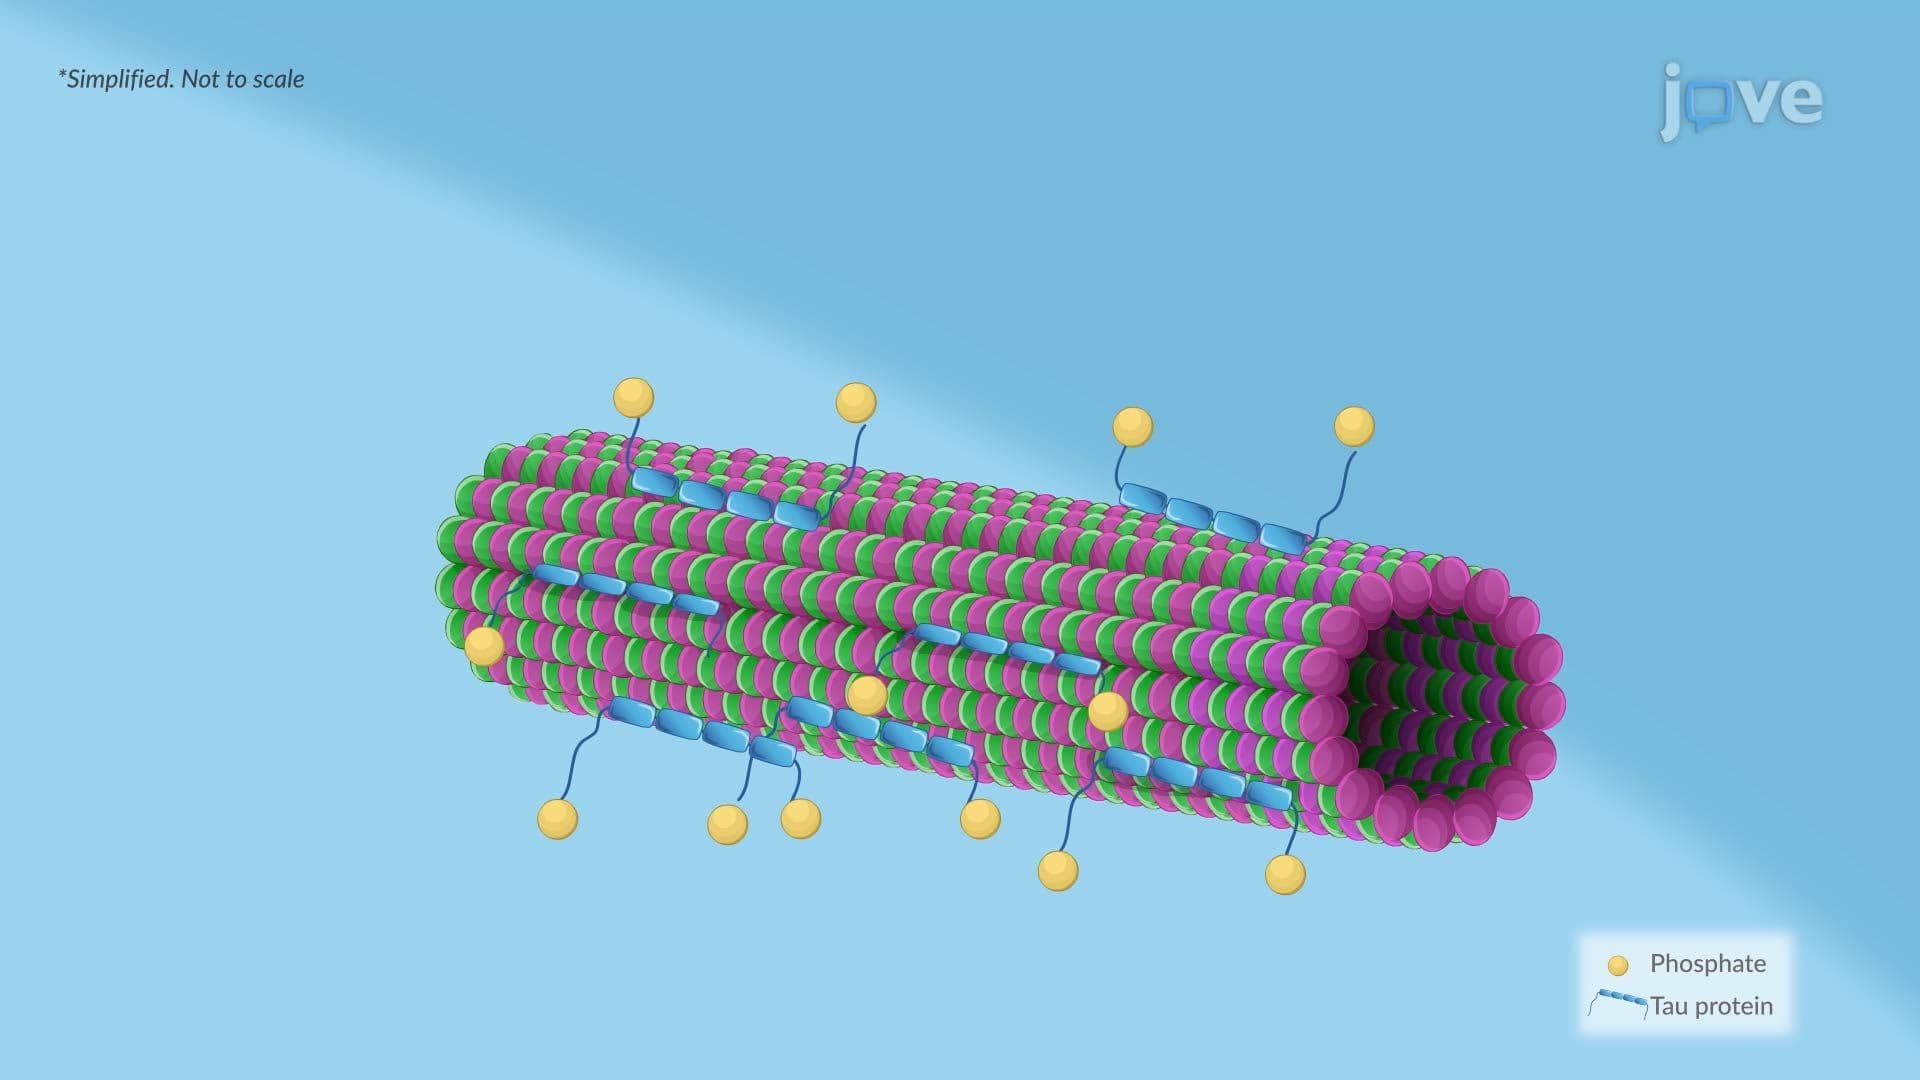
Alzheimer Disease ll: Pathophysiology
 01:21
Huntington Disease l: Introduction