Related Experiment Video
Updated: Aug 20, 2026
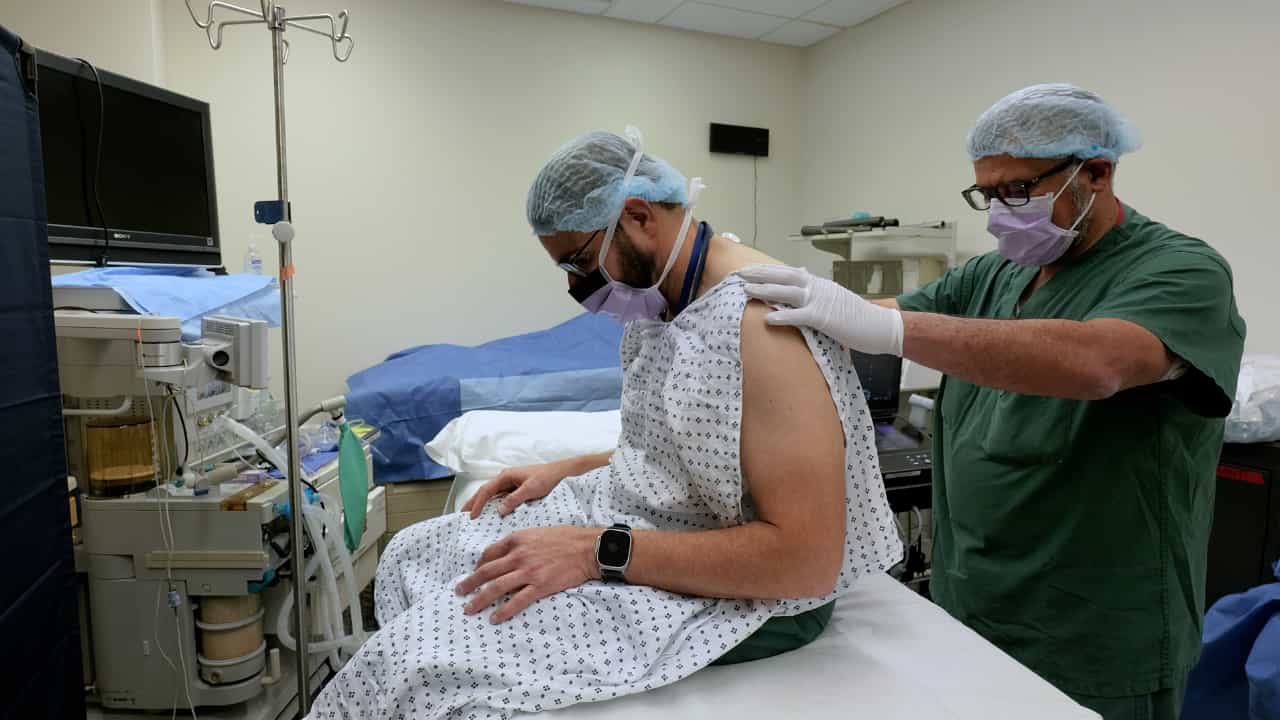

Spinal Sonography for Ultrasound-Guided Lumbar Neuraxial Anesthesia
Published on: January 31, 2025
The effect of position on sacral spread of epidural analgesia
R Griffin1, M Barklamb, F Reynolds
1Department of Anaesthetics, St. Thomas' Hospital, Lambeth Palace Road, London SE1 7EH, UK.

In parturients, extension of epidural analgesia to include the sacral roots is necessary for adequate analgesia during the second stage of labour and for vacuum extraction and forceps delivery. There is clinical evidence that if the sitting position is adopted after local anaesthetic administration, it impairs the sacral spread of analgesia. An in vitro model representing the lumbar spinal canal has been used to demonstrate how, in the vertical position, a CSF plug can prevent downward spread of local anaesthetic. With the model tilted 25 degrees to the horizontal and also in the full horizontal position downward spread occurs. The effect of a 25 degrees head up tilt on sacral spread of epidural analgesia was compared clinically with the horizontal position. Women requesting epidural analgesia during labour were randomly allocated to receive the first epidural dose either with the head end of the bed tilted 25 degrees head up (n = 30) or remaining horizontal (n = 30). All epidurals were sited at L3/4, a test dose of 2 ml of 0.5% bupivacaine was followed by a main dose of 6 ml of 0.5% bupivacaine. Sacral sensory blockade was greater in the head up group. The difference was significant on the left side (P < 0.05) at 15, 20, and 30 minutes after the main dose. There were more patients with blocks extending to S5 (on either the left or right sides) in the head up group at 15, 20 and 30 minutes (P < 0.05 at 20 and 30 minutes on left side).
In parturients, extension of epidural analgesia to include the sacral roots is necessary for adequate analgesia during the second stage of labour and for vacuum extraction and forceps delivery. There is clinical evidence that if the sitting position is adopted after local anaesthetic administration, it impairs the sacral spread of analgesia. An in vitro model representing the lumbar spinal canal has been used to demonstrate how, in the vertical position, a CSF plug can prevent downward spread of local anaesthetic. With the model tilted 25 degrees to the horizontal and also in the full horizontal position downward spread occurs. The effect of a 25 degrees head up tilt on sacral spread of epidural analgesia was compared clinically with the horizontal position. Women requesting epidural analgesia during labour were randomly allocated to receive the first epidural dose either with the head end of the bed tilted 25 degrees head up (n = 30) or remaining horizontal (n = 30). All epidurals were sited at L3/4, a test dose of 2 ml of 0.5% bupivacaine was followed by a main dose of 6 ml of 0.5% bupivacaine. Sacral sensory blockade was greater in the head up group. The difference was significant on the left side (P < 0.05) at 15, 20, and 30 minutes after the main dose. There were more patients with blocks extending to S5 (on either the left or right sides) in the head up group at 15, 20 and 30 minutes (P < 0.05 at 20 and 30 minutes on left side).
Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:30
Local Anesthetics: Clinical Application as Surface, Infiltration, and Conduction Block Anesthesia