Related Experiment Video
Updated: Aug 20, 2026


Technical Considerations and Approach to Redo Foregut Surgery
Published on: September 22, 2023
Impact of hiatal hernia on histological pattern of non-erosive reflux disease
Anthie Gatopoulou1, Konstantinos Mimidis, Alexandra Giatromanolaki
1Endoscopy Unit, Democritus University of Thrace, Dragana, GR-68100 Alexandroupolis, Greece. gatop@otenet.gr <gatop@otenet.gr>

Background:
Hiatus hernia (HH) has major pathophysiological effects favoring gastroesophageal reflux and hence contributing to esophageal mucosa injury, especially in patients with severe gastroesophageal disease. However, prospective studies investigating the impact of HH on the esophageal mucosa in non-erosive reflux disease (NERD) are lacking. This study evaluated the association between the presence of (HH) and the histological findings in symptomatic patients with NERD.
Methods:
Fifty consecutive patients with gastroesophageal reflux disease (GERD) were enrolled. After conventional endoscopy, Lugol solution was applied and biopsy specimens were obtained. Histological parameters including basal zone hyperplasia, papillary length and cellular infiltration were evaluated. The chi-square test with Yates' correlation was used for comparing discrete parameters between groups. However, Fisher's exact probability test was used where the expected frequencies were lower than 5. Wilcoxon's test for unpaired samples was preferred in cases of semi-quantitative parameters.
Results:
The presence of HH along with more severe findings (0.01
Conclusion:
The presence of HH is correlated with more severe endoscopy findings, and predisposes for severe histological abnormality in cases of NERD.

Related Concept Videos
 01:25
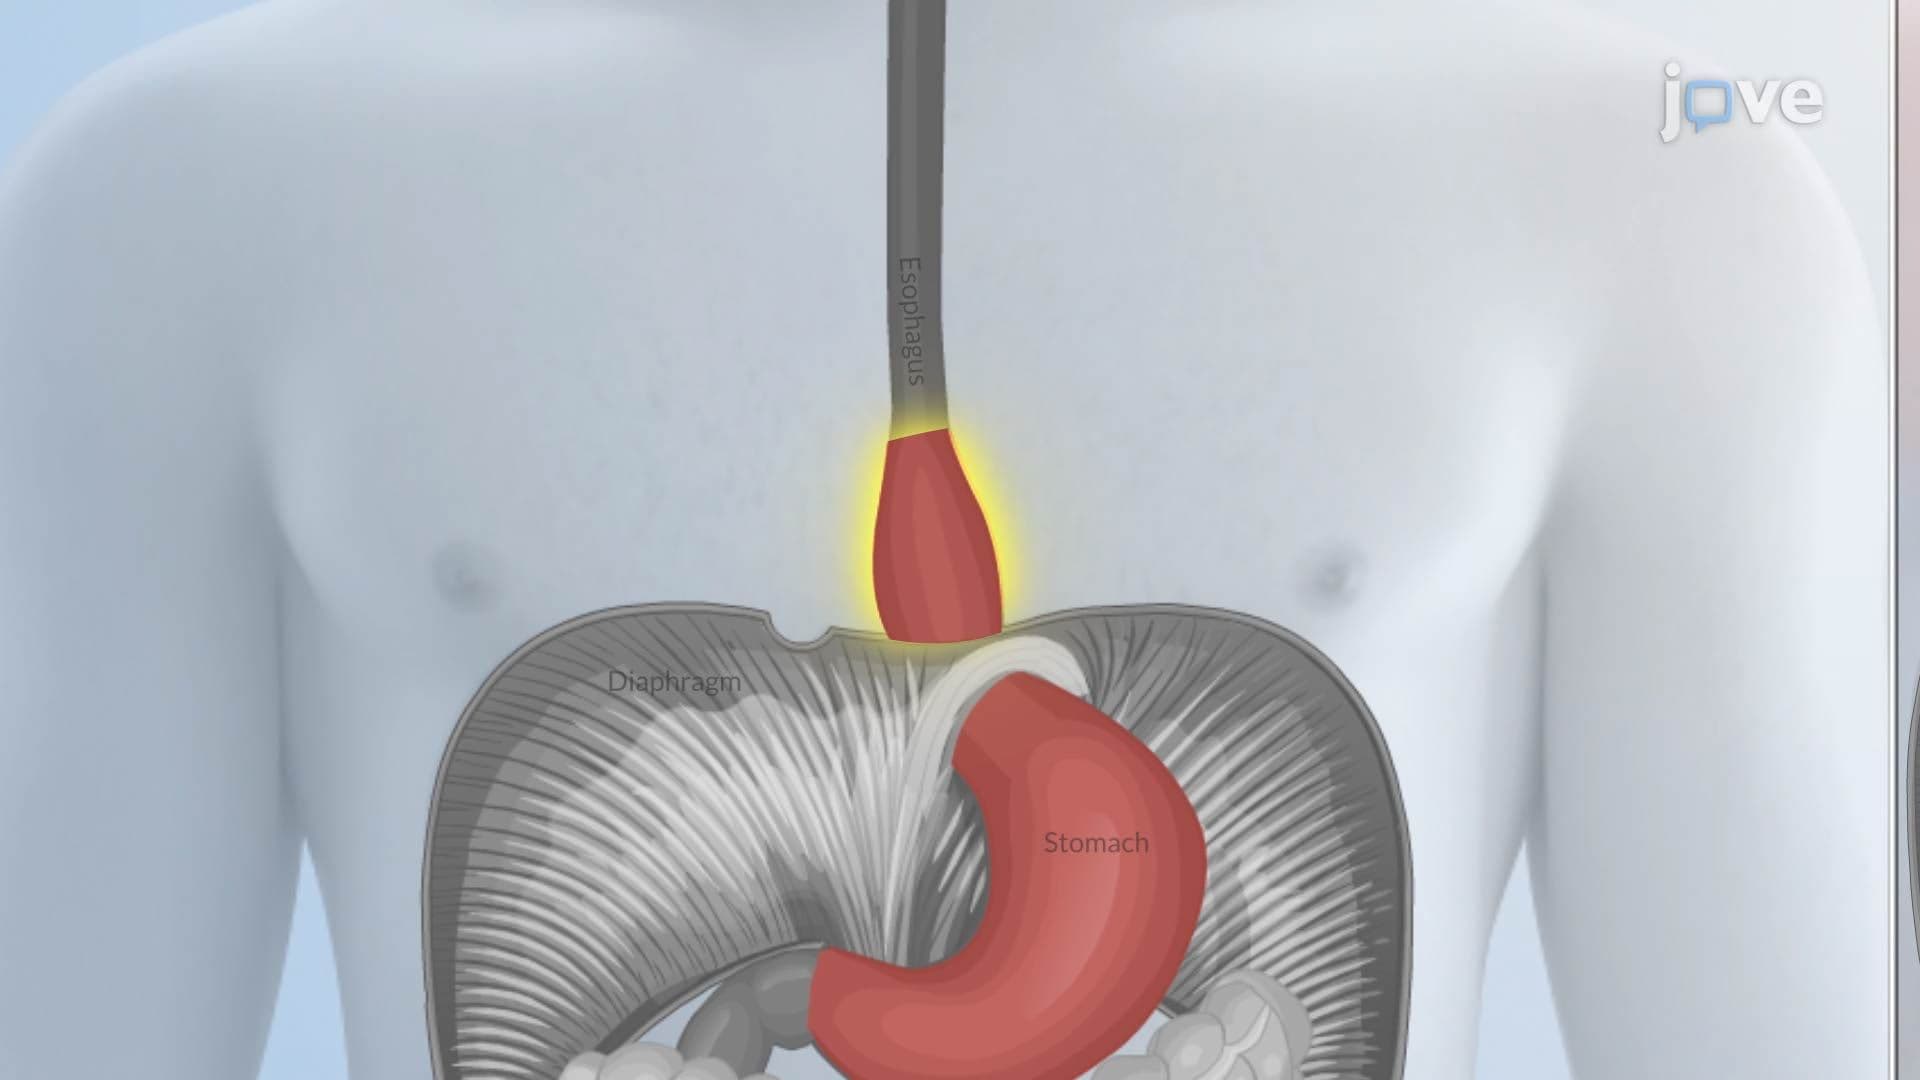
Hiatal Hernia
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:26
Gastritis II: Pathophysiology
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:24
Peptic Ulcer Disease II: Pathophysiology