Related Experiment Video
Updated: Aug 11, 2026

Substernal Thyroid Biopsy Using Endobronchial Ultrasound-guided Transbronchial Needle Aspiration
Published on: November 10, 2014
Thyroid disorders associated with pregnancy: etiology, diagnosis, and management
1Department of Medicine, University of Wales College of Medicine, Cardiff, Wales, UK. lazarus@cf.ac.ik

Pregnancy has an effect on thyroid economy with significant changes in iodine metabolism, serum thyroid binding proteins, and the development of maternal goiter especially in iodine-deficient areas. Pregnancy is also accompanied by immunologic changes, mainly characterized by a shift from a T helper-1 (Th1) lymphocyte to a Th2 lymphocyte state. Thyroid peroxidase antibodies are present in 10% of women at 14 weeks' gestation, and are associated with (i) an increased pregnancy failure (i.e. abortion), (ii) an increased incidence of gestational thyroid dysfunction, and (iii) a predisposition to postpartum thyroiditis. Thyroid function should be measured in women with severe hyperemesis gravidarum but not in every patient with nausea and vomiting during pregnancy. Graves hyperthyroidism during pregnancy is best managed with propylthiouracil administered throughout gestation. Thyroid-stimulating hormone-receptor antibody measurements at 36 weeks' gestation are predictive of transient neonatal hyperthyroidism, and should be checked even in previously treated patients receiving thyroxine. Postpartum exacerbation of hyperthyroidism is common, and should be evaluated in women with Graves disease not on treatment. Radioiodine therapy in pregnancy is absolutely contraindicated. Hypothyroidism (including subclinical hypothyroidism) occurs in about 2.5% of pregnancies, and may lead to obstetric and neonatal complications as well as being a cause of infertility. During the last few decades, evidence has been presented to underpin the critical importance of adequate fetal thyroid hormone levels in order to ensure normal central and peripheral nervous system maturation. In iodine-deficient and iodine-sufficient areas, low maternal circulating thyroxine levels have been associated with a significant decrement in child IQ and development. These data suggest the advisability of further evaluation for a screening program early in pregnancy to identify women with hypothyroxinemia, and the initiation of prompt treatment for its correction. Hypothyroidism in pregnancy is treated with a larger dose of thyroxine than in the nonpregnant state. Postpartum thyroid dysfunction (PPTD) occurs in 50% of women found to have thyroid peroxidase antibodies in early pregnancy. The hypothyroid phase of PPTD is symptomatic and requires thyroxine therapy. A high incidence (25-30%) of permanent hypothyroidism has been noted in these women. Women having transient PPTD with hypothyroidism should be monitored frequently, as there is a 50% chance of these patients developing hypothyroidism during the next 7 years.
Pregnancy has an effect on thyroid economy with significant changes in iodine metabolism, serum thyroid binding proteins, and the development of maternal goiter especially in iodine-deficient areas. Pregnancy is also accompanied by immunologic changes, mainly characterized by a shift from a T helper-1 (Th1) lymphocyte to a Th2 lymphocyte state. Thyroid peroxidase antibodies are present in 10% of women at 14 weeks' gestation, and are associated with (i) an increased pregnancy failure (i.e. abortion), (ii) an increased incidence of gestational thyroid dysfunction, and (iii) a predisposition to postpartum thyroiditis. Thyroid function should be measured in women with severe hyperemesis gravidarum but not in every patient with nausea and vomiting during pregnancy. Graves hyperthyroidism during pregnancy is best managed with propylthiouracil administered throughout gestation. Thyroid-stimulating hormone-receptor antibody measurements at 36 weeks' gestation are predictive of transient neonatal hyperthyroidism, and should be checked even in previously treated patients receiving thyroxine. Postpartum exacerbation of hyperthyroidism is common, and should be evaluated in women with Graves disease not on treatment. Radioiodine therapy in pregnancy is absolutely contraindicated. Hypothyroidism (including subclinical hypothyroidism) occurs in about 2.5% of pregnancies, and may lead to obstetric and neonatal complications as well as being a cause of infertility. During the last few decades, evidence has been presented to underpin the critical importance of adequate fetal thyroid hormone levels in order to ensure normal central and peripheral nervous system maturation. In iodine-deficient and iodine-sufficient areas, low maternal circulating thyroxine levels have been associated with a significant decrement in child IQ and development. These data suggest the advisability of further evaluation for a screening program early in pregnancy to identify women with hypothyroxinemia, and the initiation of prompt treatment for its correction. Hypothyroidism in pregnancy is treated with a larger dose of thyroxine than in the nonpregnant state. Postpartum thyroid dysfunction (PPTD) occurs in 50% of women found to have thyroid peroxidase antibodies in early pregnancy. The hypothyroid phase of PPTD is symptomatic and requires thyroxine therapy. A high incidence (25-30%) of permanent hypothyroidism has been noted in these women. Women having transient PPTD with hypothyroidism should be monitored frequently, as there is a 50% chance of these patients developing hypothyroidism during the next 7 years.
Related Concept Videos
 01:20
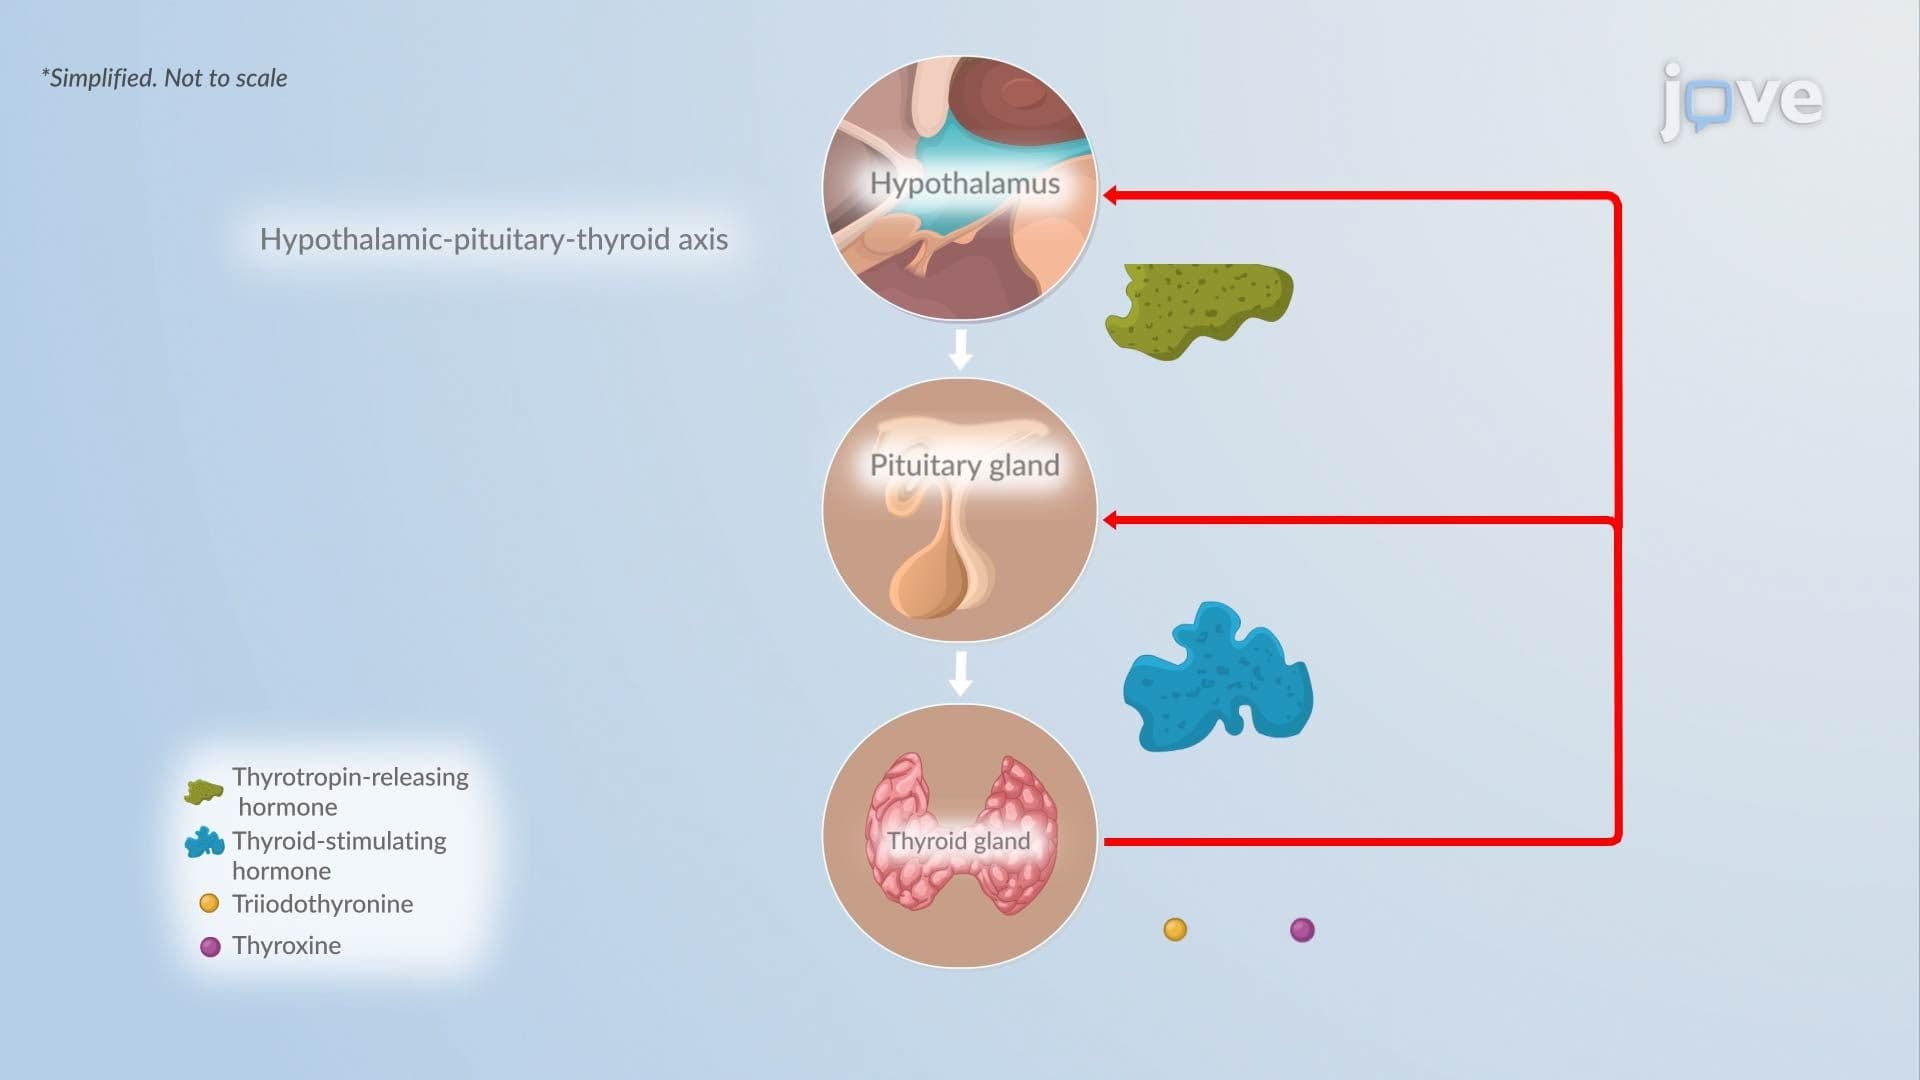
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology