Related Experiment Video
Updated: Aug 20, 2026
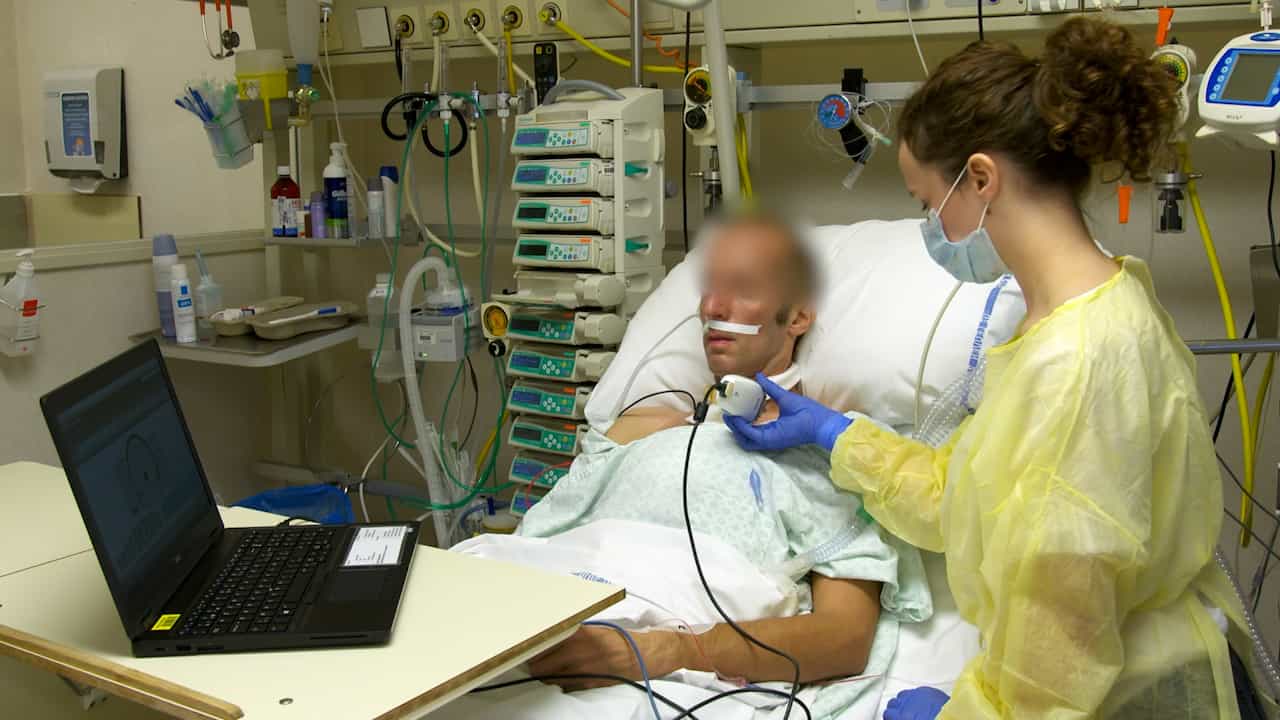

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Transtracheal high-flow insufflation supports spontaneous respiration in chronic respiratory failure
Thomas Brack1, Olivier Senn, Erich W Russi
1Division of Pulmonary Medicine, University Hospital, Zürich, Switzerland. thomas.brack@usz.ch

Study Objectives:
Transtracheal insufflation of oxygen-enriched air at a high flow rate has been proposed to support ventilation. The purpose of this study was to investigate the physiologic effects of high-flow insufflation unobtrusively with a respiratory inductive plethysmograph in patients with chronic respiratory failure. Using a respiratory inductive plethysmograph also permitted monitoring of end-expiratory lung volume, and respiratory variables could be quantified independently of the tracheal bias flow.
Design:
Prospective randomized comparison of low-flow vs high-flow transtracheal insufflation.
Setting:
Pulmonary division of a tertiary teaching hospital.
Patients:
Fourteen spontaneously breathing outpatients with chronic hypoxemic respiratory failure carrying a transtracheal catheter for long-term oxygen therapy.
Interventions And Measurements:
Oxygen-enriched air (fraction of inspired oxygen, 0.37) at 15 L/min and oxygen at 1.5 L/min were transtracheally administered for 1 h each. The breathing pattern and the end-expiratory lung volume were monitored by inductive plethysmography along with pulse oximetry and transcutaneous PCO2. Arterial blood gases were also analyzed at the end of the hour of both low-flow and high-flow insufflation.
Results:
High-flow insufflation decreased the mean (+/- SEM) minute ventilation (Ve) by 20% from 8.37 +/- 0.49 to 6.66 +/- 0.57 L/min, the mean respiratory rate from 19.2 +/- 0.9 to 15.7 +/- 1.0 breaths/min, while mean expiratory time increased from 2.0 +/- 0.1 to 2.8 +/- 0.2 s, and end-expiratory lung volume decreased by 0.55 +/- 0.15 L compared to low-flow oxygen insufflation (p < 0.05 for all comparisons). Mean arterial and transcutaneous PCO2 decreased from 45 +/- 1 to 43 +/- 1 mm Hg and from 54 +/- 2 to 53 +/- 2 mm Hg, respectively (p < 0.05 in both instances), while arterial PaO2 and oxygen saturation did not change.
Conclusions:
High-flow transtracheal insufflation of oxygen-enriched air assists ventilation by reducing Ve without compromising gas exchange and by reducing end-expiratory lung volume, possibly through the reversal of dynamic hyperinflation.

Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...