Metabolic consequences of peritoneal dialysis
Related Experiment Video
Updated: Aug 20, 2026
Surgical Techniques for Catheter Placement and 5/6 Nephrectomy in Murine Models of Peritoneal Dialysis
Published on: July 19, 2018
1Department of Internal Medicine, Section on Nephrology, Wake Forest University School of Medicine, Medical Center Boulevard, Winston-Salem, NC 27157-1053, USA. jburkart@wfubmc.edu

Abstract:
Optimization of the peritoneal dialysis (PD) prescription includes attempts to normalize the patient's blood pressure and extracellular volume. To do so, one must utilize crystalloid or colloid osmotic agents to achieve ultrafiltration. These osmotic agents are systemically absorbed and thus have both potential benefits and adverse effects. With glucose-based dialysate solutions, the average patient absorbs 300-450 kcal of glucose per day on either continuous ambulatory peritoneal dialysis (CAPD) or the cycler. The amount of glucose absorbed varies based on peritoneal transport characteristics, prescription, and tonicity of fluids used. Alternative osmotic agents such as amino acids and macromolecular solutions, including polypeptides and polyglucose (icodextrin) solutions, have a different rate of systemic absorption and thus a different caloric load profile. In addition, there are protein losses that average about 10 g/day with glucose-based solutions and glucose losses with either amino acid or icodextrin dialysate solutions. There are also potential advantages of these alternative solutions with regard to ultrafiltration. Glucose-based solutions require the development of significant crystalloid osmotic forces, which are dissipated as glucose is absorbed systemically. In contrast, macromolecular solutions achieve ultrafiltration via differences in colloid osmotic pressure, and the absorption of these agents is of a lesser magnitude than glucose-based solutions. Further research is needed to determine other potential risks and benefits of these alternative dialysate solutions.

Related Concept Videos
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:30
Peritoneal Dialysis I: Introduction and Procedure
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
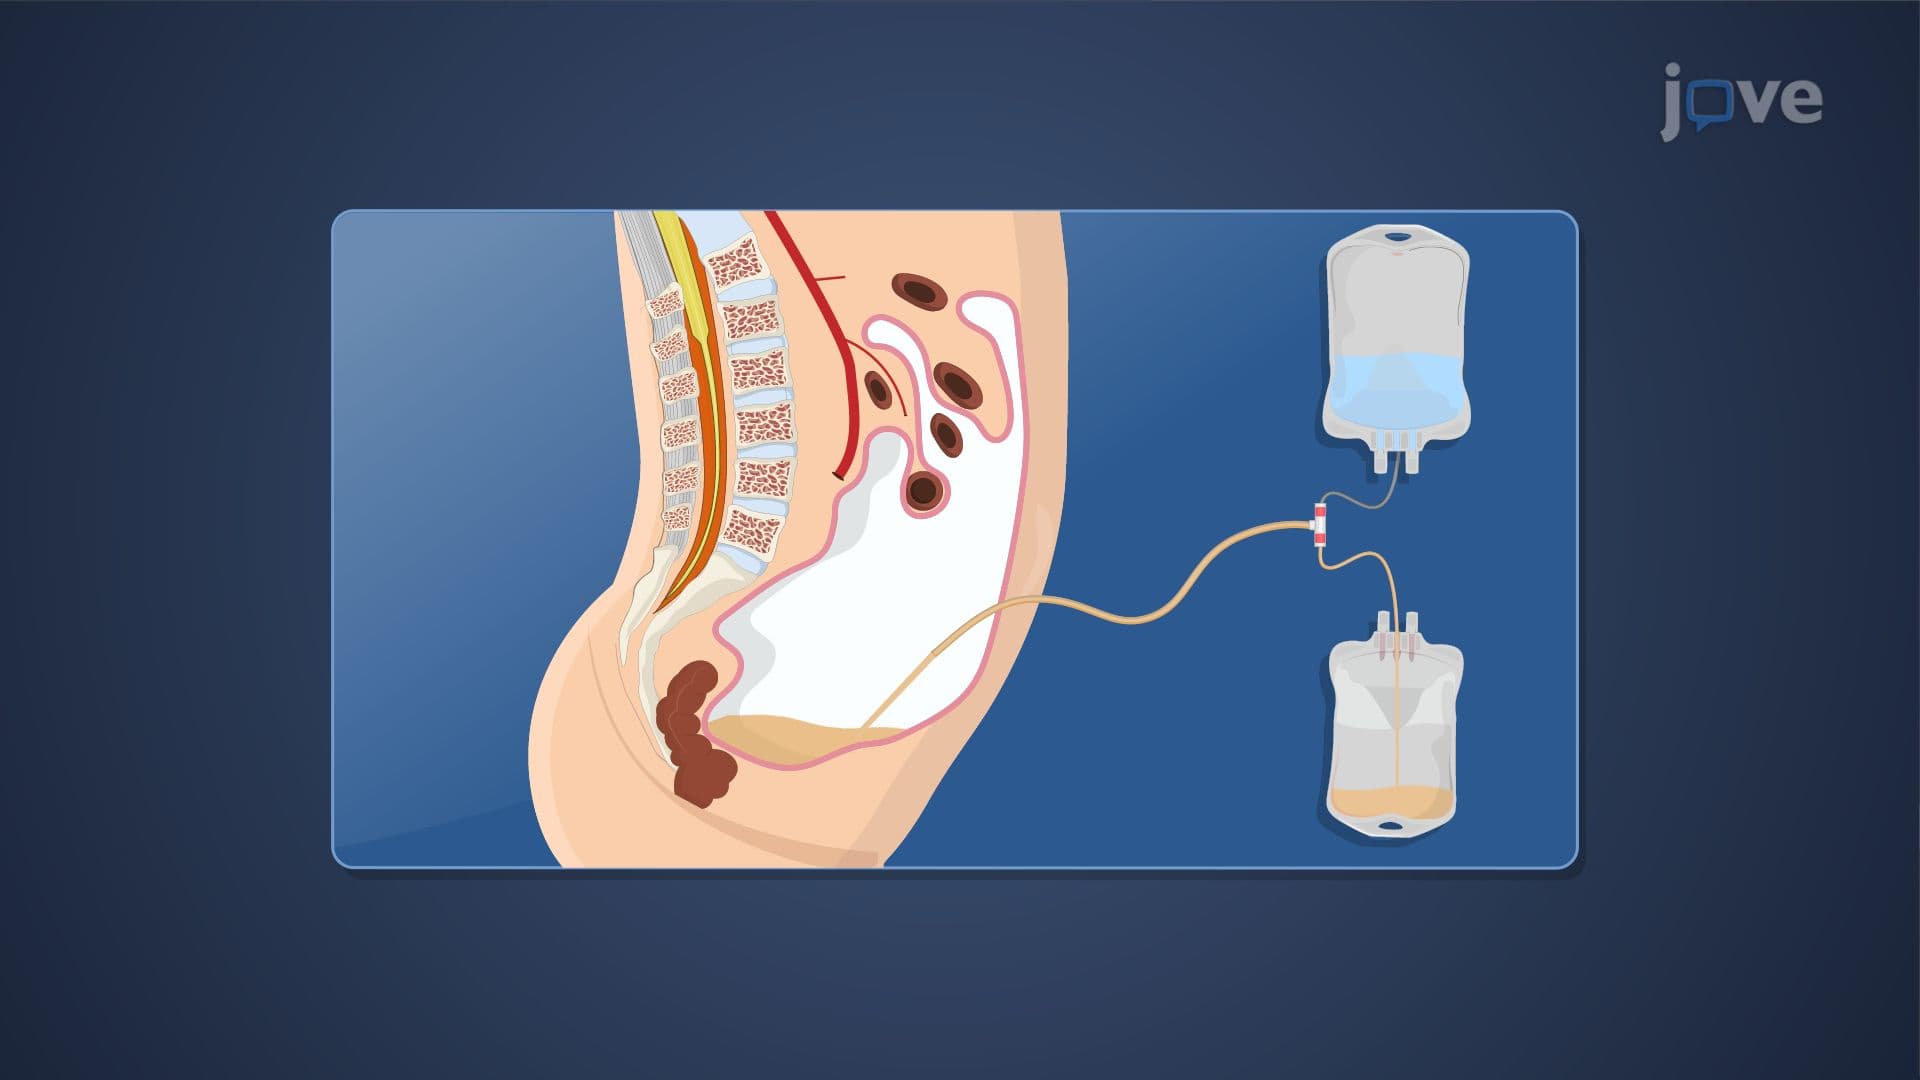 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:22
Diabetic Ketoacidosis ll: Pathophysiology