Related Experiment Video
Updated: Aug 20, 2026
Pseudomonas aeruginosa Induced Lung Injury Model
Published on: October 29, 2014
Postinjury serum secretory phospholipase A2 correlates with hypoxemia and clinical status at 72 hours
Nikole A Neidlinger1, Elsa R Hirvela, Ruby A Skinner
1Department of Surgery, University of California, San Francisco-East Bay, San Francisco, CA 94602, USA. neidlingern@surgery.ucsf.edu

Background:
Although trauma patients often suffer direct lung damage, an equally destructive mechanism of lung injury involves postinjury systemic inflammation. We postulate that secretory phospholipase A(2) (sPLA(2)) release induced by trauma relates to systemic inflammation that compromises both lung function and clinical status after injury. The objectives of this study were: to relate Injury Severity Score to postinjury sPLA(2); to determine whether circulating sPLA(2) relates to pulmonary oxygenation and compliance; and to determine whether early or persistent increases in sPLA(2) are associated with abnormal chest x-ray at 72 hours after injury.
Study Design:
The prospective cohort study comprised 54 consecutive intensive care admissions in patients with traumatic injury admitted over a 6-month period from November 1, 1996, to May 1, 1997.
Results:
Postinjury peak sPLA(2) values were associated with increased ISS (r = 0.49, r(2) = 0.24, p < 0.001). Patients with elevated sPLA(2) had poor oxygenation compared with those with normal sPLA(2) levels (Pa0(2)/Fi0(2) ratio 164 +/- 16 versus 260 +/- 26 mmHg [mean +/- SEM], p < 0.01) and also required additional PEEP (5.5 +/- 0.9 versus 2.5 +/- 0.4 cm H(2)O, p = 0.01). Secretory PLA(2) levels in patients with abnormal chest x-ray 72 hours after injury were higher (1.08 +/- 0.2 versus 0.34 +/- 0.1 activity units, p < 0.001) than levels seen in patients with normal x-rays.
Conclusions:
Increasing injury magnitude is associated with elevated sPLA(2) levels, and increased sPLA(2) is related to postinjury hypoxemia and clinical status.
Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:10
Atelectasis II: Pathophysiology
 01:29
Pneumonia II: Pathophysiology
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:25
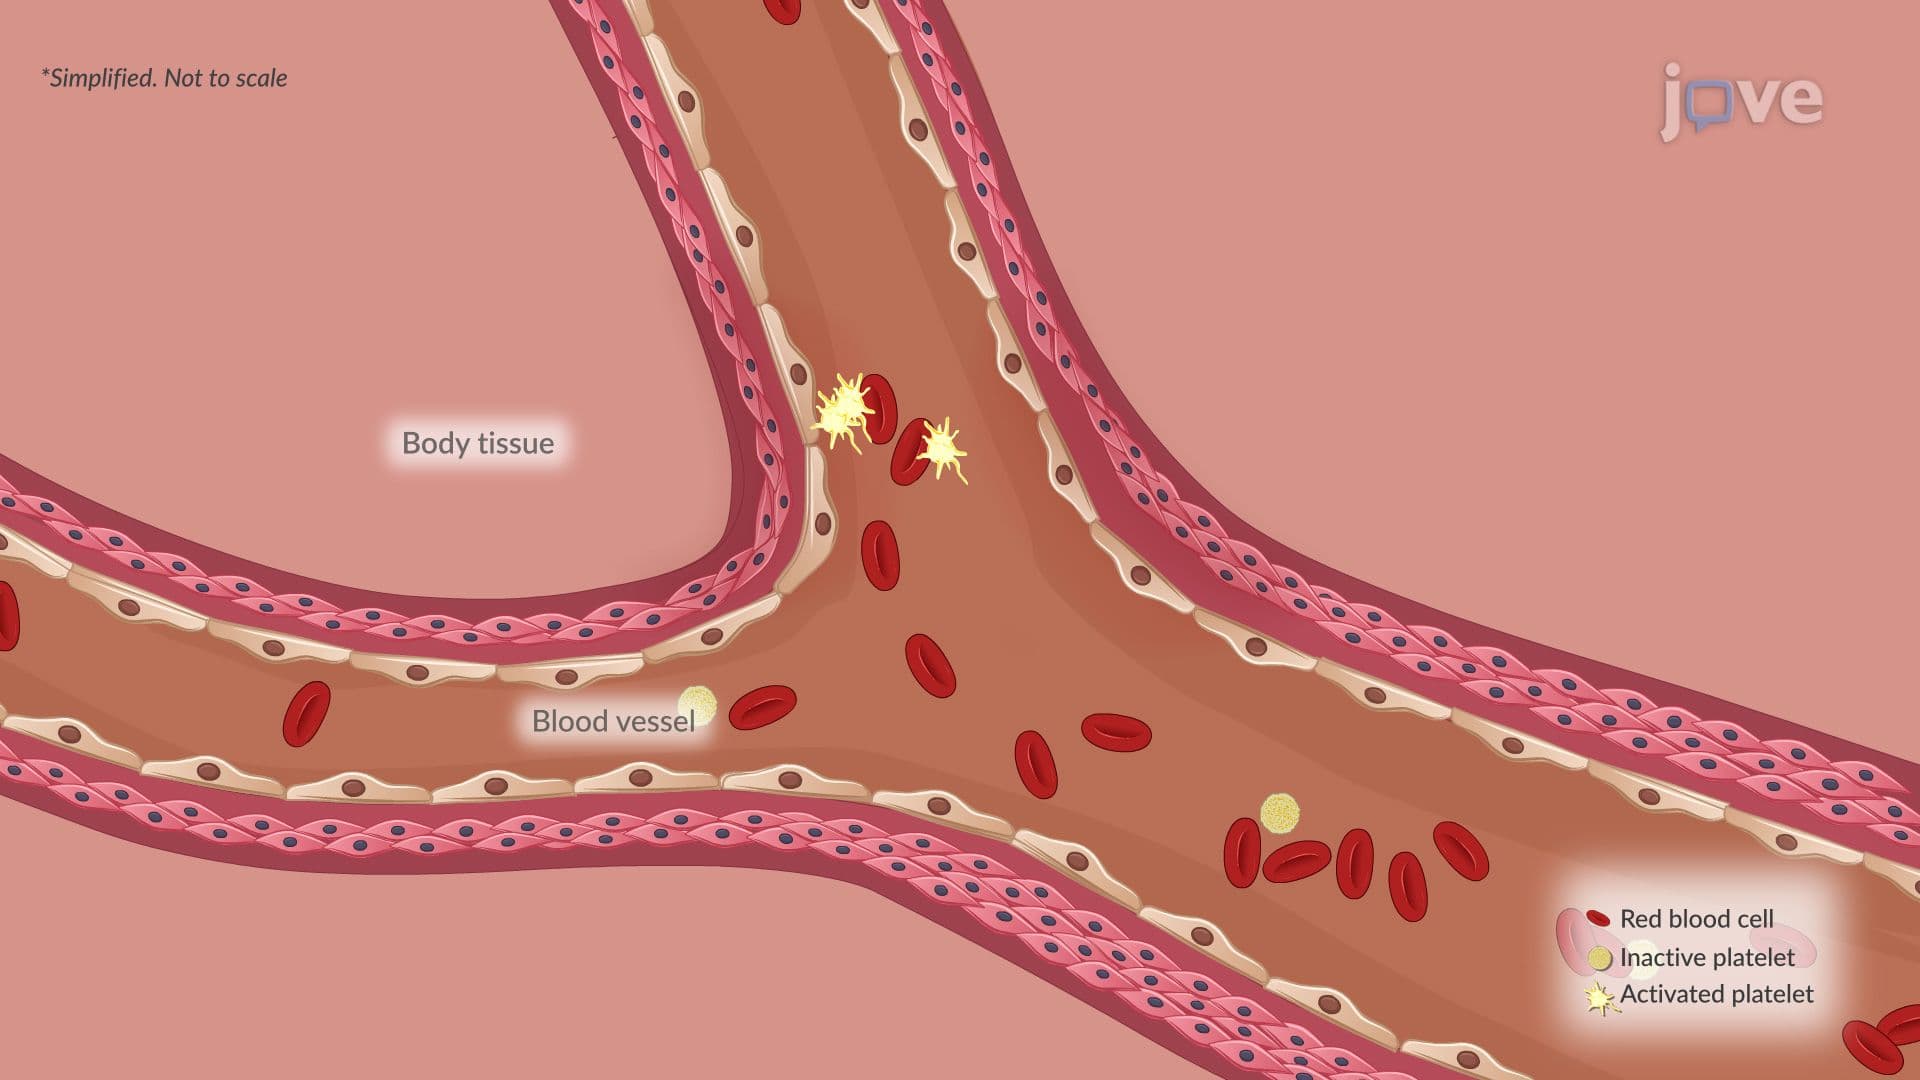
Acute Inflammation III: Local and Systemic Effects