Related Experiment Video
Updated: Aug 19, 2026


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse (POP) Quantification System
Published on: September 20, 2018
[Pregnancy, labor and delivery: the pelvic floor injury]
Efrat Hadi1, Asnat Groutz, Ronen Gold
1Urogynecology, Lis Maternity Hospital, Tel Aviv Sourasky Medical Center, Tel Aviv, Israel.

The association between pregnancy, labor and delivery, and pelvic floor injury is well known. Pregnancy itself may be associated with some injury, but the main damage occurs during vaginal delivery. It is well documented that vaginal delivery may cause denervation of the pelvic floor as well as direct injury to muscles and connective tissue. These injuries may lead to the development of stress urinary incontinence, anal incontinence, voiding difficulties, and/or urogenital prolapse. Previous studies showed correlation between various obstetric risk factors and the development of these symptoms, however, there is no consensus regarding the relative contribution of the different parameters. Moreover, the apparently protective effect of cesarean section is questionable. Further studies are required to define obstetric risk factors as well as patients at increased risk. These factors should be taken into consideration in modern obstetric practice.
The association between pregnancy, labor and delivery, and pelvic floor injury is well known. Pregnancy itself may be associated with some injury, but the main damage occurs during vaginal delivery. It is well documented that vaginal delivery may cause denervation of the pelvic floor as well as direct injury to muscles and connective tissue. These injuries may lead to the development of stress urinary incontinence, anal incontinence, voiding difficulties, and/or urogenital prolapse. Previous studies showed correlation between various obstetric risk factors and the development of these symptoms, however, there is no consensus regarding the relative contribution of the different parameters. Moreover, the apparently protective effect of cesarean section is questionable. Further studies are required to define obstetric risk factors as well as patients at increased risk. These factors should be taken into consideration in modern obstetric practice.
Related Concept Videos
 01:26
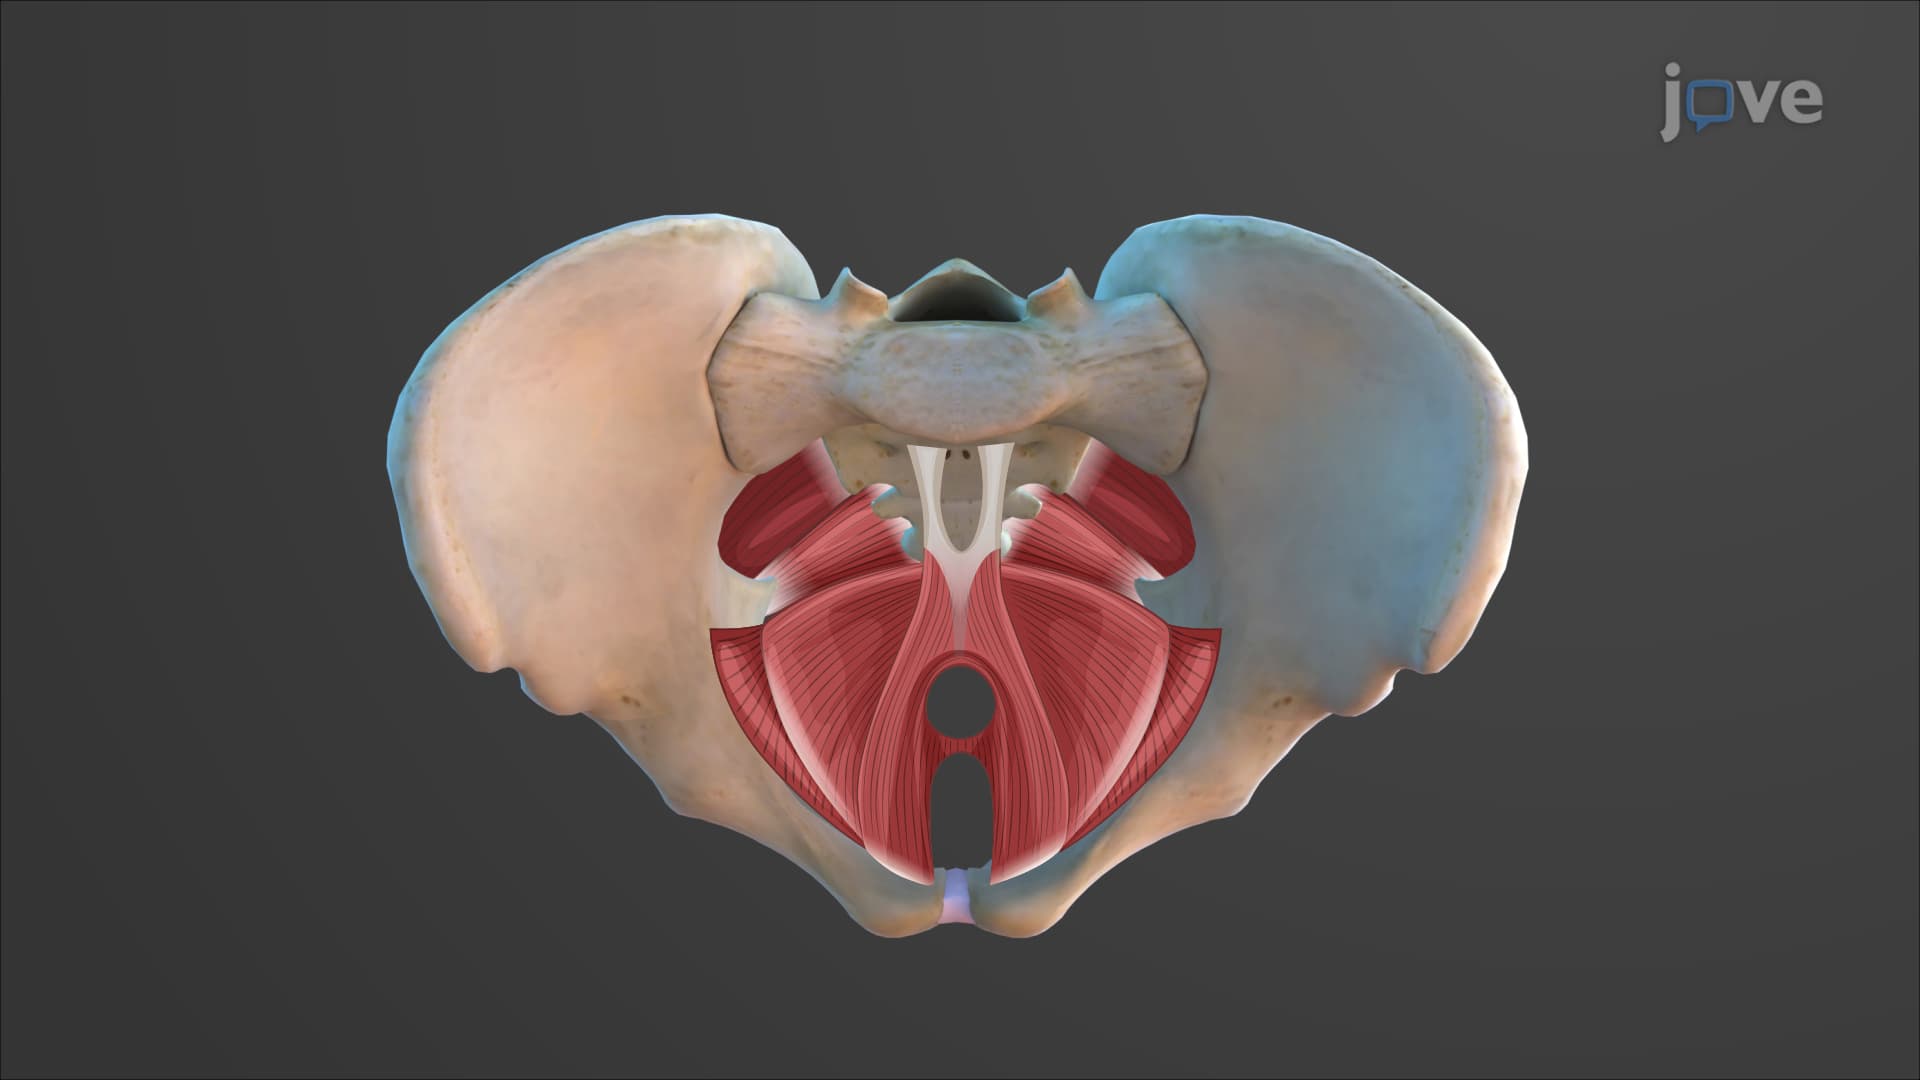
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Herniated Intervertebral Disc l: Introduction