Related Experiment Video
Updated: Aug 16, 2026

Functional Assessment of Intestinal Motility and Gut Wall Inflammation in Rodents: Analyses in a Standardized Model of Intestinal Manipulation
Published on: September 11, 2012
[Postoperative intestinal paralysis caused by the muscarinic receptor blocker tiotropium bromide]
1Urologische Belegabteilung, Klinikum, Starnberg. Dr.Praetorius@t-online.de

Abstract:
Drug-induced manipulation of the different muscarinic receptors is gaining increasing interest in the treatment of various diseases. Despite enhanced specific chemical design of these substances, side effects in other organ systems cannot be avoided completely. The observations presented led to the conclusion that under certain circumstances the bronchodilator tiotropium bromide can cause paralytic ileus.
Insights
Tiotropium bromide, a bronchodilator, may cause paralytic ileus in some patients. This side effect highlights potential risks of muscarinic receptor drugs despite targeted designs.
Area of Science:
- Pharmacology
- Gastroenterology
- Respiratory Medicine
Background:
- Muscarinic receptors are key targets for drug development across various diseases.
- Despite advances in drug design for receptor specificity, off-target side effects persist.
- Understanding drug-induced effects on different organ systems is crucial for patient safety.
Observation:
- The study observed a potential link between the use of tiotropium bromide and the development of paralytic ileus.
- Tiotropium bromide is a widely used long-acting muscarinic antagonist for respiratory conditions.
- Paralytic ileus, a gastrointestinal motility disorder, was noted as an adverse event.
Findings:
- The bronchodilator tiotropium bromide was found to be associated with paralytic ileus under specific circumstances.
- This suggests a potential gastrointestinal side effect of a drug primarily used for respiratory indications.
- The findings indicate an interaction between muscarinic receptor blockade and intestinal function.
Implications:
- Clinicians should be aware of the potential for tiotropium bromide to induce paralytic ileus.
- Further research is warranted to elucidate the precise mechanism of this adverse effect.
- This underscores the importance of monitoring gastrointestinal function in patients using tiotropium bromide.


Related Concept Videos
 01:24
Cholinergic Antagonists: Pharmacokinetics
 01:28
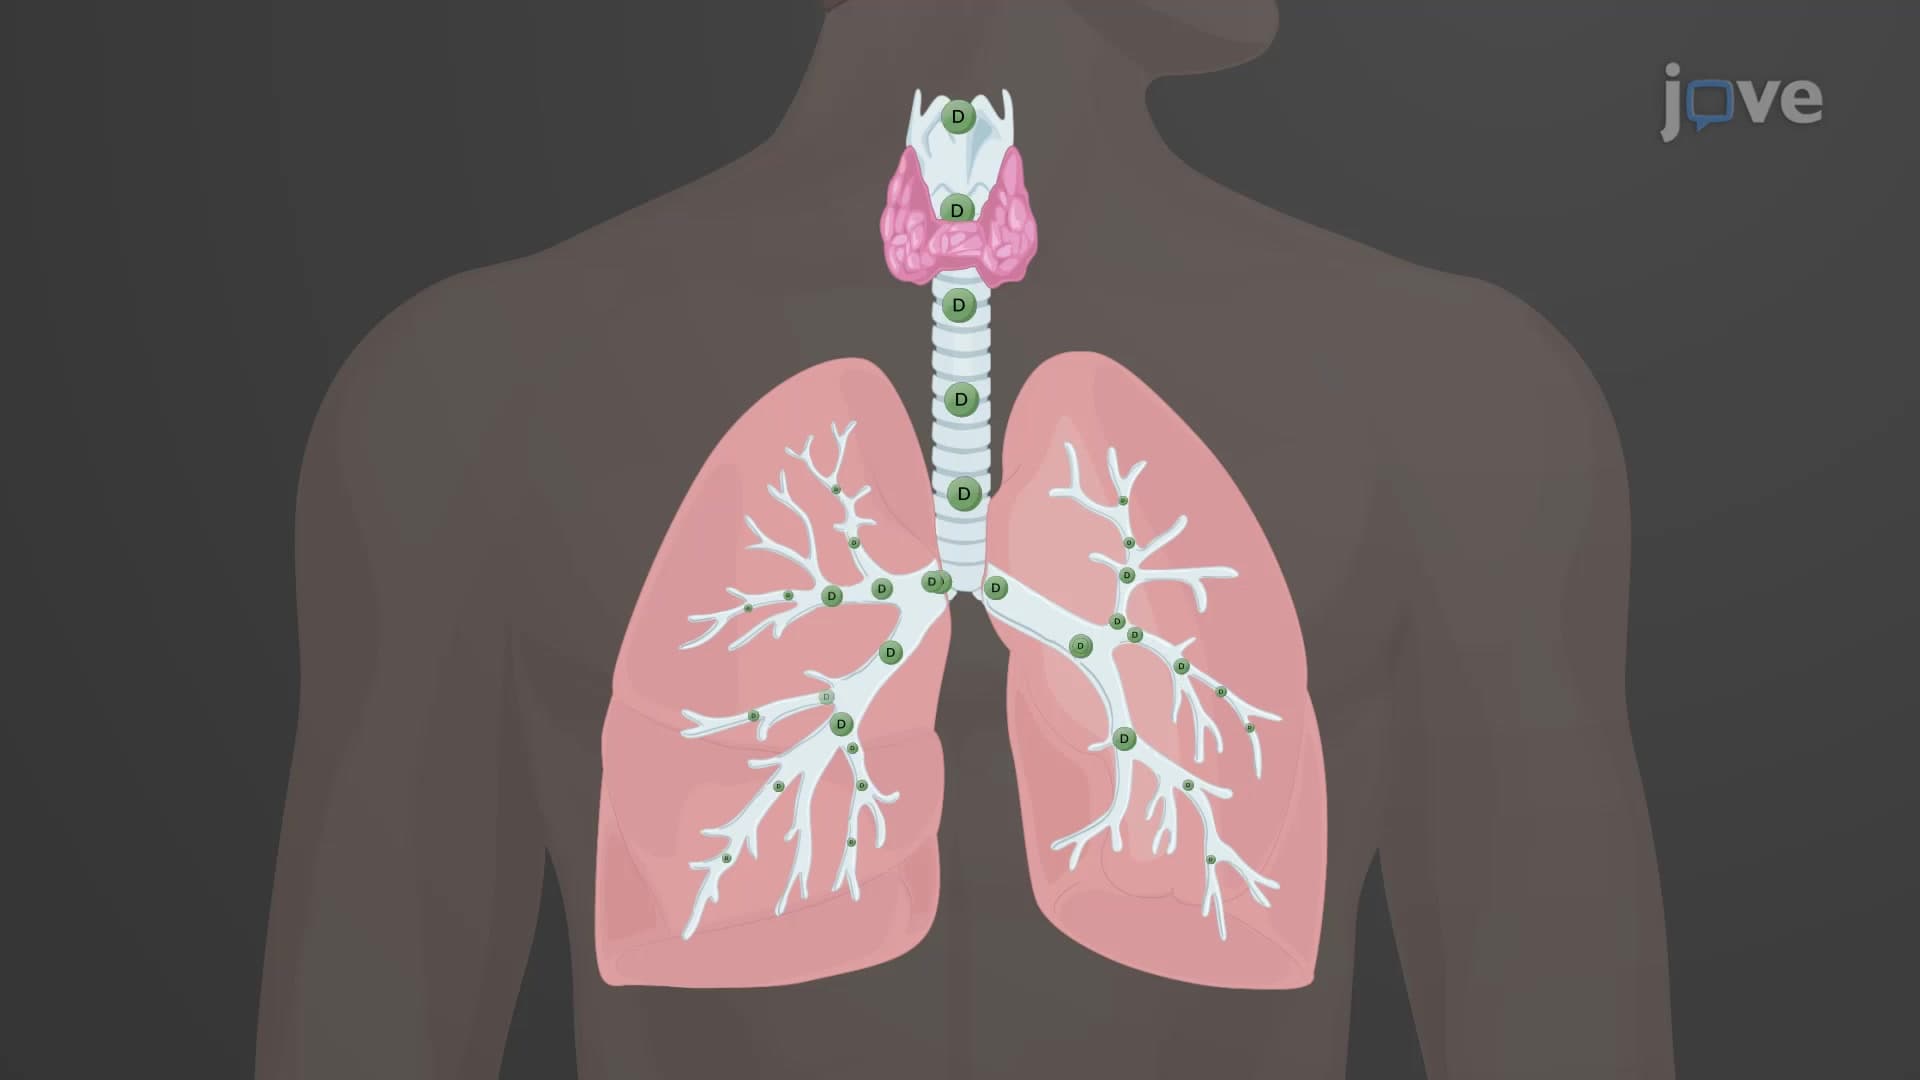
Cholinergic Antagonists: Pharmacological Actions
Gastrointestinal Effects: Antimuscarinics reduce gut contractions, increase gastric emptying, and slow intestinal transit. They partly inhibit gastric acid secretion...
 01:17
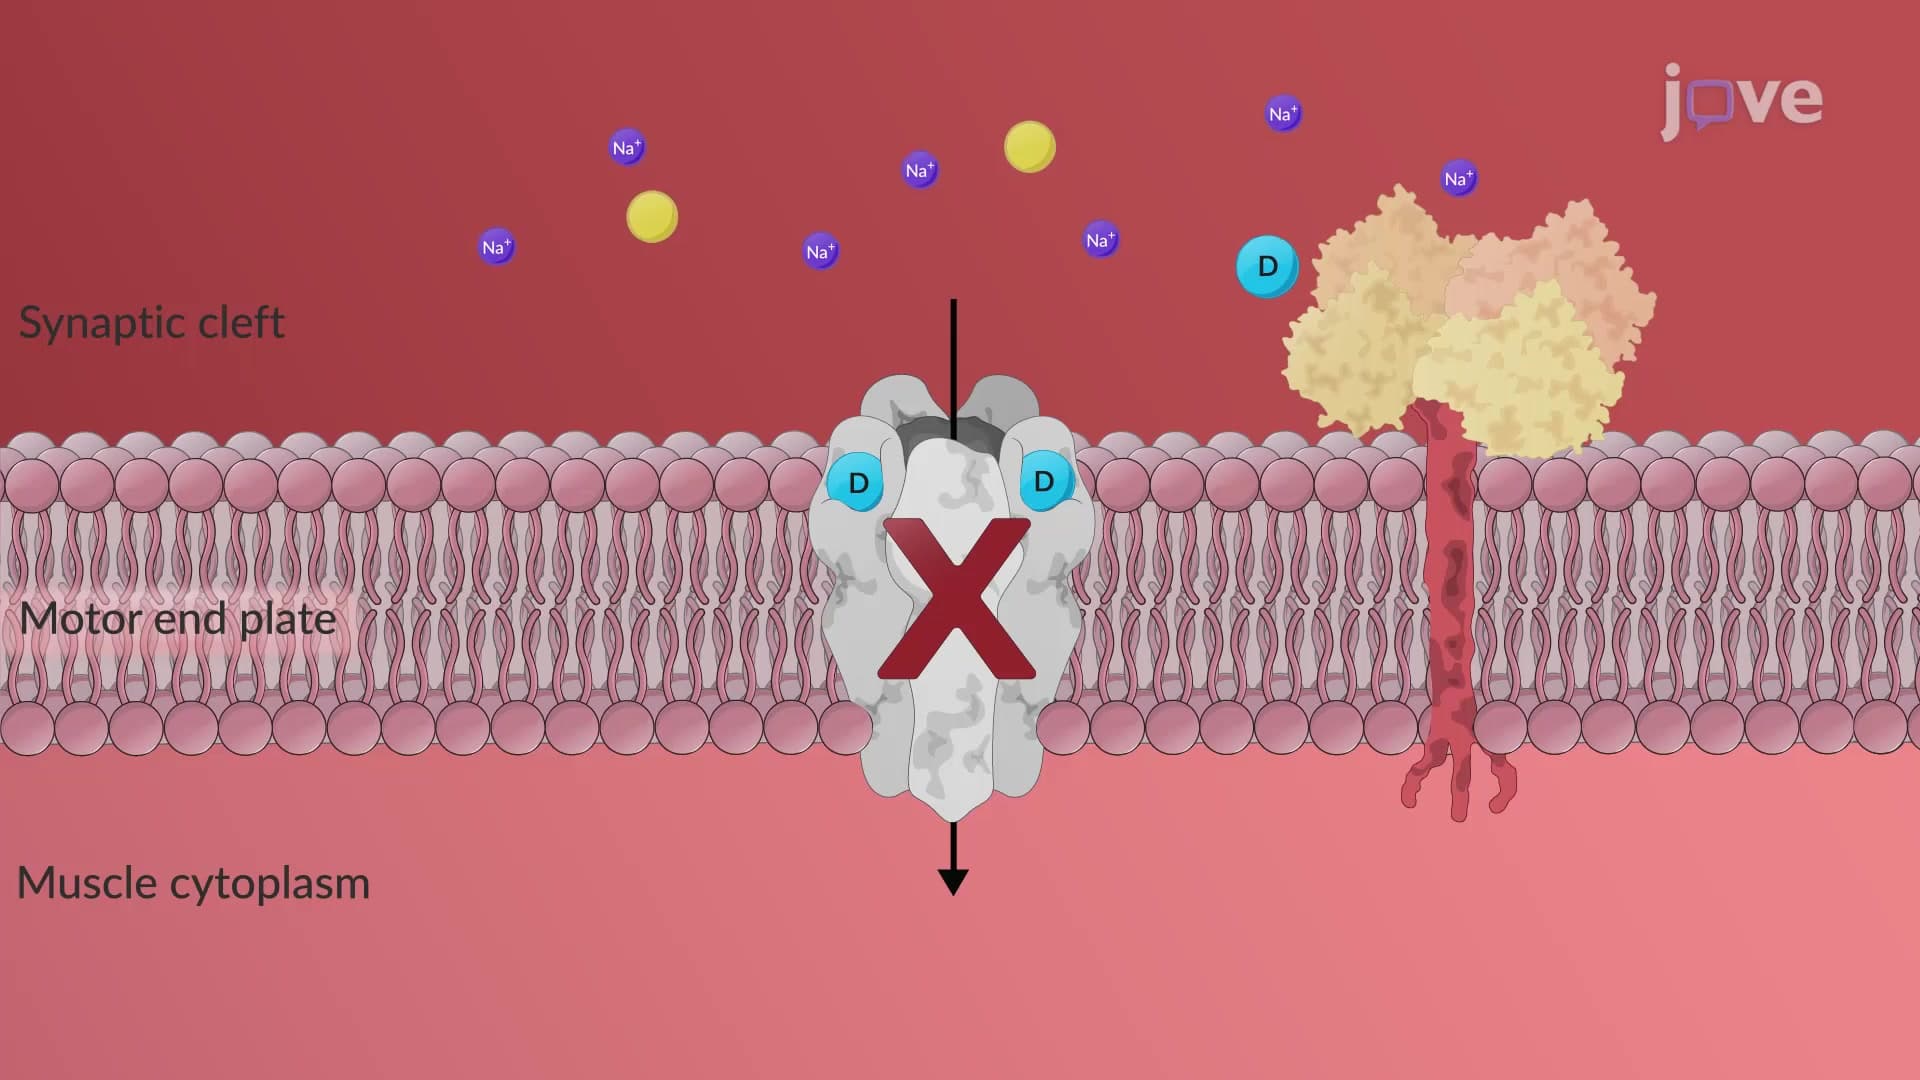
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:29
Intestinal Obstruction I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology