Related Experiment Video
Updated: Aug 19, 2026

Drug Treatment and In Vivo Imaging of Osteoblast-Osteoclast Interactions in a Medaka Fish Osteoporosis Model
Published on: January 1, 2017
A comparison of oral and intravenous bisphosphonate therapy for children with osteogenesis imperfecta
L A Dimeglio1, L Ford, C McClintock
1Department of Pediatrics, Section of Pediatric Endocrinology & Diabetology, Indiana University School of Medicine, Indianapolis, IN, USA. dimeglio@iupui.edu

Insights
Oral bisphosphonates, like alendronate, show similar efficacy to intravenous bisphosphonates in improving bone mineral density and reducing bone turnover in children with osteogenesis imperfecta.
Area of Science:
- Pediatric Endocrinology
- Orthopedics
- Pharmacology
Background:
- Intravenous bisphosphonates are established treatments for osteogenesis imperfecta, improving bone mineral density and fracture rates in children.
- The efficacy of oral bisphosphonates for treating osteogenesis imperfecta in pediatric populations remains largely unestablished.
- Osteogenesis imperfecta is a genetic disorder characterized by fragile bones, leading to frequent fractures and impaired growth.
Purpose of the Study:
- To compare the efficacy of oral alendronate versus intravenous pamidronate in children diagnosed with osteogenesis imperfecta.
- To evaluate the impact of both bisphosphonate formulations on bone mineral density, bone turnover markers, fracture incidence, and linear growth.
Main Methods:
- An open-label, prospective, randomized clinical trial was conducted.
- Pediatric patients were stratified by bone age, pubertal stage, and osteogenesis imperfecta type.
- Participants received either intravenous pamidronate (3 mg/kg every 4 months) or oral alendronate (10-20 mg daily).
Main Results:
- Both oral and intravenous bisphosphonate groups demonstrated comparable increases in bone mineral density, exceeding normal growth expectations.
- A significant decrease in biochemical markers of bone turnover was observed in all treated children.
- Moderate increases in linear growth and a non-significant reduction in fracture incidence were noted in both treatment arms.
Conclusions:
- Oral alendronate appears to be an effective alternative to intravenous pamidronate for managing osteogenesis imperfecta in children.
- Both treatment regimens positively impact bone metabolism and density, offering potential benefits for growth and fracture prevention.
- Further research with larger cohorts is warranted to confirm long-term efficacy and safety profiles.
Abstract:
Bone mineral density and fracture rates in children with osteogenesis imperfecta improve with intravenous bisphosphonates. The efficacy of oral bisphosphonates has not been established. This report is an analysis of an open-label, prospective, randomized clinical trial of oral compared to intravenous bisphosphonate medications in children with osteogenesis imperfecta. Children were stratified according to bone age, pubertal stage, and type of osteogenesis imperfecta and then randomized to receive intravenous pamidronate, 3 mg/kg over 3 days every 4 months, or oral alendronate 1 mg/kg, from a minimum of 10 mg to a maximum of 20 mg daily. The primary efficacy outcome was change in bone mineral density. Secondary outcomes included change in biomarkers of bone turnover, fracture incidence, and growth rate. Ten children were randomized (6 oral and 4 intravenous). Two other children were assigned to intravenous treatment due to chronic abdominal pain. In each group, three patients had type III/IV osteogenesis imperfecta, while three had type I. All 12 children completed 8 months of therapy; nine completed 12 months. Bone mineral density increased in both oral and intravenous groups equally and beyond that expected with normal growth. All children had a decrease in biochemical markers of bone turnover. Linear growth showed a moderate increase above that for age. There was a non-significant decrease in fracture incidence in both groups.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:28
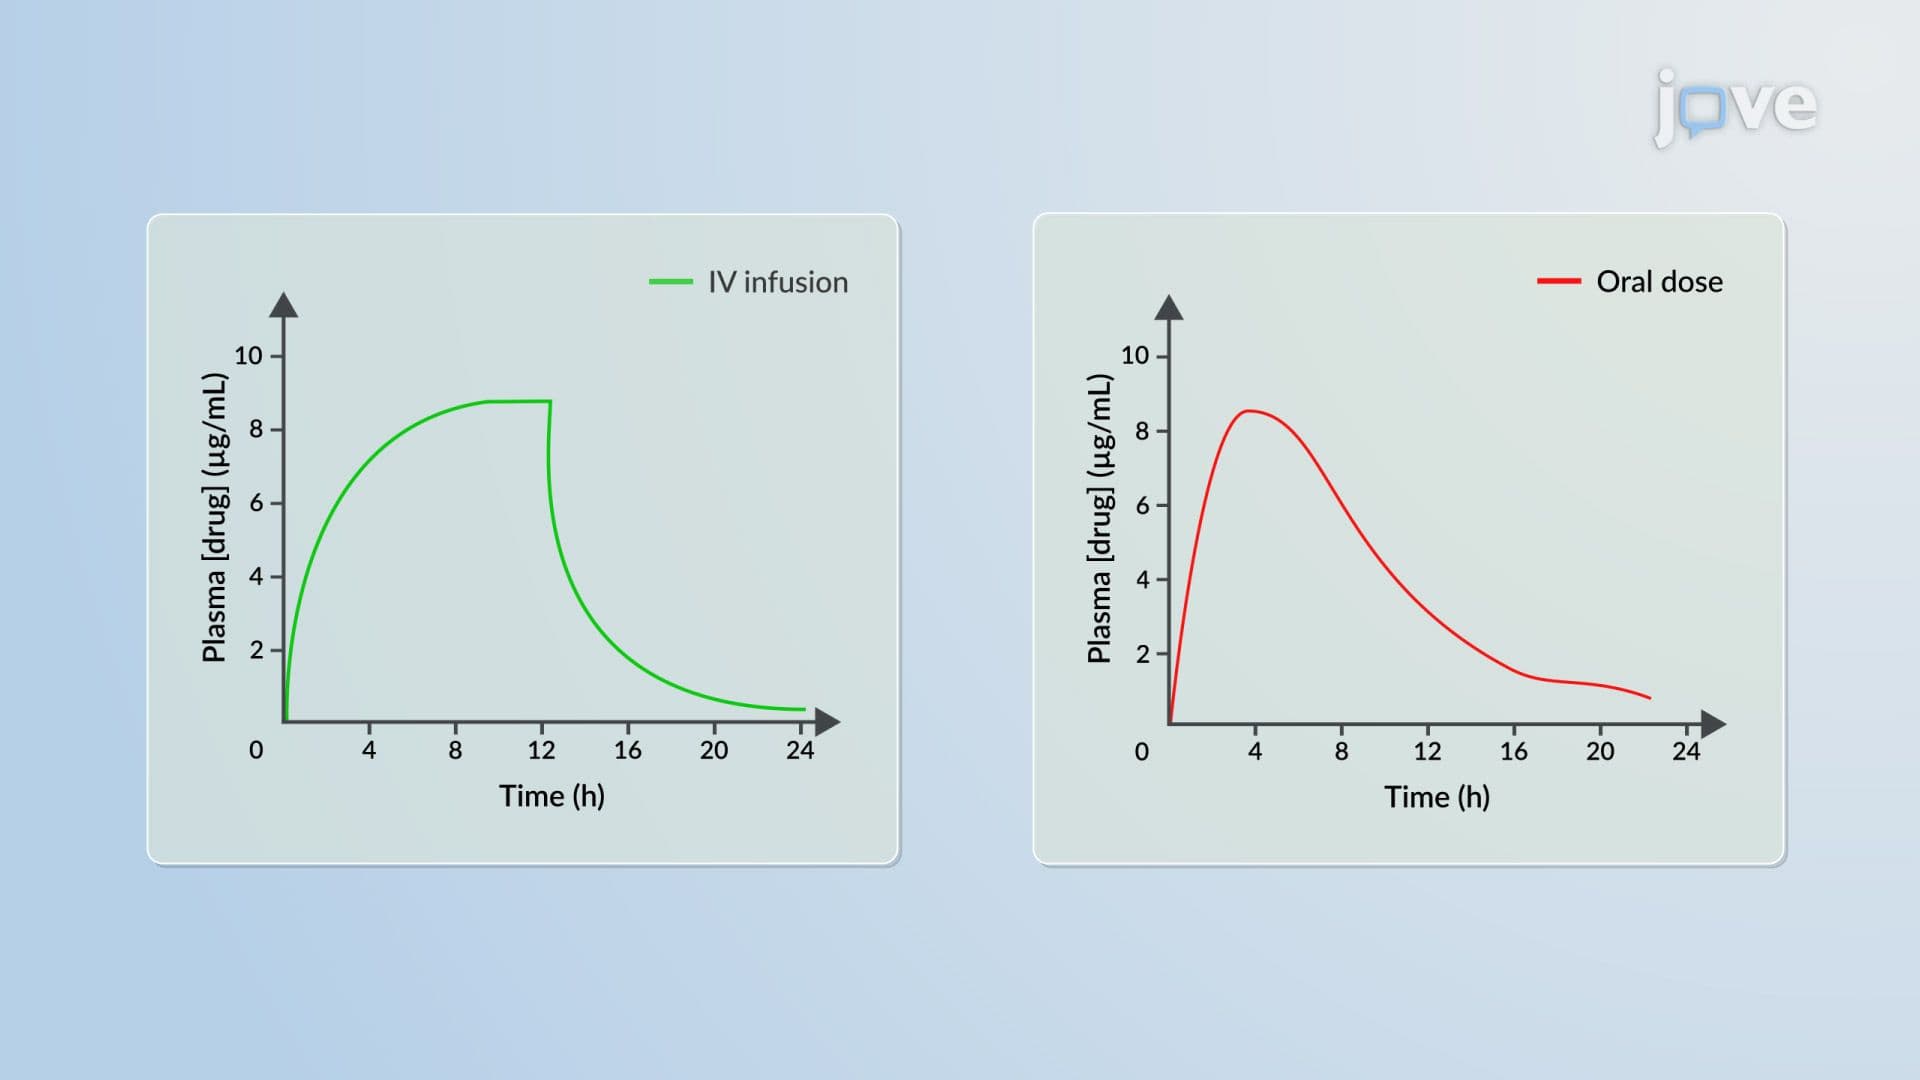
IV Infusion to Oral Dosing: Conversion Methods
 01:31
Osteoclasts in Bone Remodeling
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into...