Related Experiment Video
Updated: Aug 19, 2026
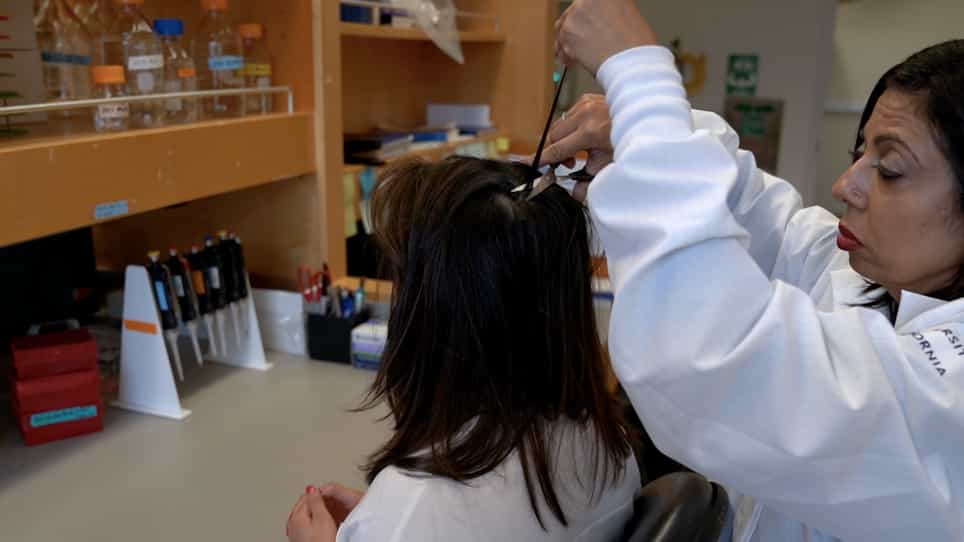
Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Rates of drug resistance and risk factor analysis in civilian and prison patients with tuberculosis in Samara Region,
M Ruddy1, Y Balabanova, C Graham
1HPA Mycobacterium Reference Unit, Department of Microbiology and Infection, Guy's King's and St Thomas' Medical School, King's College Hospital (Dulwich), London SE22 8QF, UK.

Background:
Tuberculosis (TB) and HIV rates continue to escalate in Russia, but true rates for drug resistance, especially multidrug resistant tuberculosis (MDR TB), are unknown. A study was conducted with the aims of identifying first line drug resistance, both in the civilian and prison sectors, for new and previously treated cases; and risk factors for the development of drug resistance.
Methods:
A cross sectional survey was undertaken of 600 patients (309 civilians, 291 prisoners) with bacteriologically confirmed pulmonary TB over a 1 year period during 2001-2 in Samara Oblast, Russia.
Results:
The prevalence of isoniazid, rifampicin, streptomycin, ethambutol and pyrazinamide resistance in new TB cases (civilian and prison patients) was 38.0%, 25.2%, 34.6%, 14.7%, and 7.2%, respectively. The prevalence of MDR TB was 22.7%, 19.8%, and 37.3% in all new cases, new civilian cases, and new prison cases, respectively, with an overall prevalence of 45.5% and 55.3% in previously treated cases. Factors associated with resistance included previous TB treatment for more than 4 weeks, smoking (for isoniazid resistance), the presence of cavitations on the chest radiograph, and imprisonment. HIV was not associated with resistance in all patients. The rates of resistance were significantly higher in prisoners, with rate ratios (RR) of 1.9 (95% CI 1.1 to 3.2) for MDR TB, 1.9 (95% CI 1.1 to 3.2) for rifampicin, and 1.6 (95% CI 1.0 to 2.6) for isoniazid.
Conclusions:
Rates of first line drug resistance are high, particularly in prisoners and previously treated cases. TB control programmes should initially focus on standardised treatment to maximise cure, combined with measures to reduce institutional TB spread (particularly in prisons) coupled with early diagnosis of MDR TB to reduce the spread and development of resistance.
Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:25
Mechanism of Antibiotic Resistance in MRSA
 01:23
Tuberculosis
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: