Related Experiment Video
Updated: Aug 19, 2026


Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
Deformational brachycephaly in supine-sleeping infants
John M Graham1, Jeannie Kreutzman, Dawn Earl
1Medical Genetics Institute, Ahmanson Department of Pediatrics, Steven Spielberg Pediatric Research Center, Burns and Allen Research Institute, Cedars-Sinai Medical Center, Los Angeles, CA 90048, USA.

Insights
Supine sleeping can increase brachycephaly (abnormal head shape) in infants. Cranial orthotic therapy is more effective than repositioning for severe cases, but varying infant head position during sleep is recommended.
Area of Science:
- Pediatric medicine
- Anthropology
- Craniofacial development
Background:
- Brachycephaly is defined by a cranial index (CI) greater than 81%.
- Infant head shape abnormalities are common, with potential links to sleeping positions.
Purpose of the Study:
- To investigate the impact of supine sleeping on infant cranial index (CI).
- To compare the effectiveness of orthotic treatment versus repositioning for brachycephaly.
Main Methods:
- A comparative study involving 193 infants with abnormal head shapes.
- Assessment of cranial index (CI) changes following repositioning or helmet therapy.
Main Results:
- Eighty percent of infants presented with a pretreatment CI > 81%.
- Mean CI decreased from 89% to 87% after treatment in infants with CI > 81%.
- Cranial orthotic therapy showed greater efficacy in correcting severe brachycephaly compared to repositioning.
Conclusions:
- Supine sleeping is associated with higher CI in infants.
- Orthotic therapy is more effective than repositioning for severe brachycephaly.
- Alternating infant head position during sleep is advised to mitigate brachycephaly risk.
Objectives:
Medical dictionaries and anthropologic sources define brachycephaly as a cranial index (CI = width divided by length x 100%) greater than 81%. We examine the impact of supine sleeping on CI and compare orthotic treatment with repositioning.
Study Design:
We compared the effect of repositioning versus helmet therapy on CI in 193 infants referred for abnormal head shape.
Results:
Eighty percent of the infants had a pretreatment CI > 81%. Their initial mean CI at mean age 5.3 months was 89%, and after treatment, their mean CI was 87% (+/-2 SE = 0.9%) at mean age 9.0 months. For 92 infants with an initial CI at or above 90%, their initial mean CI of 96.1% was reduced to a mean of 91.9%.
Conclusions:
Post-treatment CI was 86% to 88%, CI in neonates delivered by cesarean section was 80%, and CI in supine-sleeping Asian children was 85% to 91%, versus 78% to 83% for prone-sleeping American children. Repositioning was less effective than cranial orthotic therapy in correcting severe brachycephaly. We recommend varying the head position when putting infants to sleep.


Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:30
Neurulation
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:16
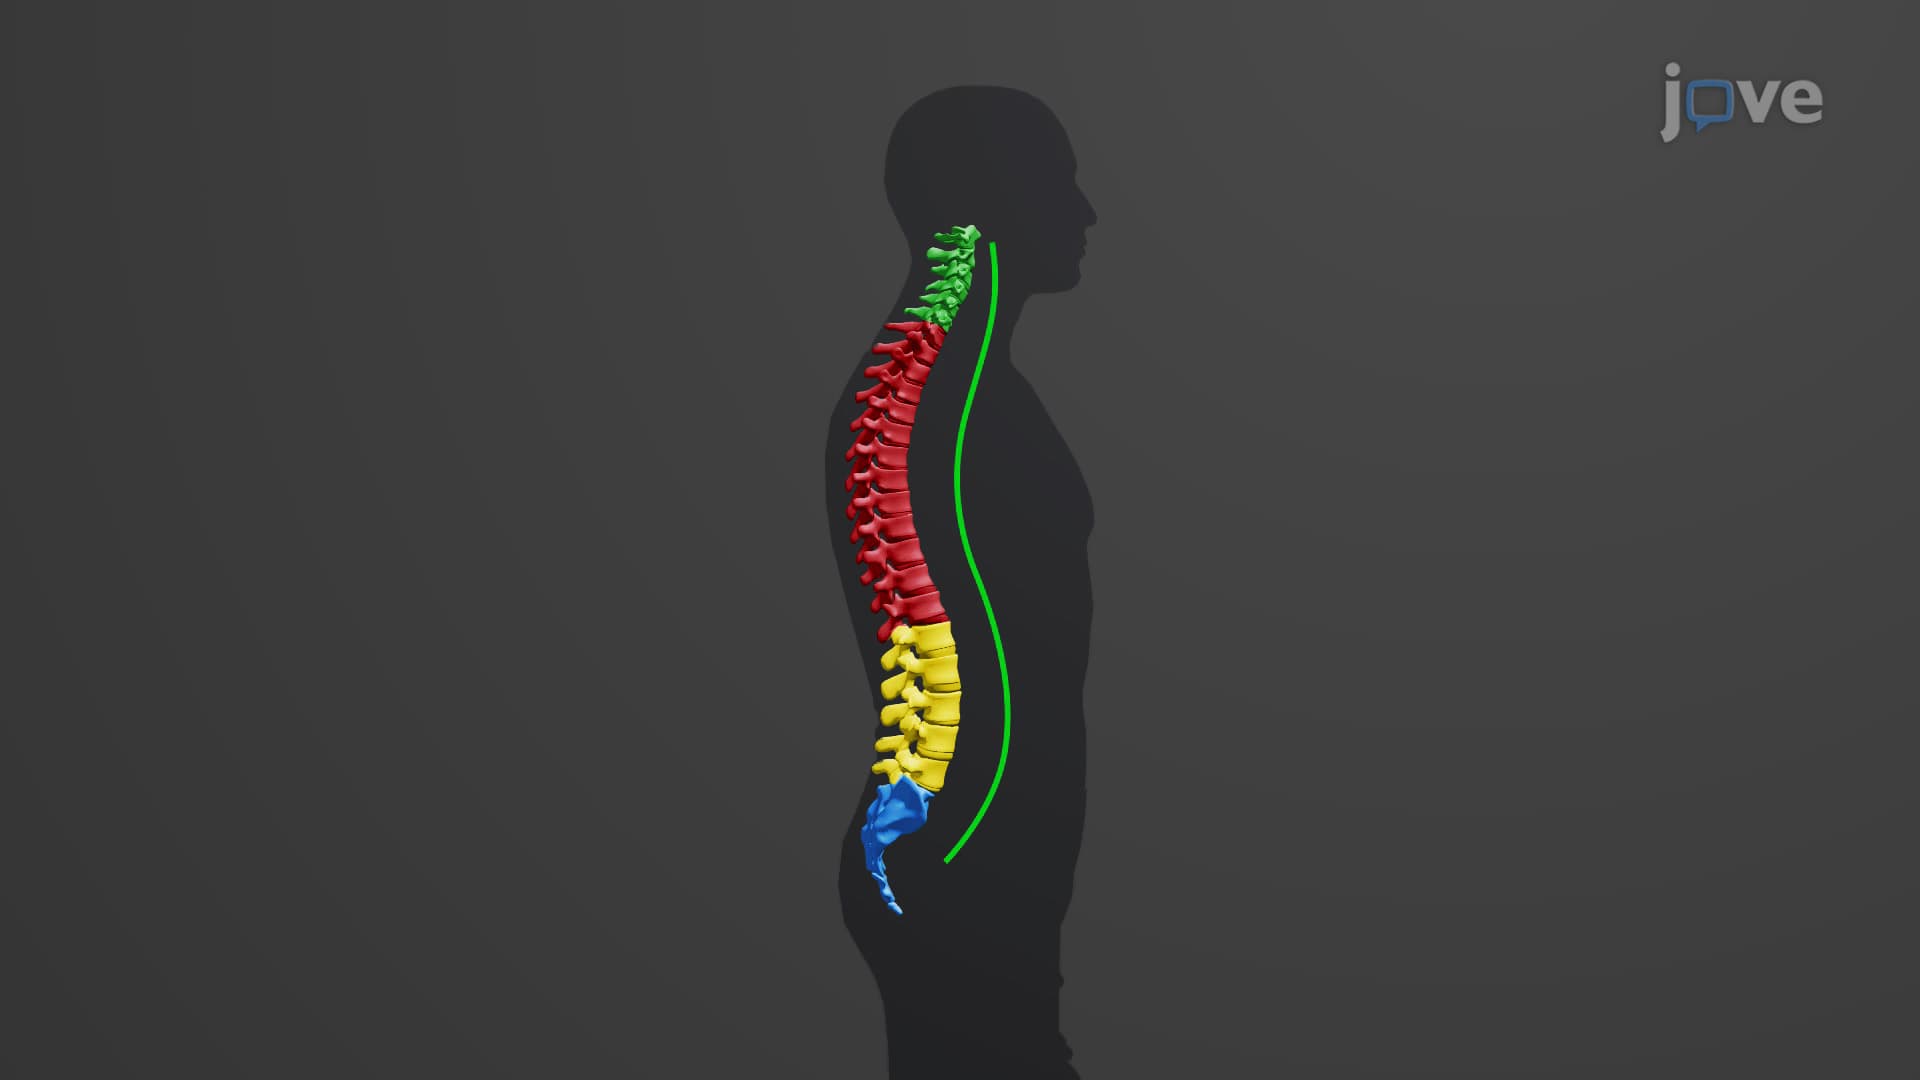
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...