Related Experiment Video
Updated: Aug 19, 2026
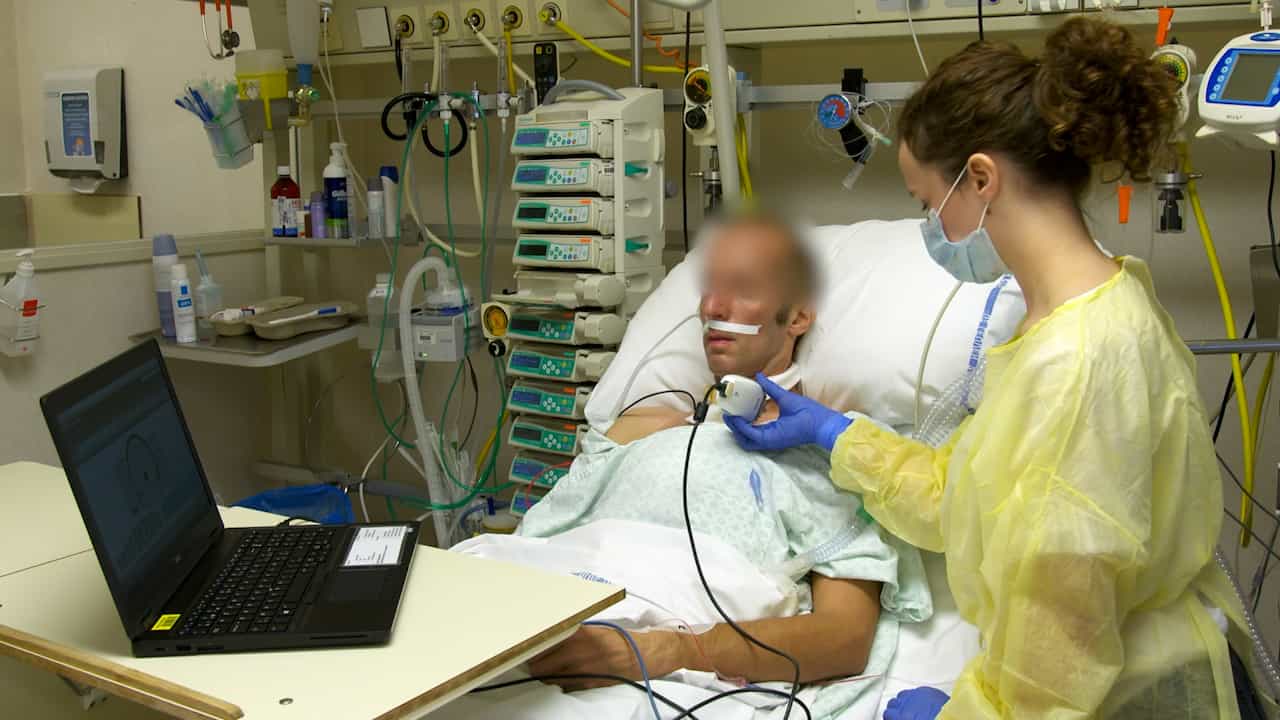

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Respiratory mechanics in the patient who is weaning from the ventilator
1Respiratory Care Services, PO Box 3911, Duke University Medical Center, Durham, NC 27710, USA. neil.macintyre@duke.edu

Abstract:
Ventilator management of the patient recovering from acute respiratory failure must balance competing objectives. On the one hand, aggressive efforts to promptly discontinue support and remove the artificial airway reduce the risk of ventilator-induced lung injury, nosocomial pneumonia, airway trauma from the endotracheal tube, and unnecessary sedation. On the other hand, overly aggressive, premature discontinuation of ventilatory support or removal of the artificial airway can precipitate ventilatory muscle fatigue, gas-exchange failure, and loss of airway protection. To help clinicians balance these concerns, 2 important research projects were undertaken in 1999-2001. The first was a comprehensive evidence-based literature review of the ventilator-discontinuation process, performed by the McMaster University research group on evidence-based medicine. The second was the development (by the American Association for Respiratory Care, American College of Chest Physicians, and Society of Critical Care Medicine) of a set of evidence-based guidelines based on the latter literature review. From those 2 projects, several themes emerged. First, frequent patient-assessment is required to determine whether the patient needs continued ventilatory support, from both the ventilator and the artificial airway. Second, we should continuously re-evaluate the overall medical management of patients who continue to require ventilatory support, to assure that we address all factors contributing to ventilator-dependence. Third, ventilatory support strategies should be aimed at maximizing patient comfort and unloading the respiratory muscles. Fourth, patients who require prolonged ventilatory support beyond the intensive care unit should go to specialized facilities that can provide gradual reduction of support. Fifth, many of these management objectives can be effectively carried out with protocols executed by nonphysicians.
Related Concept Videos
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:17
Pulmonary Cycle: Exhalation