Related Experiment Video
Updated: Aug 19, 2026
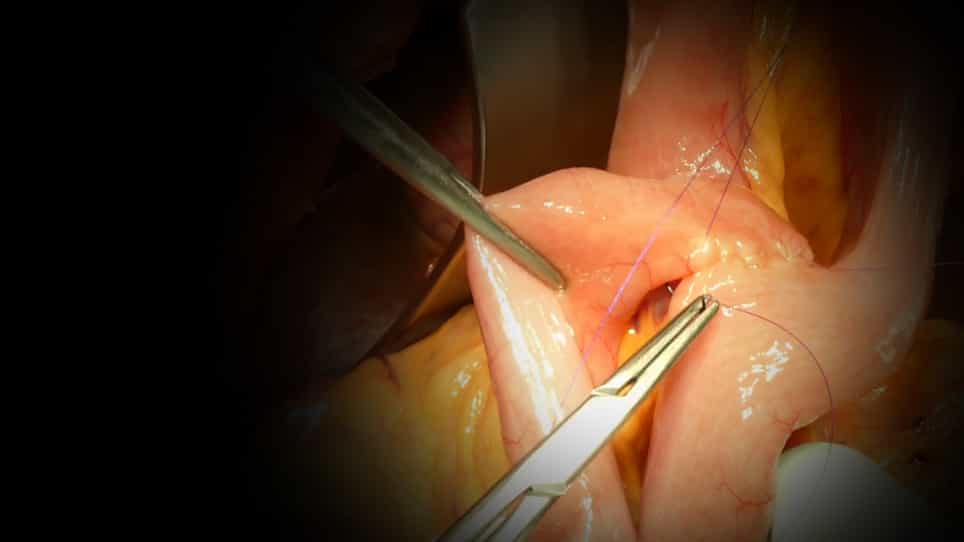

Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Analysis of postoperative reoperation for congenital duodenal obstruction
Qinming Zhang1, Yongwei Chen, Dawei Hou
1Department of Neonatal Surgery, Beijing Children's Hospital/Capital University of Medical Sciences, Beijing, People's Republic of China. qzhang9611@yahoo.com

Insights
Careful surgical evaluation can reduce reoperation rates for congenital duodenal obstruction. Missed multiple lesions during initial surgery are a key factor for reoperation in infants.
Area of Science:
- Pediatric Surgery
- Gastrointestinal Surgery
- Neonatal Care
Background:
- Congenital duodenal obstruction requires surgical intervention.
- Reoperation is a significant concern following initial repair.
Purpose of the Study:
- Analyze risk factors for reoperation after congenital duodenal obstruction repair.
- Identify strategies to decrease reoperation rates through improved surgical techniques.
Main Methods:
- Retrospective analysis of 298 neonates and infants (0-2 months) undergoing surgery for congenital duodenal obstruction over 30 years.
- Evaluation of reoperation reasons and analysis of combined lesions in relation to reoperation outcomes.
Main Results:
- Twenty patients (6.7%) presented with combined lesions, including duodenal web, malrotation, and annular pancreas.
- Twelve patients required reoperation due to complications or initially undiscovered duodenal atresias.
Conclusions:
- Over half of reoperated patients had missed multiple duodenal obstruction lesions.
- Enhanced preoperative and intraoperative evaluation can lower the reoperation rate for congenital duodenal obstruction.
Objective:
To analyse the risk factors for reoperation after initial surgical repair of congenital duodenal obstruction and demonstrate that they can be decreased with more careful attention and more advanced techniques during surgery.
Methods:
The records of newborns and infants (aged 0-2 months) who had surgical therapy for congenital duodenal obstruction in the past 30 years were reviewed and analysed. Of the 298 patients, 132 (44%) were boys and 166 (56%) were girls. All patients who underwent repeat surgery postoperatively were evaluated by the reasons for surgery. The number of patients with various combination lesions of congenital duodenal obstruction was also calculated and the relationship to postoperative reoperation was analysed.
Results:
Twenty patients (6.7%) had congenital duodenal obstruction with combination lesions including duodenal web, malrotation, annular pancreas and multiple duodenal web. Twelve patients required further operation 5 days to 2 years postoperatively for complications (n = 5) and other duodenal atresias that were not discovered initially (n = 7).
Conclusion:
More than half of reoperated patients (7/12) had multiple lesions of duodenal obstruction that were missed during the primary operation. The postoperative reoperation rate for congenital duodenal obstruction could be decreased with more careful attention to operative details and more preoperative and intraoperative evaluation of the gastrointestinal tract.
