Related Experiment Video
Updated: Aug 19, 2026
Isolation of Neonatal Extrahepatic Cholangiocytes
Published on: June 5, 2014
[Hereditary cholestasis, an unusual etiology of pruritus in the infant]
E Mahé1, F Lacaille, S Hadj-Rabia
1Service de Dermatologie, Groupe Hospitalier Necker-Enfants Malades, Assistance Publique-Hôpitaux de Paris, 75015 Paris. emmanuel.mahe@nck.ap-hop-paris.fr

Insights
Infantile pruritus can signal rare bile acid transport disorders like hypercholanemia and familial fibrogenic cholestasis. Early diagnosis and treatment with ursodeoxycholic acid and rifampicin manage symptoms and prevent liver disease progression.
Area of Science:
- Pediatric Gastroenterology
- Hepatology
- Medical Genetics
Background:
- Pruritus in infants is typically linked to common dermatoses, with systemic causes being rare.
- This study investigates two cases where infant pruritus indicated underlying anicteric cholestasis.
Observation:
- Case 1: A 13-month-old boy with pruritus since 2 months old presented with elevated total bile acids, diagnosed as hypercholanemia.
- Case 2: A 21-month-old boy with pruritus and growth delay showed cholestasis with normal GGT, diagnosed as familial fibrogenic cholestasis.
Findings:
- Both cases demonstrated abnormalities in bile acid transport.
- Hypercholanemia involves faulty bile acid canalization by hepatocytes.
- Familial fibrogenic cholestasis involves impaired bile acid elimination.
Implications:
- Non-dermatological pruritus in infants warrants investigation for rare bile acid transport defects.
- Prompt diagnosis and treatment can alleviate symptoms and prevent progression to cirrhosis in familial fibrogenic cholestasis.
Introduction:
Pruritus in the infant is predominantly related to common dermatosis. General causes remain exceptional. We report two cases of pruritus in infants revealing anicteric cholestasis.
Observations:
Case no 1. A thirteen month-old boy had exhibited pruritus since the age of 2 months. The clinical examination was non-specific. Biological explorations revealed an isolated and moderate rise in total bilary acids. The search for mutations in the genes of a familial fibrogenic cholestasis was negative. The diagnosis retained was hypercholanemia. Treatment combined ursodesoxycholic acid and rifampicine, which controlled the pruritus and normalized the bilary acid levels. Case no 2. A twenty-one month-old boy had exhibited pruritus since the age of 2 months and delayed growth. The clinical examination was unspecific. The biological explorations revealed cholestasis with normal delta GT, moderate cytolysis and liposoluble vitamin deficiency. The hepatic biopsy was normal. The diagnosis retained was familial fibrogenic cholestasis. Treatment combined ursodesoxycholic acid and rifampicine, which controlled the pruritus and normalized the hepatic parameters.
Discussion:
Non-dermatological isolated pruritus is rare in infants. These two observations illustrate two abnormalities in bilary acid transport. Hypercholanemia is a faulty canalization of bilary acids by the hepatocyte. Familial fibrogenic cholestasis is a default in the elimination of these bilary acids. Such pathologies must be evoked because specific treatment will treat the symptoms and avoid the evolution of familial fibrogenic cholestasis towards cirrhosis.

Related Concept Videos
 01:20
Cholecystitis
 01:25
Jaundice
 01:25
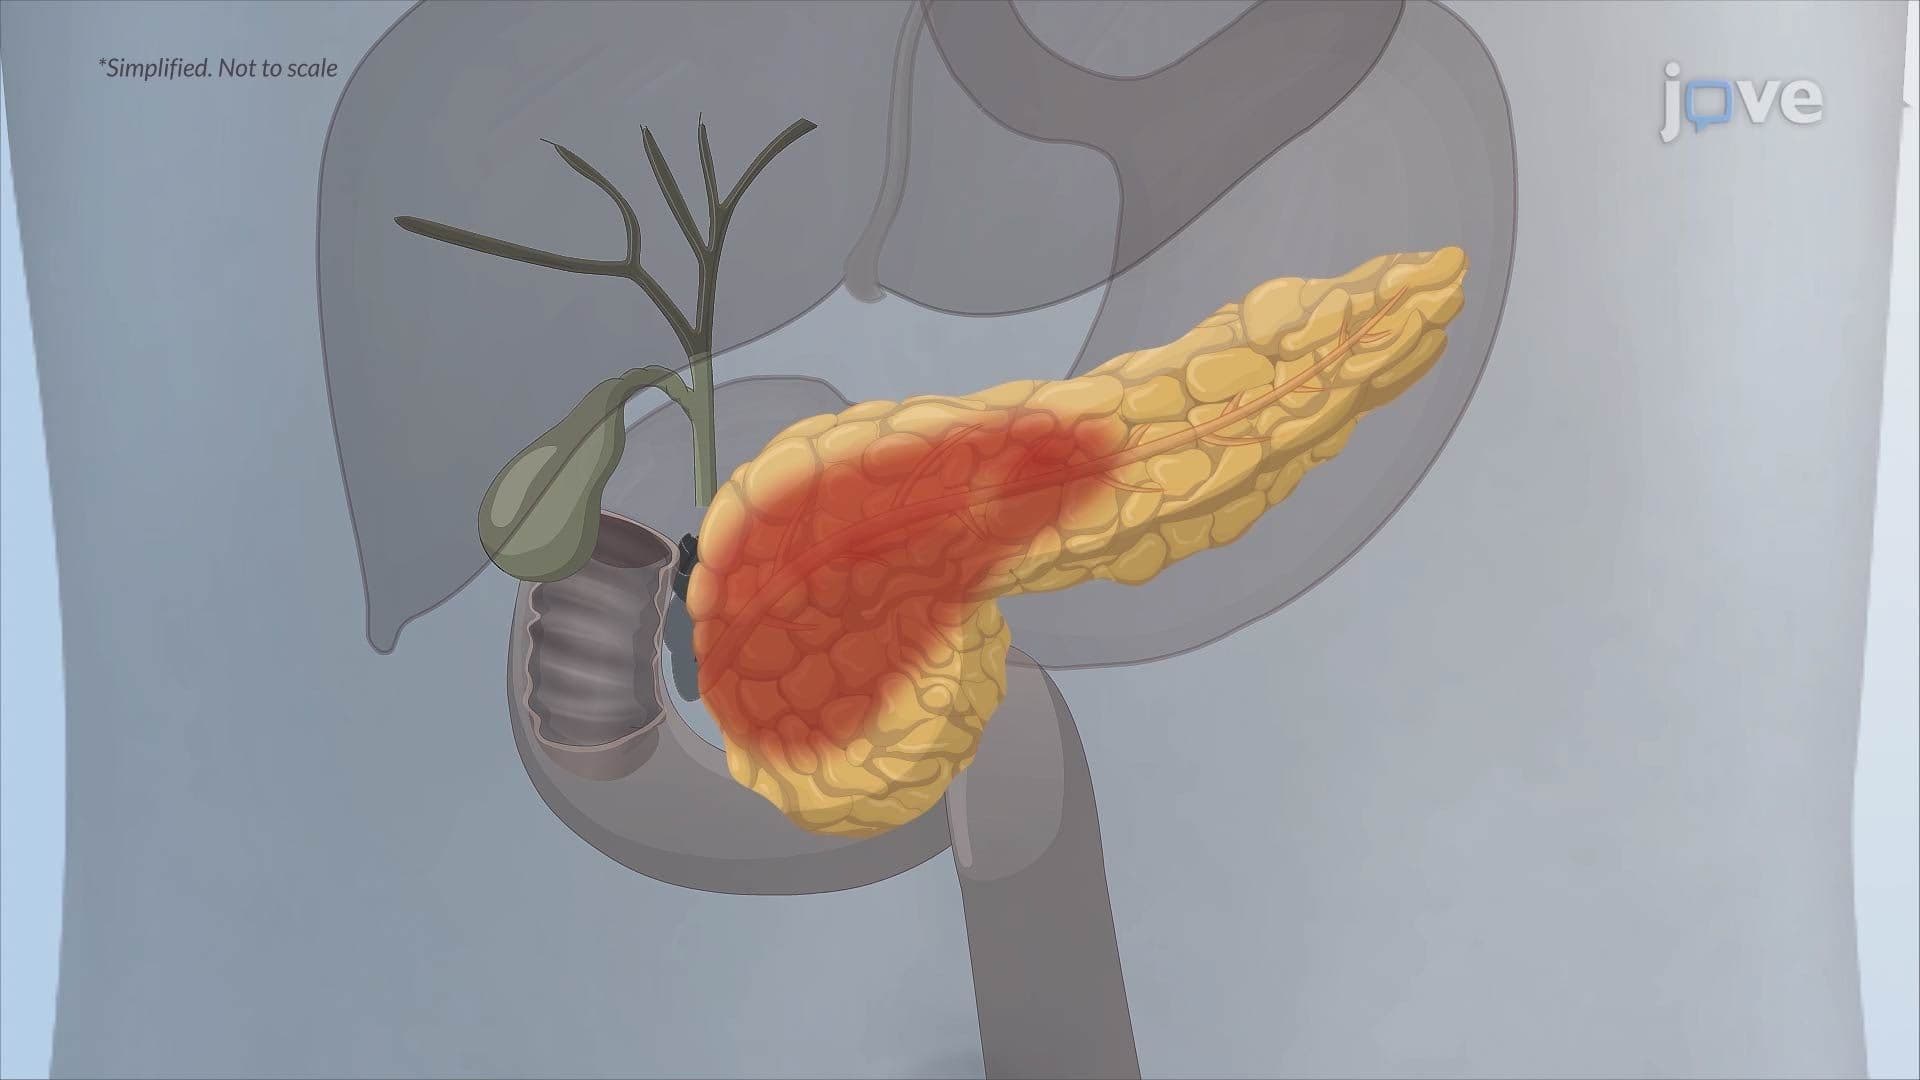
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:27
Protein Import into the Peroxisomes
Peroxisomal Protein Import:
Peroxisomes lack the genetic machinery required to code for their own proteins. Hence, most peroxisomal membrane, lumenal and transmembrane proteins are synthesized in the cytoplasm or ER and transported to the peroxisome...