Related Experiment Video
Updated: Aug 19, 2026


Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Hemosiderosis is associated with accelerated decompensation and decreased survival in patients with cirrhosis
Zeid Kayali1, Rostislav Ranguelov, Frank Mitros
1Division of Gastroenterology and Hepatology, Keck School of Medicine, University of Southern California, Los Angeles, CA, USA.

Aim:
Although hepatic iron deposition unrelated to hereditary hemochromatosis is commonly observed in cirrhosis, its clinical significance is unclear. The aim of this study was to examine the outcomes of cirrhotic patients with and without hemosiderosis.
Methods:
Patients with an initial liver biopsy demonstrating cirrhosis between January 1993 and December 1997 were identified using the Department of Pathology database. Based on iron staining, patients were characterized as siderotic or nonsiderotic. Charts were reviewed to determine outcomes.
Results:
Siderotic patients had significantly higher Child-Pugh (CP) and model for end-stage liver disease (MELD) scores. Their median survival without transplant was 23 months vs. 85 months in the nonsiderotics (P<0.0001, confidence interval: 95%). On univariate analysis, siderosis was associated with a hazard ratio of 2.74 (P<0.0001). On multivariate analysis, the effect of siderosis was reduced but remained significant after correction for the CP or MELD score (hazard ratios 1.82 and 2.06, P=0.05 and 0.02, respectively). Child's A cirrhotics with hemosiderosis decompensated more rapidly and had shorter median survival than those without siderosis (P=0.007 and P=0.01, respectively).
Conclusions:
The presence of siderosis is associated with more advanced liver dysfunction. Even when the effects of baseline liver function are taken into account, siderosis is associated with decreased survival and more rapid decompensation in cirrhosis.

Related Concept Videos
 01:24
Cirrhosis II: Pathophysiology
 01:23
Cirrhosis I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:22
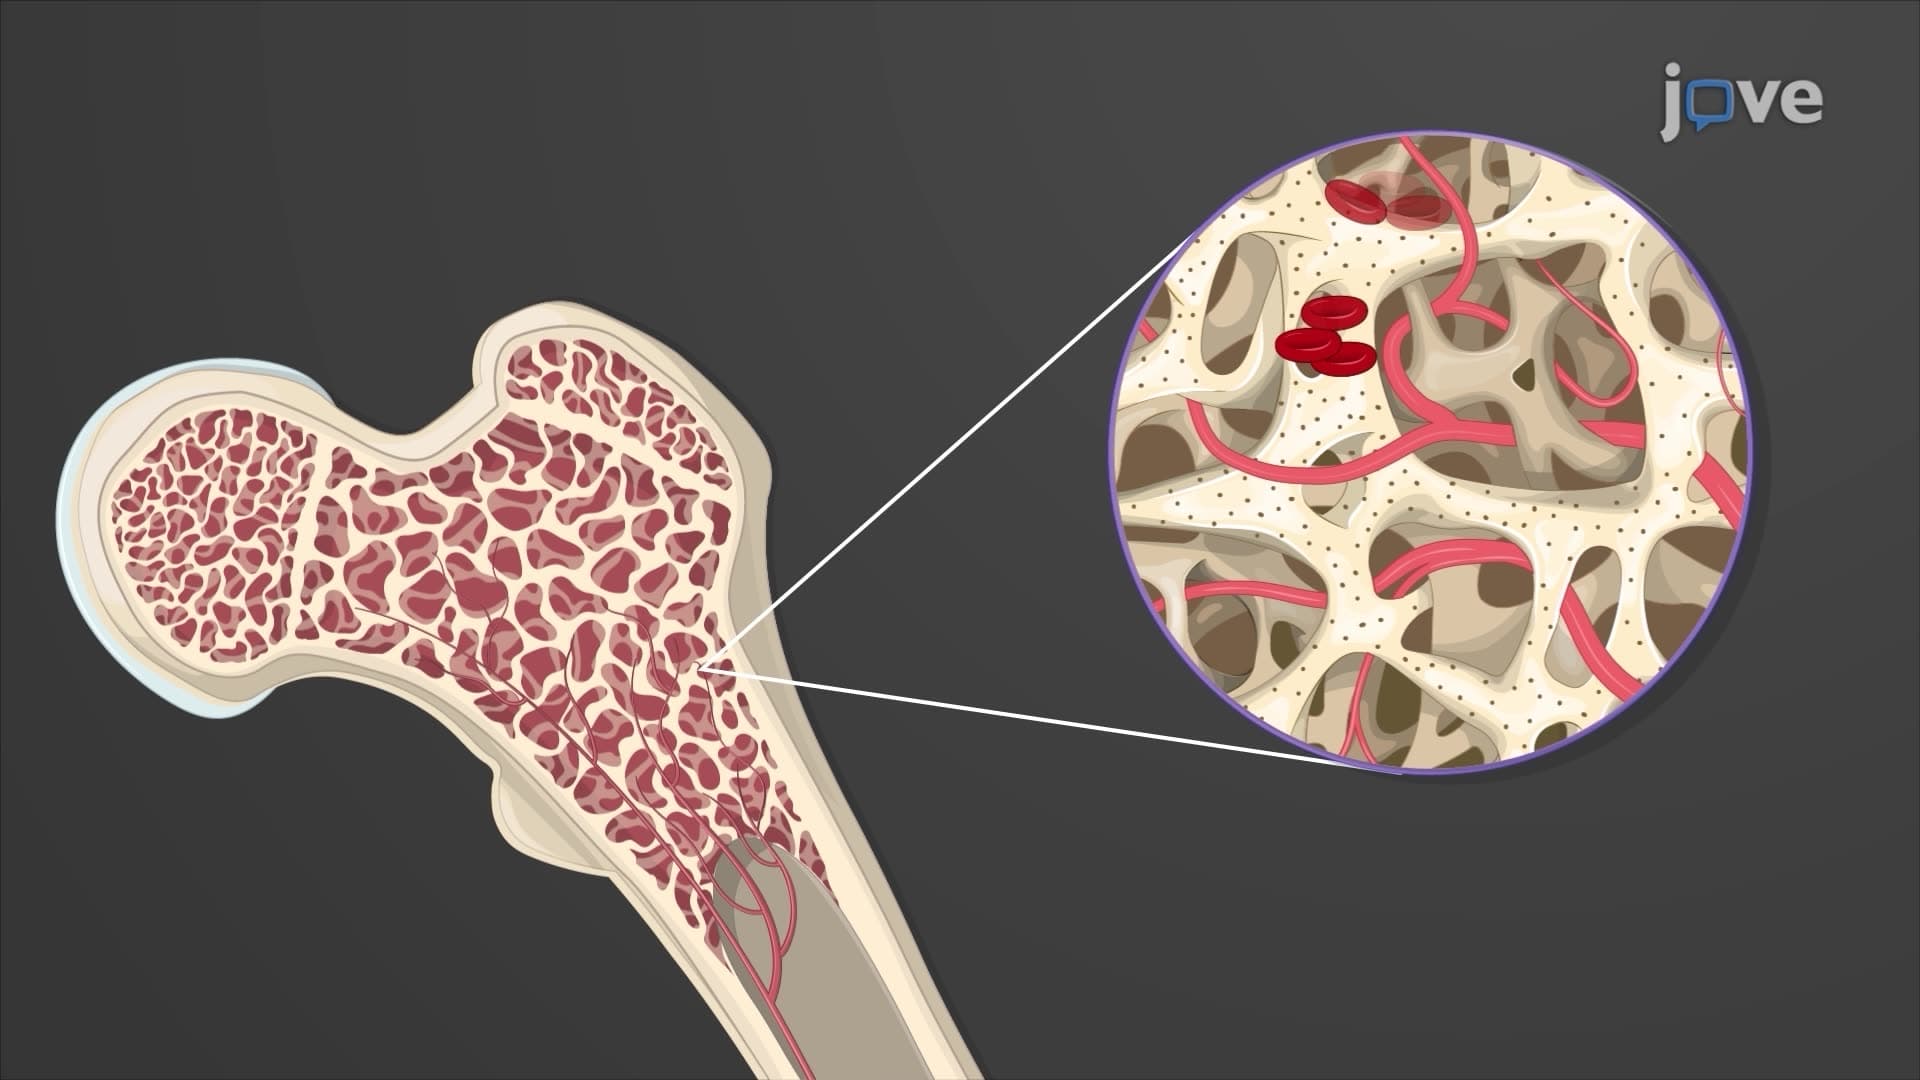
Lifecycle of Erythrocytes
The resident phagocytic macrophages deal with these damaged cells by engulfing them and separating their globin and heme groups.
 01:22
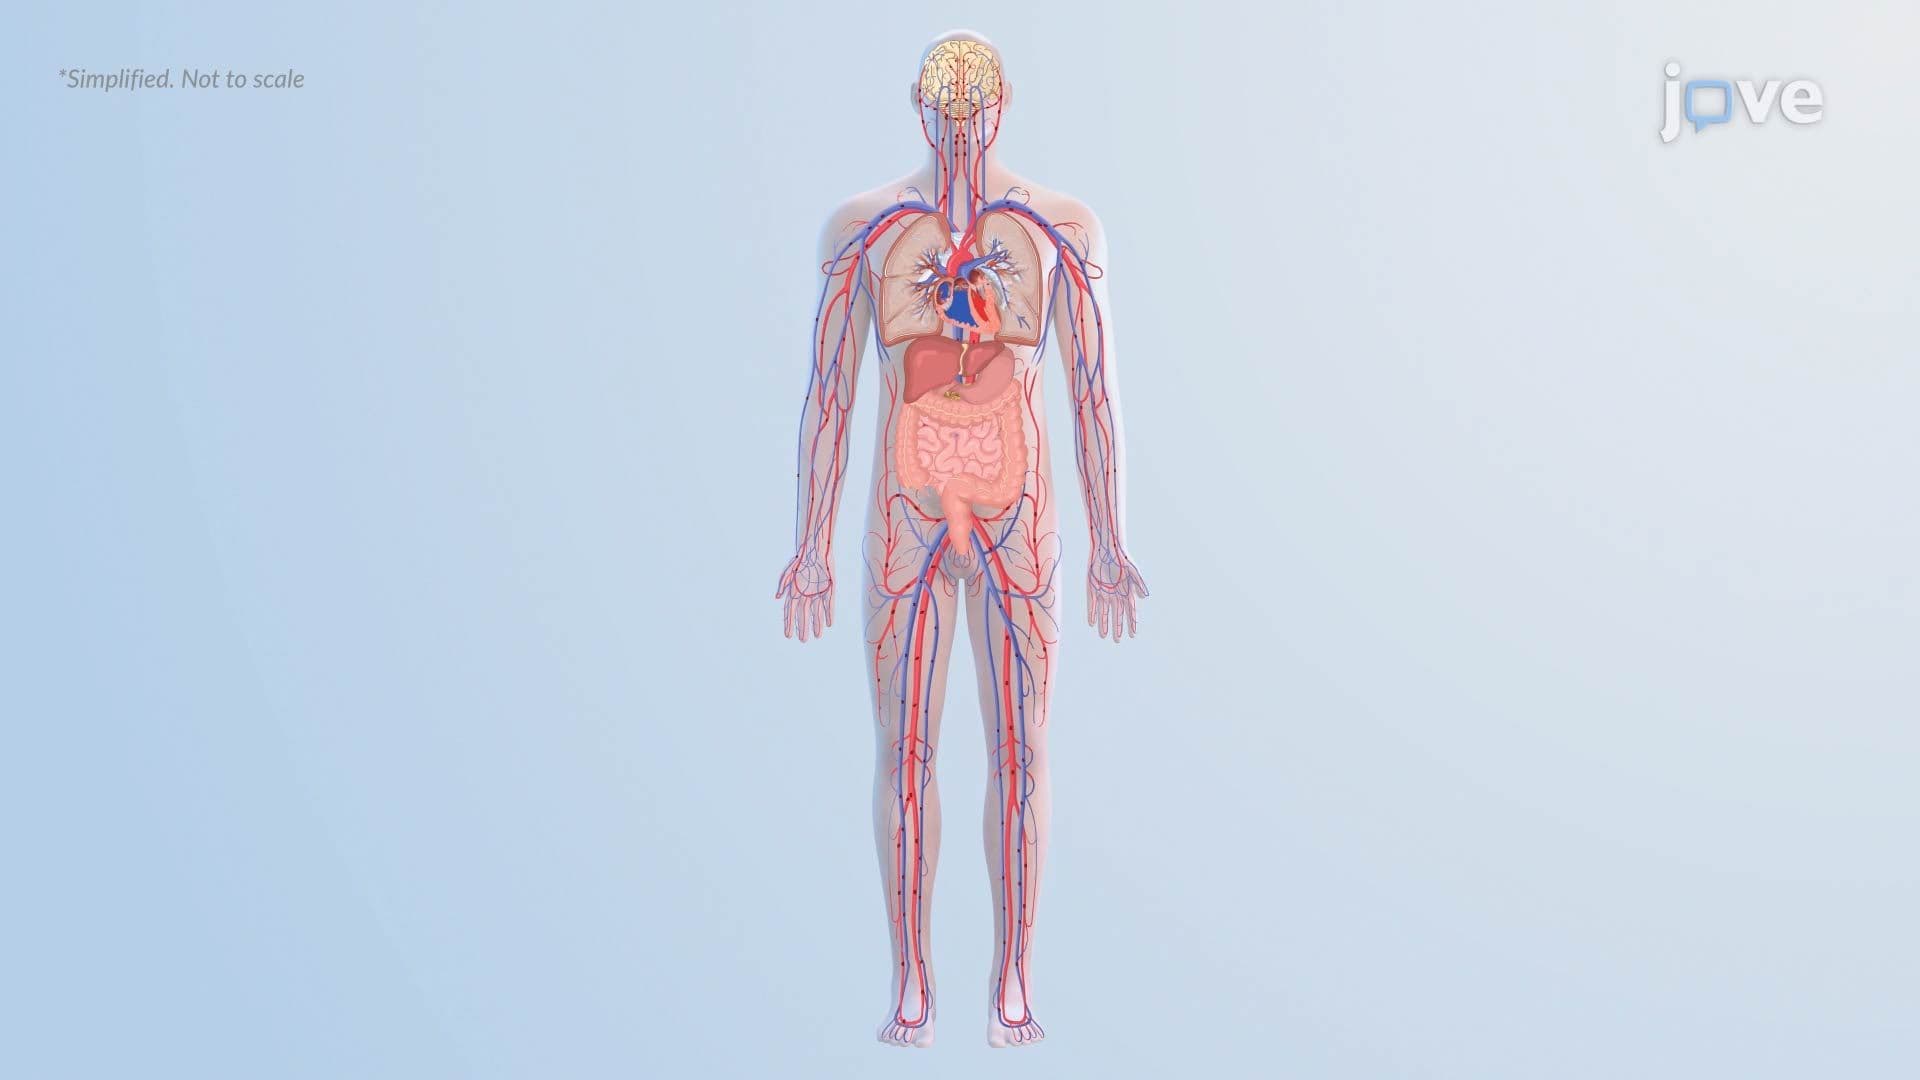
Portal Hypertension
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...