Related Experiment Video
Updated: Aug 19, 2026


Double-Staining Method to Detect Pectin in Plant-Fungus Interaction
Published on: February 4, 2022
Syndromic diagnosis and management of confirmed mushroom poisonings
1Programs in Community Preventive Medicine, School of Public Health, Louisiana State University Health Sciences Center, New Orleans, LA 70112, USA. jdiaz@lsuhsc.edu

Objective:
To assess the evolving global epidemiology of mushroom poisoning and to identify new and emerging mushroom poisonings and their treatments, a descriptive analysis and review of the world's salient scientific literature on mushroom poisoning was conducted.
Data Source:
Data sources from observation studies conducted over the period 1959-2002, and describing 28,018 mushroom poisonings since 1951, were collected from case reports, case series, regional descriptive studies, meta-analyses, and laboratory studies of mushroom poisonings and the toxicokinetics of mycotoxins.
Study Selection:
Studies included in the review were selected by a MEDLINE search, 1966-2004, an Ovid OLDMEDLINE search, 1951-1965, and a medical library search for sources published before 1951.
Data Extraction:
To better guide clinicians in establishing diagnoses and implementing therapies, despite confusing ingestion histories, data were extracted to permit an expanded syndromic classification of mushroom poisoning based on presentation timing and target organ systemic toxicity.
Data Synthesis:
The final 14 major syndromes of mushroom poisoning were stratified first by presentation timing and then by target organ systemic toxicity and included early (<6 hrs), late (6-24 hrs), and delayed syndromes (> or =1 day). There were eight early syndromes (four neurotoxic, two gastrointestinal, two allergic); three late syndromes (hepatotoxic, accelerated nephrotoxic, erythromelalgia); and three delayed syndromes (delayed nephrotoxic, delayed neurotoxic, rhabdomyolysis). Four new mushroom poisoning syndromes were classified including accelerated nephrotoxicity (Amanita proxima, Amanita smithiana), rhabdomyolysis (Tricholoma equestre, Russula subnigricans), erythromelalgia (Clitocybe amoenolens, Clitocybe acromelalgia), and delayed neurotoxicity (Hapalopilus rutilans). In addition, data sources were stratified by three chronological time periods with >1,000 confirmed mushroom ingestions reported and tested for any statistically significant secular trends in case fatalities from mushroom ingestions over the entire study period, 1951-2002.
Conclusions:
Since the 1950s, reports of severe and fatal mushroom poisonings have increased worldwide. Clinicians must consider mushroom poisoning in the evaluation of all patients who may be intoxicated by natural substances. Since information on natural exposures is often insufficient and incorrect, a new syndromic classification of mushroom poisoning is recommended to guide clinicians in making earlier diagnoses, especially in cases where only advanced critical care, including organ transplantation, may be life saving.
Related Concept Videos
 01:26
Pharmaceutical Poisoning: Treatment Strategies
 01:14
Prevention of Further Absorption of Poison
 01:26
Pharmaceutical Poisoning: Potential Scenarios
 01:30
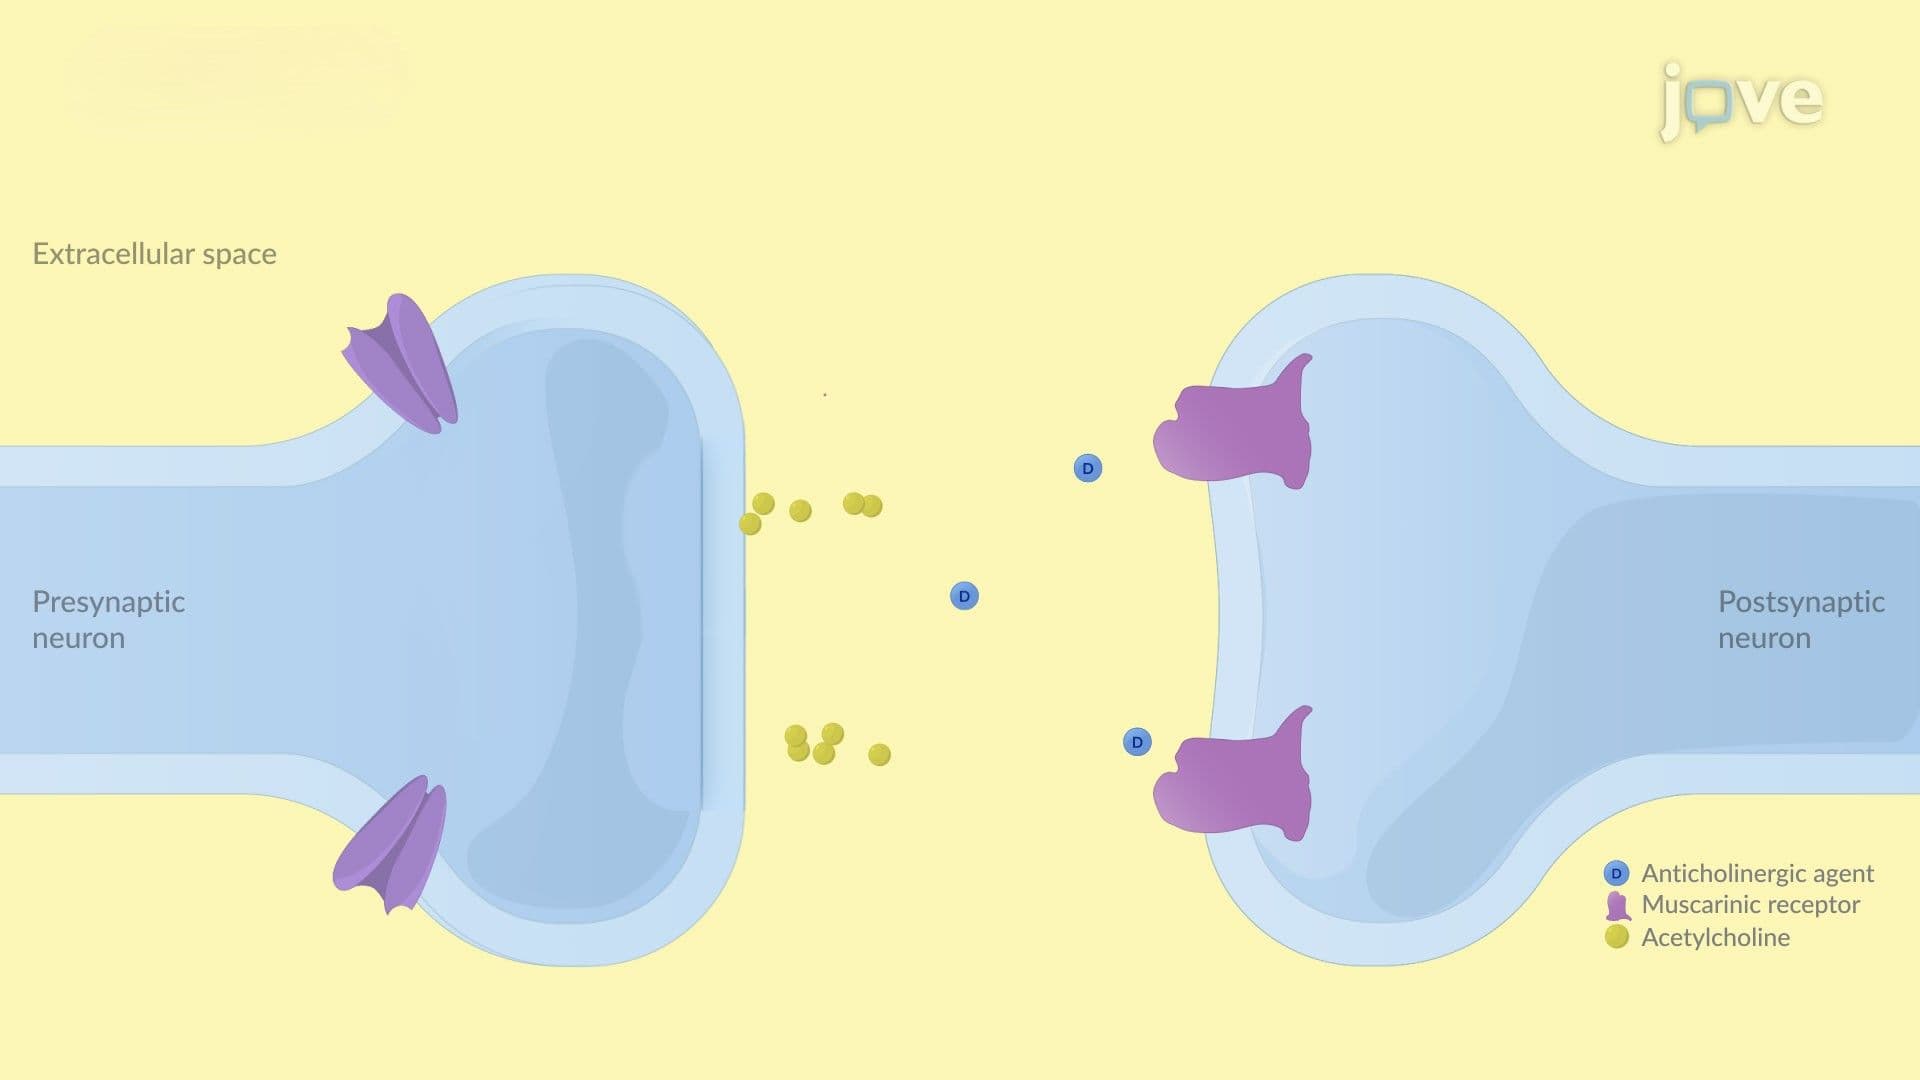
Toxidromes: Clinical Features
 01:26
Rocky Mountain Spotted Fever
 01:17
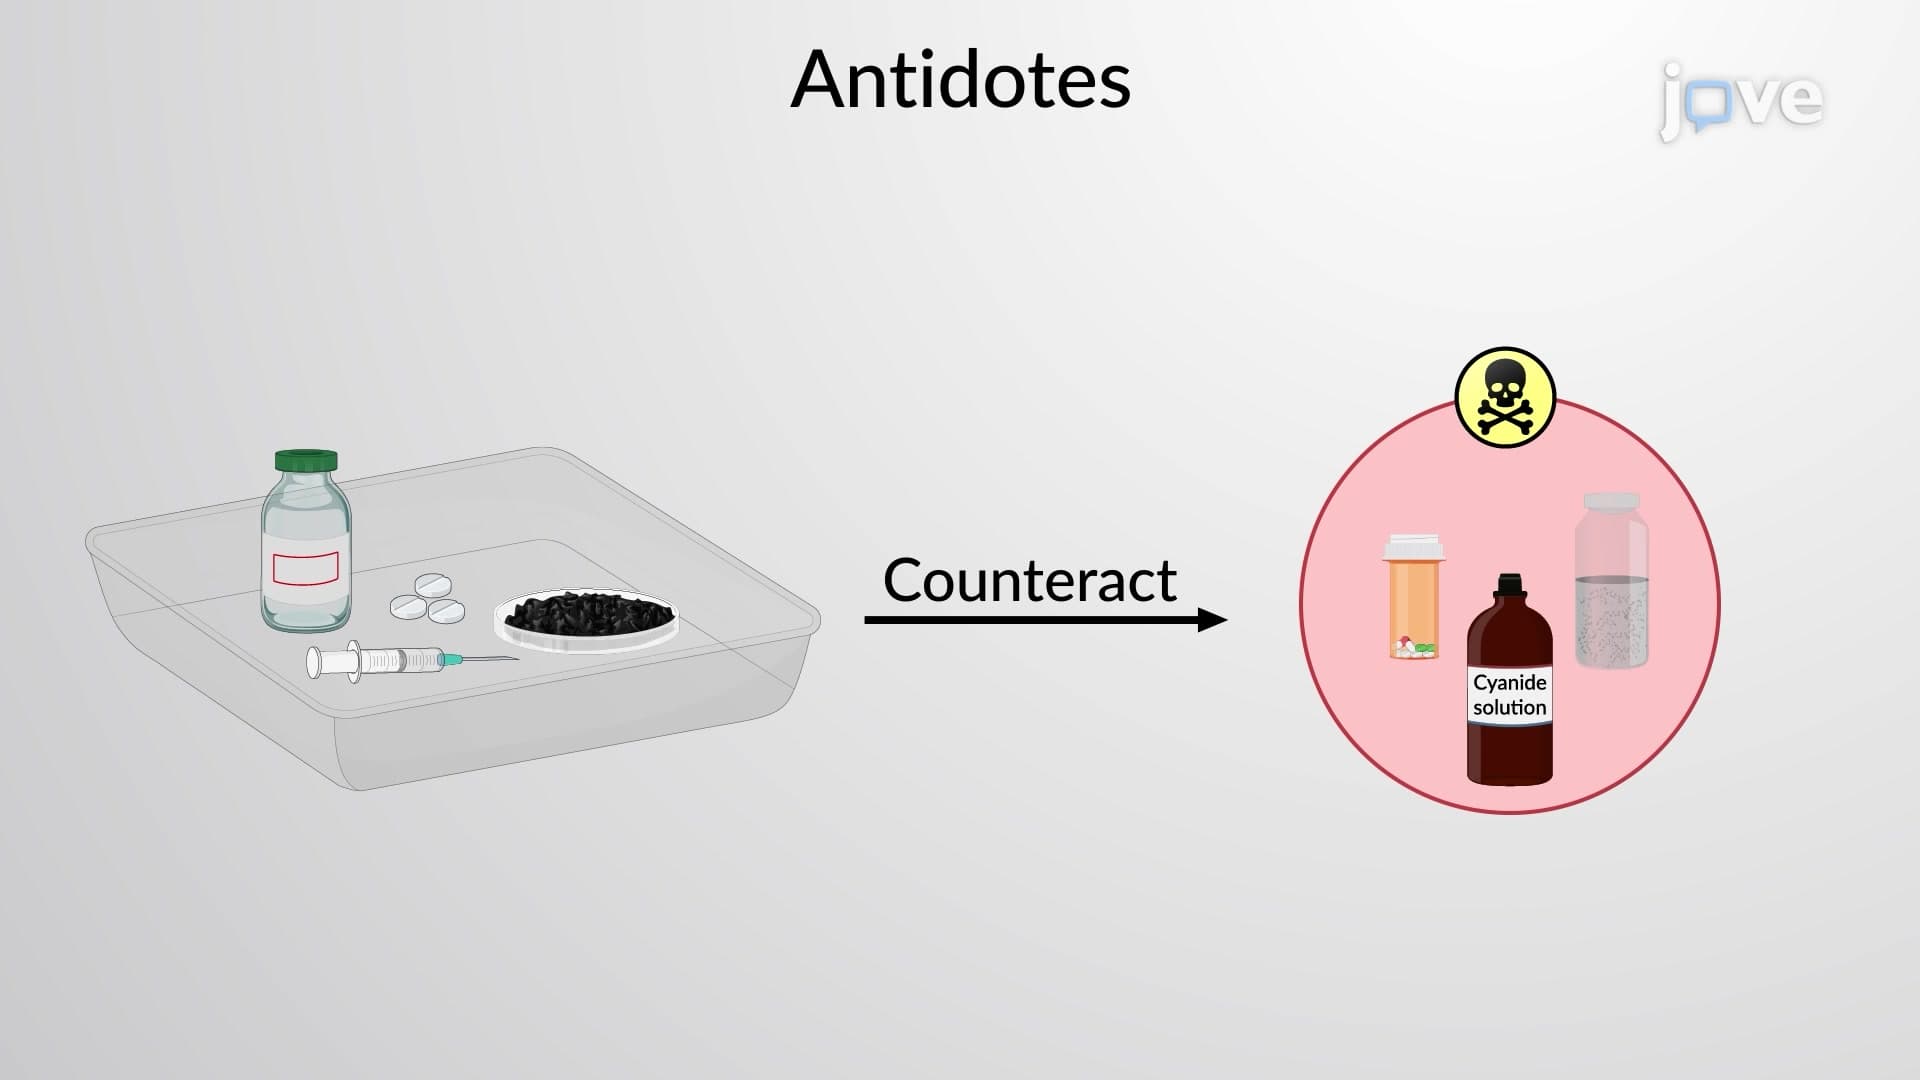
Antidotes
Specific antidotes operate by inhibiting the enzymes that control biochemical pathways, reducing the production of harmful metabolites.
An example of an antidote is atropine, which counteracts the detrimental effects of cholinesterase inhibitors. It achieves this by deactivating muscarinic receptors,...