Cryothermal ablation treatment of atrial flutter--experience with a new 9 French 8 mm tip catheter
Annibale S Montenero1, Nicola Bruno, Francesco Zumbo
1Cardiology Department and Arrhythmia Center of Policlinico MultiMedica, Sesto S. Giovanni, Milan, Italy. montenero@hotmail.com

Background:
Cardiac cryoablation has been used to successfully treat a variety of arrhythmias.
Objective:
This study documents our experience with a new 9 French (FR) 8 mm cryocatheter for ablation treatment of symptomatic atrial flutter.
Methods:
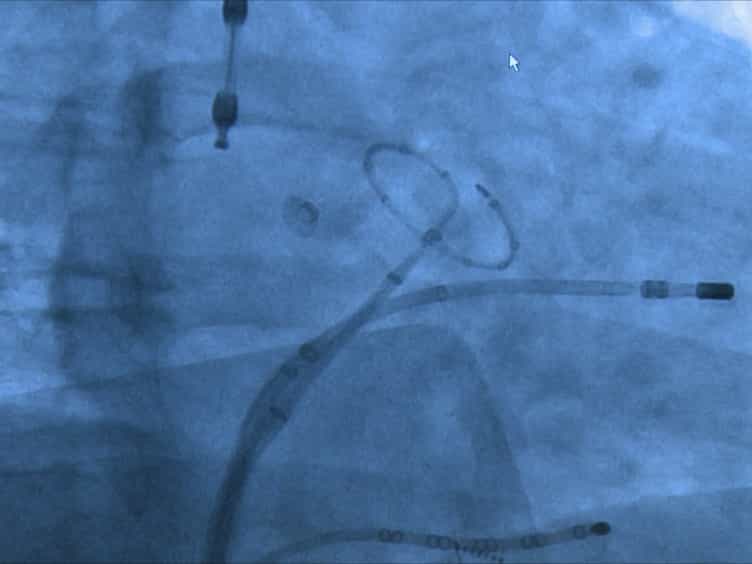
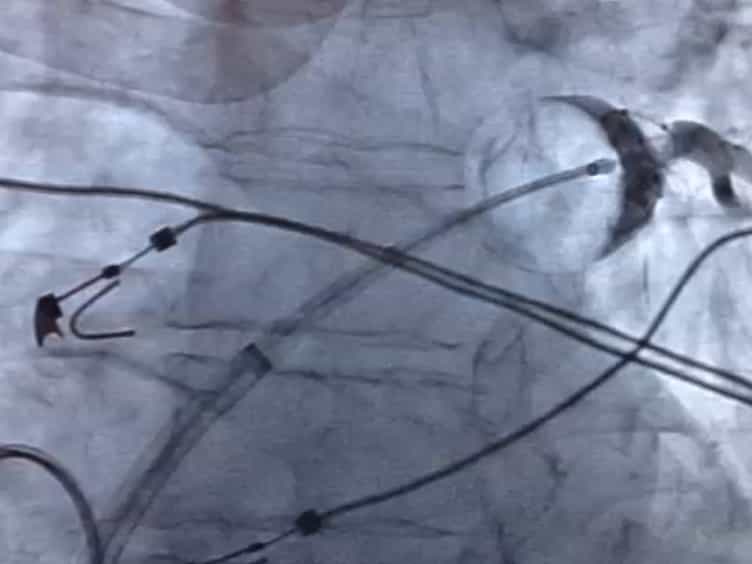
A total of 77 consecutive patients with symptomatic atrial flutter were treated. Electrophysiological studies (EPS) were performed with diagnostic catheters and ablation was performed with a 9FR, 8 mm tip, quadripolar cryocatheter (Freezor MAX catheter, CryoCath Technologies Inc., Kirkland, Canada). Cryoablation at -75 degrees C for 8 minutes was performed, beginning at the inferior rim of the coronary sinus (CS) os and creating a posterior line to the Eustachian ridge. Safety, bidirectional isthmus block at intervention, and recurrence at 3 months post procedure were assessed.
Results:
There were no adverse events reported. All patients remained free of discomfort on cryoenergy delivery. The acute success rate at intervention was 96% for all patients and 100% for those with common atrial flutter. Follow-up data from 47 patients showed 33 (70%) patients without conduction recurrence on repeat EPS at 3 months. Although, 1 (2%) patient had both symptom and conduction recurrence. Data available from 53 acutely successful patients at 6 month clinical follow-up showed that 48 (91%) patients were asymptomatic and 5 (9%) patients had recurrence documented by ECG and/or patient diary records.
Conclusions:
Our experience with a new 9FR, 8 mm tip, quadripolar cryocatheter yielded a high success rate at intervention and an excellent safety profile. Although repeat EPS at 3 months post ablation identified conduction recurrence in 30% of patients, at 6 month clinical follow-up only 9% of patients had recurrence. Further monitoring is necessary to assess whether the relatively low recurrence rate observed at 6 month clinical follow-up is maintained over the long term.