Related Experiment Video
Updated: Aug 19, 2026

Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
Effect of inspiratory time on tidal volume delivery in anesthesia and intensive care unit ventilators operating in
Avery Tung1, Melinda L Drum, Sherwin Morgan
1Department of Anesthesia and Critical Care, University of Chicago, Chicago, IL 60637, USA. atung@airway.uchicago.edu

Study Objective:
To compare the effect of inspiratory time and lung compliance on tidal volume (Vt) delivery in anesthesia and intensive care unit (ICU) ventilators operating in pressure control mode.
Setting:
Respiratory research laboratory of a tertiary care medical center.
Design:
Two anesthesia ventilators with pressure control capability (Narkomed 6000, Drager Medical, Inc, Telford, Pa, and the Datex-Ohmeda Aestiva 5, Datex-Ohmeda, Inc, Madison, Wis) and one critical care ventilator (Puritan Bennett 7200, Puritan-Bennett, Pleasanton, Calif) were studied under varying inspiratory time and lung compliance conditions using a mechanical lung model.
Intervention:
Each ventilator was set to pressure control mode at a fixed inspiratory/expiratory (I/E) ratio. The respiratory rate (RR) was varied between 6 and 28 breaths per minute. Lung compliance and inspiratory time settings were set to simulate clinical conditions known to affect anesthesia ventilator performance.
Measurements:
Inspiratory flow, Vts, and peak airway pressures were measured using the on-board monitor for each ventilator, and confirmed with the Bicore CP-100 pulmonary mechanics monitor (Bicore Monitoring Systems, Inc, Irvine, Calif). To assess differences in inspiratory flow between ventilators, airway pressures were continuously monitored during inspiration.
Main Results:
Increasing RRs caused delivered Vts to decrease for all ventilators. However, decreases in Vts were significantly larger for anesthesia than for ICU ventilators. At a lung compliance of 0.02 L/cm H(2)O and set Vt of 700 mL, Vt delivery for the Puritan Bennett 7200 ventilator remained at 88% of baseline, but decreased to 76% for the Aestiva 5 when RRs were increased from 6 to 28 breaths per minute (P < .0025). Airway pressure tracings demonstrated a slower increase in inspiratory airway pressure for the Aestiva 5 than for the other ventilators.
Conclusion:
Differences in inspiratory flow delivery between ICU and anesthesia ventilators can cause differences in Vt delivery when the pressure control mode is used at high RRs. These differences can significantly impact the perioperative care of critically ill patients requiring ventilatory support.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:24
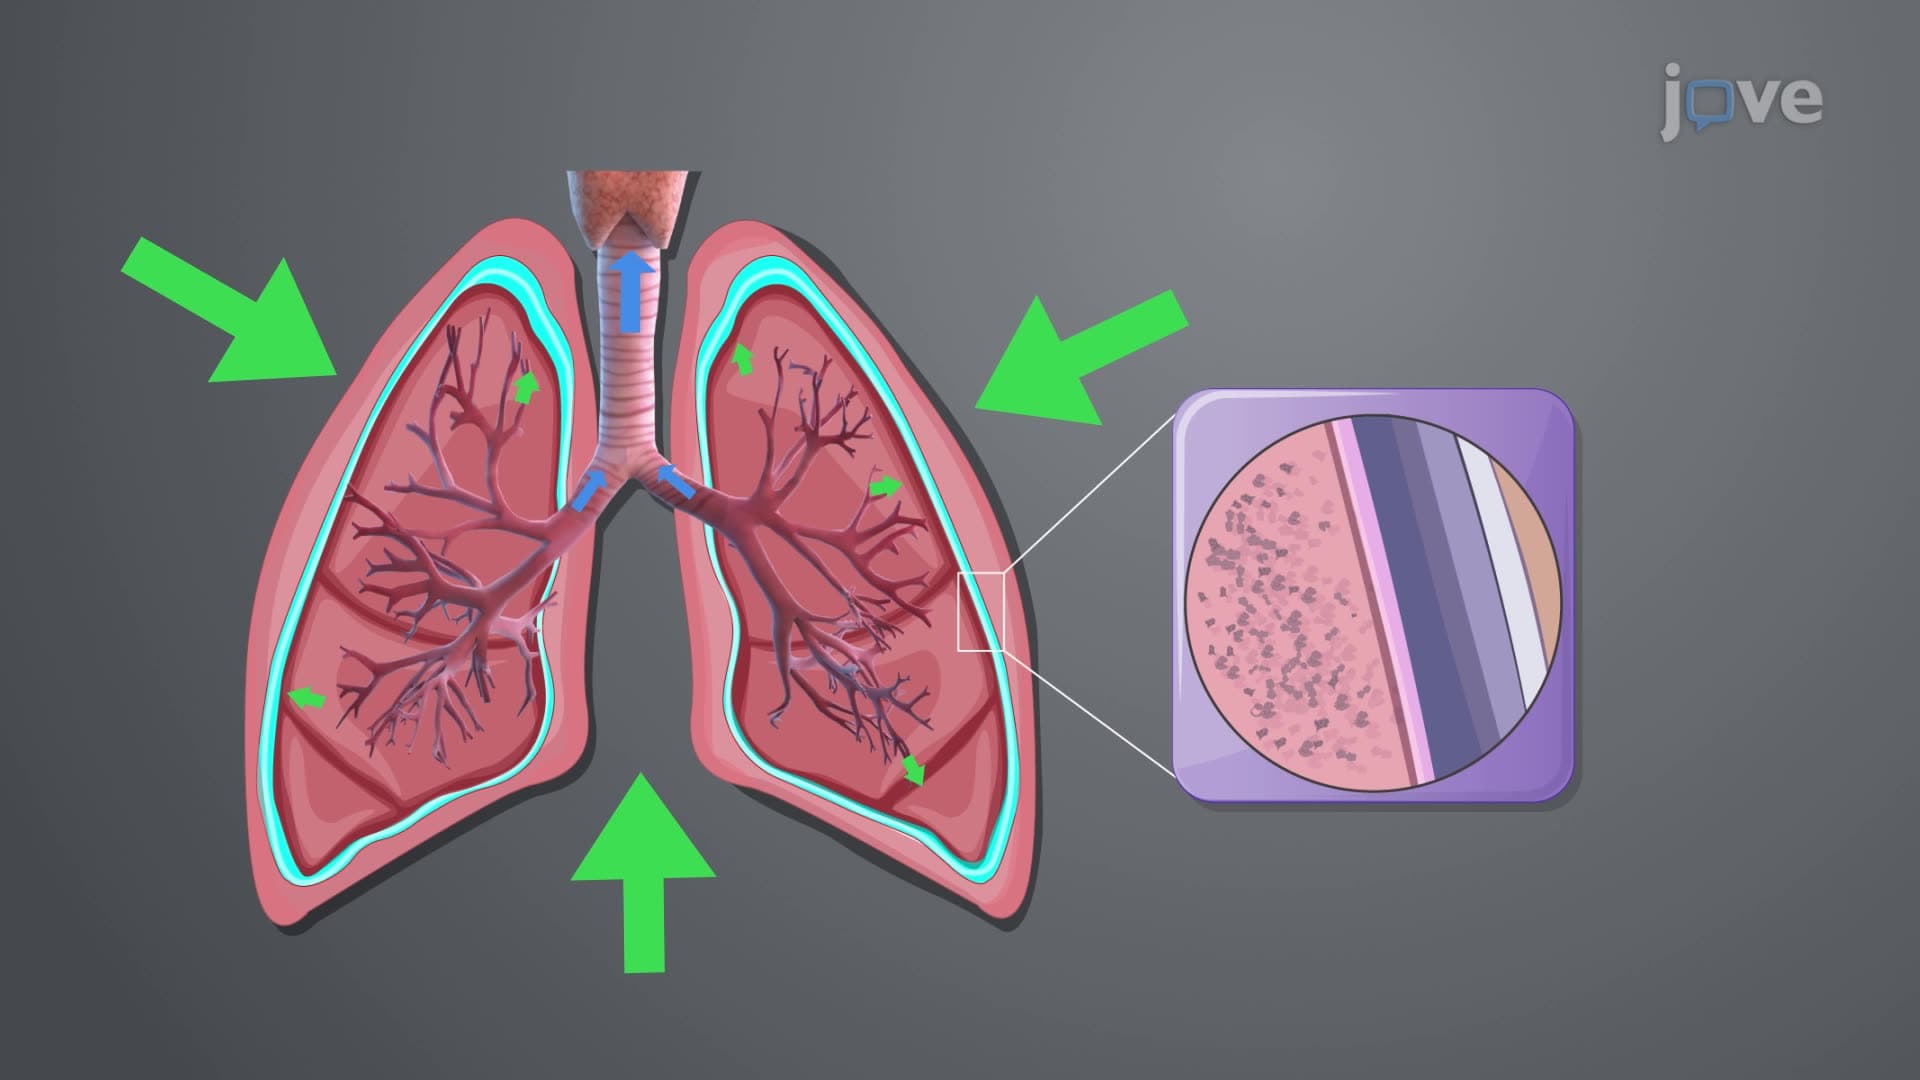
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:24
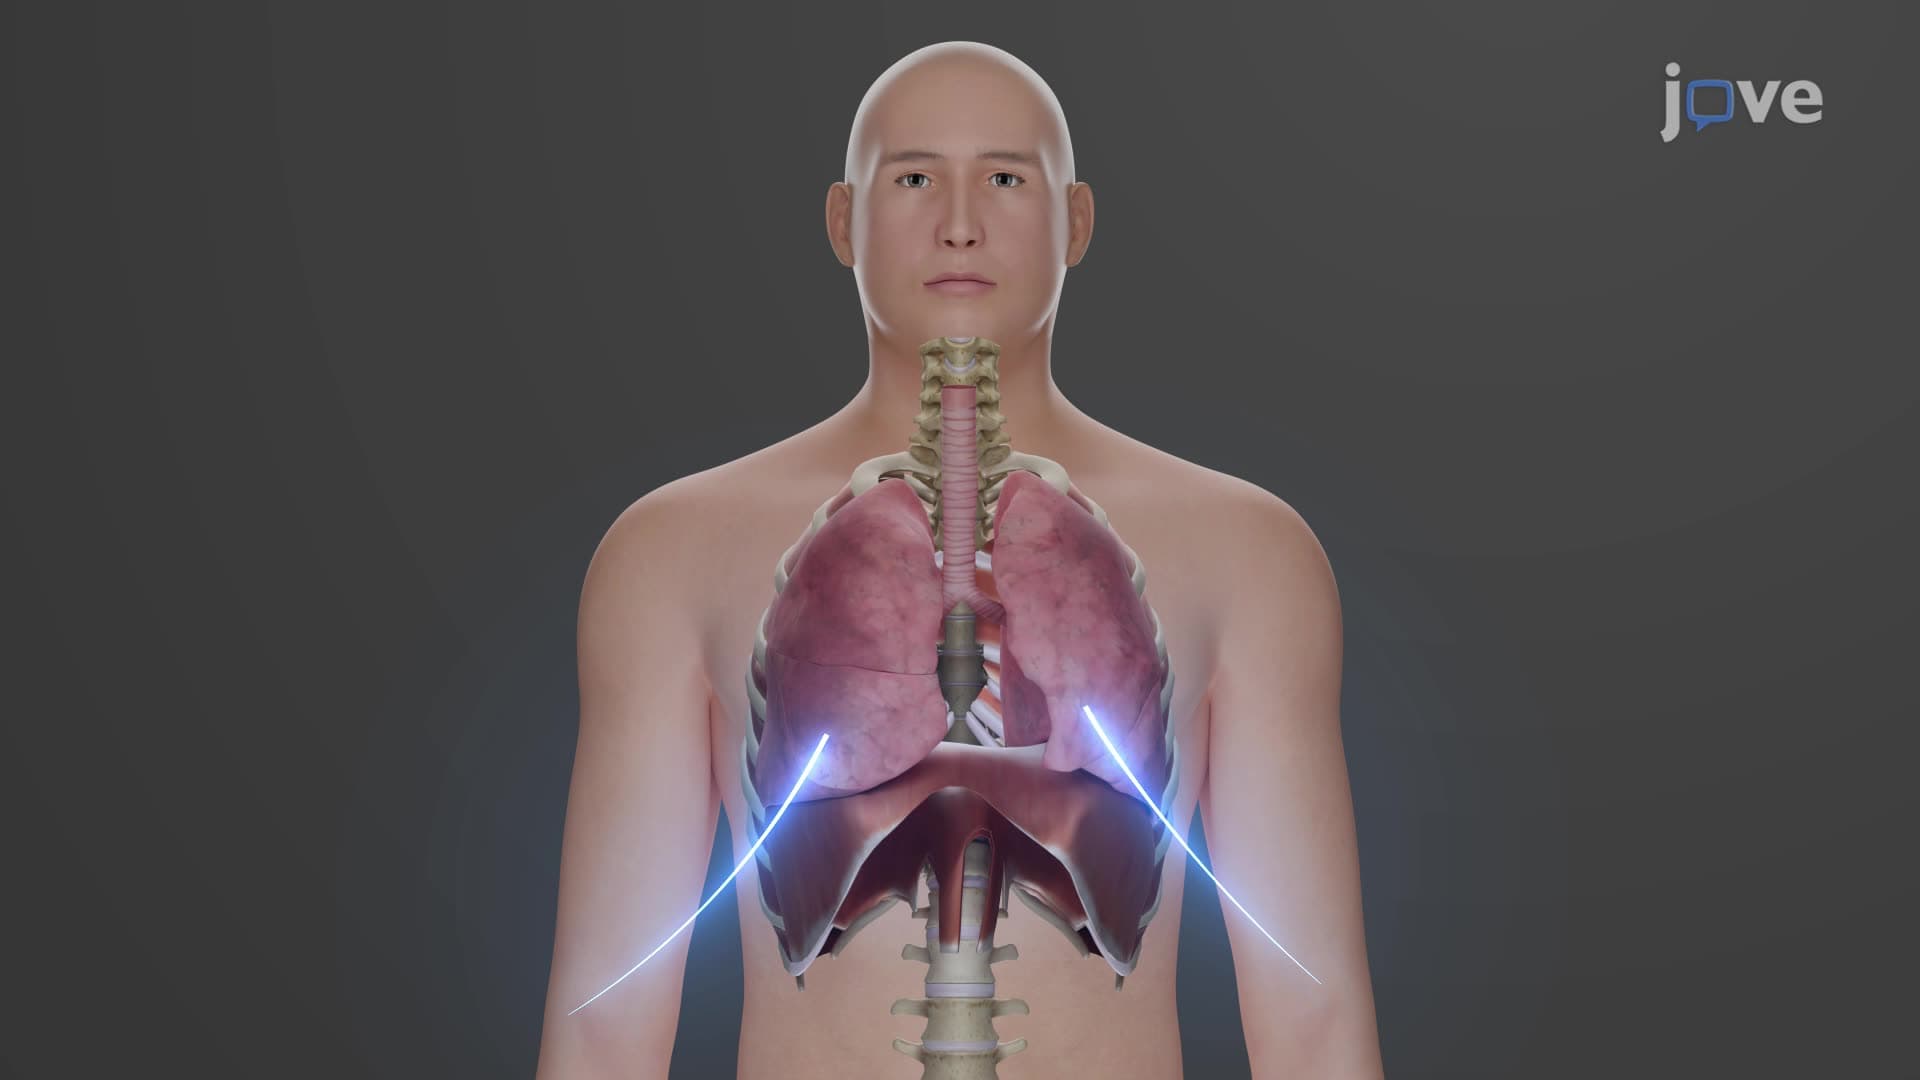
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...