Related Experiment Video
Updated: Aug 19, 2026
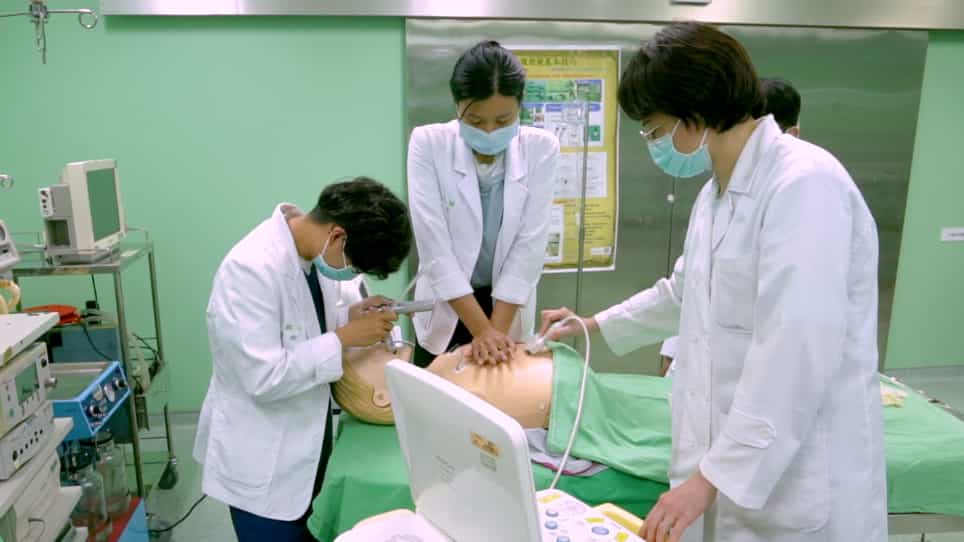
Ultrasonographic Assessment During Cardiopulmonary Resuscitation
Published on: October 24, 2020
Incomplete chest wall decompression: a clinical evaluation of CPR performance by EMS personnel and assessment of
Tom P Aufderheide1, Ronald G Pirrallo, Demetris Yannopoulos
1Department of Emergency Medicine, Medical College of Wisconsin, 9200W. Wisconsin Avenue, FEH Room 1870, Milwaukee, WI 53226, USA.

Background:
Complete chest wall recoil improves hemodynamics during cardiopulmonary resuscitation (CPR) by generating relatively negative intrathoracic pressure and thus draws venous blood back to the heart, providing cardiac preload prior to the next chest compression phase.
Objective:
Phase I was an observational case series to evaluate the quality of chest wall recoil during CPR performed by emergency medical services (EMS) personnel on patients with an out-of-hospital cardiac arrest. Phase II was designed to assess the quality of CPR delivered by EMS personnel using an electronic test manikin. The goal was to determine if a change in CPR technique or hand position would improve complete chest wall recoil, while maintaining adequate duty cycle, compression depth, and correct hand position placement. Standard manual CPR and three alternative manual CPR approaches were assessed.
Methods And Results:
Phase I--The clinical observational study was performed by an independent observer noting incomplete chest wall decompression and correlating that observation with electronically measured airway pressures during CPR in adult patients with out-of-hospital cardiac arrest. Rescuers were observed to maintain some residual and continuous pressure on the chest wall during the decompression phase of CPR, preventing full chest wall recoil, at some time during resuscitative efforts in 6 (46%) of 13 consecutive adults (average +/- S.D. age 63 +/-5.8 years). Airway pressures were consistently positive during the decompression phase (>0 mmHg) during those observations. Phase II: This randomized prospective trial was performed on an electronic test manikin. Thirty EMS providers (14 EMT-Basics, 5 EMT-Intermediates, and 11 EMT-Paramedics), with an average age +/- S.D. of 32 +/- 8 years and 6.5 +/- 4.2 years of EMS experience, performed 3 min of CPR on a Laerdal Skill Reporter CPR manikin using the Standard Hand Position followed by 3 min of CPR (in random order) using three alternative CPR techniques: (1) Two-Finger Fulcrum Technique--lifting the heel of the hand slightly but completely off the chest during the decompression phase of CPR using the thumb and little finger as a fulcrum; (2) Five-Finger Fulcrum Technique--lifting the heel of the hand slightly but completely off the chest during the decompression phase of CPR using all five fingers as a fulcrum; and (3) Hands-Off Technique--lifting the heel and all fingers of the hand slightly but completely off the chest during the decompression phase of CPR. These EMS personnel did not know the purpose of the studies prior to or during this investigation. Adequate compression depth was poor for all hand positions tested and ranged only from 29.9 to 48.5% of all compressions. When compared with the Standard Hand Position, the Hands-Off Technique decreased mean compression duty cycle from 46.9 +/- 6.4% to 33.3 +/- 4.6%, (P < 0.0001) but achieved the highest rate of complete chest wall recoil (95.0% versus 16.3%, P < 0.0001) and was 129 times more likely to provide complete chest wall recoil (OR: 129.0; CI: 43.4-382.0). There were no significant differences in accuracy of hand placement, depth of compression, or reported increase in fatigue or discomfort with its use compared with the Standard Hand Position.
Conclusions:
Incomplete chest wall decompression was observed at some time during resuscitative efforts in 6 (46%) of 13 consecutive adult out-of-hospital cardiac arrests. The Hands-Off Technique decreased compression duty cycle but was 129 times more likely to provide complete chest wall recoil (OR: 129.0; CI: 43.4-382.0) compared to the Standard Hand Position without differences in accuracy of hand placement, depth of compression, or reported increase in fatigue or discomfort with its use. All forms of manual CPR tested (including the Standard Hand Position) in professional EMS rescuers using a recording manikin produced an inadequate depth of compression more than half the time. These data support development and testing of more effective means to deliver manual as well as mechanical CPR.

Related Concept Videos
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:23
Cardiopulmonary Resuscitation III: AED Use