Related Experiment Video
Updated: Aug 19, 2026
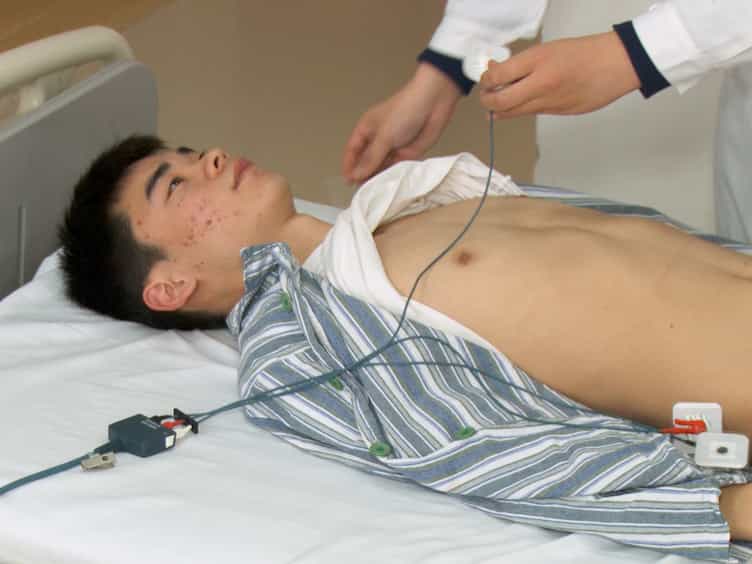

Measuring the Carotid to Femoral Pulse Wave Velocity (Cf-PWV) to Evaluate Arterial Stiffness
Published on: May 3, 2018
Decrease of arterial stiffness at common carotid artery in hypothyroid patients by normalization of thyroid function
Toshiki Nagasaki1, Masaaki Inaba, Yasuro Kumeda
1Department of Metabolism, Endocrinology and Molecular Medicine, Osaka City University Graduate School of Medicine, 1-4-3, Asahi-machi, Abeno-ku, Osaka 545-8585, Japan.

This study examined the effect of hypothyroidism on arterial stiffening and the effect of levothyroxine (l-T(4)) replacement. The arterial stiffness index beta (stiffness beta) and intima-media thickness (IMT), a parameter of arterial stiffening and thickening, respectively, were determined in common carotid artery (CCA) by ultrasonography in 30 hypothyroid patients before and after 1 year of normalization of thyroid function by l-T(4) replacement. Baseline CCA stiffness beta and IMT was significantly higher in the hypothyroid patients than in age- and sex-matched normal controls [9.46 +/- 0.93 vs. 8.02 +/- 0.91 (mean +/- SE); P < 0.05, 0.635 +/- 0.018 mm vs. 0.541 +/- 0.019 mm; P < 0.005, respectively]. In multivariate analysis, baseline stiffness beta was significantly associated with baseline levels of IMT (r = 0.457, P = 0.0311), FT(4) (r = -0.413, P = 0.0169), and a plasma vascular injury marker, von Willebrand factor (vWF) (r = 0.412, P = 0.0261). During 1 year of euthyroidism, 22 and 29 out of 30 patients showed significant decreases of stiffness beta and IMT to normal respective level, from 9.46 +/- 0.93 to 7.58 +/- 0.34 and from 0.635 +/- 0.018 to 0.552 +/- 0.015 mm, respectively. Change in stiffness beta during l-T(4) therapy correlated significantly in a negative manner with baseline levels of age (r = -0.465, P = 0.011) and IMT (r = -0.406, P = 0.029). Stiffness beta after but not before l-T(4) therapy showed a tendency towards a positive correlation with age. This study suggested that increases of arterial thickening, and plasma vWF, and a reduction in serum FT(4) might have an important role independently in the increased arterial stiffening in hypothyroid patients. Furthermore, it was demonstrated that sustained euthyroidism might have the potential to reverse arterial stiffening in addition to thickening in hypothyroid patients.
This study examined the effect of hypothyroidism on arterial stiffening and the effect of levothyroxine (l-T(4)) replacement. The arterial stiffness index beta (stiffness beta) and intima-media thickness (IMT), a parameter of arterial stiffening and thickening, respectively, were determined in common carotid artery (CCA) by ultrasonography in 30 hypothyroid patients before and after 1 year of normalization of thyroid function by l-T(4) replacement. Baseline CCA stiffness beta and IMT was significantly higher in the hypothyroid patients than in age- and sex-matched normal controls [9.46 +/- 0.93 vs. 8.02 +/- 0.91 (mean +/- SE); P < 0.05, 0.635 +/- 0.018 mm vs. 0.541 +/- 0.019 mm; P < 0.005, respectively]. In multivariate analysis, baseline stiffness beta was significantly associated with baseline levels of IMT (r = 0.457, P = 0.0311), FT(4) (r = -0.413, P = 0.0169), and a plasma vascular injury marker, von Willebrand factor (vWF) (r = 0.412, P = 0.0261). During 1 year of euthyroidism, 22 and 29 out of 30 patients showed significant decreases of stiffness beta and IMT to normal respective level, from 9.46 +/- 0.93 to 7.58 +/- 0.34 and from 0.635 +/- 0.018 to 0.552 +/- 0.015 mm, respectively. Change in stiffness beta during l-T(4) therapy correlated significantly in a negative manner with baseline levels of age (r = -0.465, P = 0.011) and IMT (r = -0.406, P = 0.029). Stiffness beta after but not before l-T(4) therapy showed a tendency towards a positive correlation with age. This study suggested that increases of arterial thickening, and plasma vWF, and a reduction in serum FT(4) might have an important role independently in the increased arterial stiffening in hypothyroid patients. Furthermore, it was demonstrated that sustained euthyroidism might have the potential to reverse arterial stiffening in addition to thickening in hypothyroid patients.
Related Concept Videos
 01:23
Hypothyroidism II: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:26
Atherosclerosis III: Management
 01:25
Hyperthyroidism I: Introduction
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:29
Hypertension II: Pathophysiology