Related Experiment Video
Updated: Aug 19, 2026
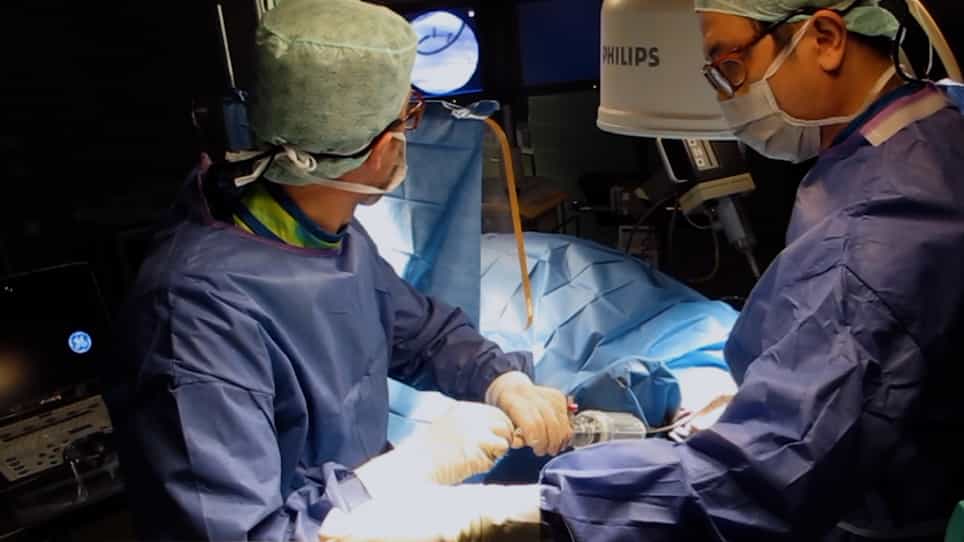

Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
Long-term outcomes of valve replacement with modern prostheses in young adults
Marc Ruel1, Alexander Kulik, Buu K Lam
1Division of Cardiac Surgery, University of Ottawa Heart Institute, 40 Ruskin Street, Suite 3403, Ottawa, Ontario, Canada K1Y 4W7. mruel@ottawaheart.ca

Objectives:
To examine the multiple impacts of valve replacement on the lives of young adults.
Methods:
Patients (N=500) between age 18 and 50 who had aortic valve replacement (AVR) and/or mitral valve replacement (MVR) with contemporary prostheses were followed annually. Events, functional status, and quality of life were examined with regression models.
Results:
Median follow-up was 7.1+/-5.3 years (maximum 26.7 years). Five, 10, and 15-year survival was 92.7+/-1.7, 88.3+/-2.4 and 80.1+/-4.7% after AVR, and 93.1+/-2.3, 79.5+/-4.3 and 71.5+/-5.4% after MVR, respectively. Survival decreased with concomitant coronary disease (hazard ratio (HR): 4.5) and preoperative LV grade (HR: 2.0/grade increase) in AVR patients, and with atrial fibrillation (HR: 5.5), coronary disease (HR: 5.7), preoperative left atrial diameter (HR: 3.0/cm increase) and NYHA class (HR: 2.1/class increase) in MVR patients. Despite reoperation, late survival was equivalent between bioprostheses and mechanical valves in both implant positions. The ten-year cumulative incidence of embolic stroke was 6.3+/-2.4% for mechanical AVR patients, 6.4+/-2.9% for bioprosthetic AVR patients, 12.7+/-3.9% for mechanical MVR patients, and 3.1+/-3.1% for bioprosthetic MVR patients. Atrial fibrillation (HR: 2.8) and smoking (HR: 4.0) were risk factors for stroke in MVR patients. In AVR patients, SF-12 physical scores, freedom from recurrent heart failure, and freedom from disability were significantly higher in bioprosthetic than mechanical valve patients. Career or income limitations were more often subjectively linked to a mechanical prosthesis in both implant positions.
Conclusions:
Late outcomes of modern prosthetic valves in young adults remain suboptimal. Bioprostheses deserve consideration in the aortic position, as mechanical valves are associated with lower physical capacity, a higher prevalence of disability, and poorer disease perception. Early surgical referral and atrial fibrillation surgery may improve survival after MVR.


Related Concept Videos
 01:26
Mitral Stenosis III: Medical Management
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:27
Mitral Stenosis IV: Nursing Management
 01:25
Aortic Regurgitation III: Medical Management
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:19
Mitral Valve Prolapse III: Nursing Management