Related Experiment Video
Updated: Aug 4, 2026


Catheterization of Intestinal Loops in Ruminants
Published on: June 11, 2009
[Duplication of the alimentary canal in infants and children]
A Pintér1, W Schubert, F Szemlédy
1Pécsi Orvostudományi Egyetem Gyermekgyógyászati Klinika, Budapest.

Insights
Alimentary tract duplications are rare congenital anomalies. Surgical removal is key, emphasizing careful preservation of the shared blood supply to avoid sacrificing healthy bowel tissue.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Congenital Anomalies
Context:
- Review of 30 alimentary tract duplications in 28 pediatric patients (1964-1989).
- Patients ranged from 1 day to 13 years; 80% presented before age 2.
- Common locations included thoracic, abdominal, and thoracoabdominal regions.
Purpose:
- To analyze the clinical presentation, diagnosis, and surgical management of alimentary tract duplications.
- To highlight diagnostic modalities and surgical considerations for optimal patient outcomes.
Summary:
- Most frequent symptoms were distended abdomen, vomiting, bowel obstruction, and palpable abdominal mass.
- Diagnostic tools included X-rays, ultrasonography, and barium studies.
- 23 duplications were cystic, 3 tubular; 18 patients required emergency surgery.
Impact:
- Surgical technique should prioritize preserving the shared blood supply to minimize sacrifice of normal bowel.
- Appropriate surgical intervention is crucial for preventing recurrence and managing symptoms effectively.
Abstract:
This is a review of 30 duplications of the alimentary tract in 28 patients treated at the Surgical Unit of the Children's Department of the Medical University of Pécs, Hungary and at the Department of Pediatric Surgery of the Medical Academy of Dresden, Germany, from 1964 to 1989. The ages of patients ranged from 1 day to 13 years, 80 per cent were less than 2 years of age at initial presentation. There were 6 thoracic, 20 abdominal and 2 thoracoabdominal duplications. Distended abdomen, vomiting, bowel obstruction and palpable abdominal mass were most frequently encountered. Plain thoracic and abdominal X-rays, ultrasonography, barium esophagogram, barium meal and enema were the most common diagnostic procedures. Emergency operative intervention was required in 18 patients. One infant died of an unrelated disease. Twenty-three duplications were cystic and 3 tubular. One patient had an appendiceal duplication, and another patient a flat lumenless duplication located on the perineum close to the anal opening. The surgical procedure--removal of the duplication--should not be more radical than necessary to eliminate the potential complaints and prevent recurrence. During surgery the common blood supply shared between the duplication and the native bowel must be carefully protected to avoid undue sacrifice of normal bowel.


Related Concept Videos
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the small...
 01:23
Renewal of Intestinal Stem Cells
 01:27
Histology of the Small Intestine
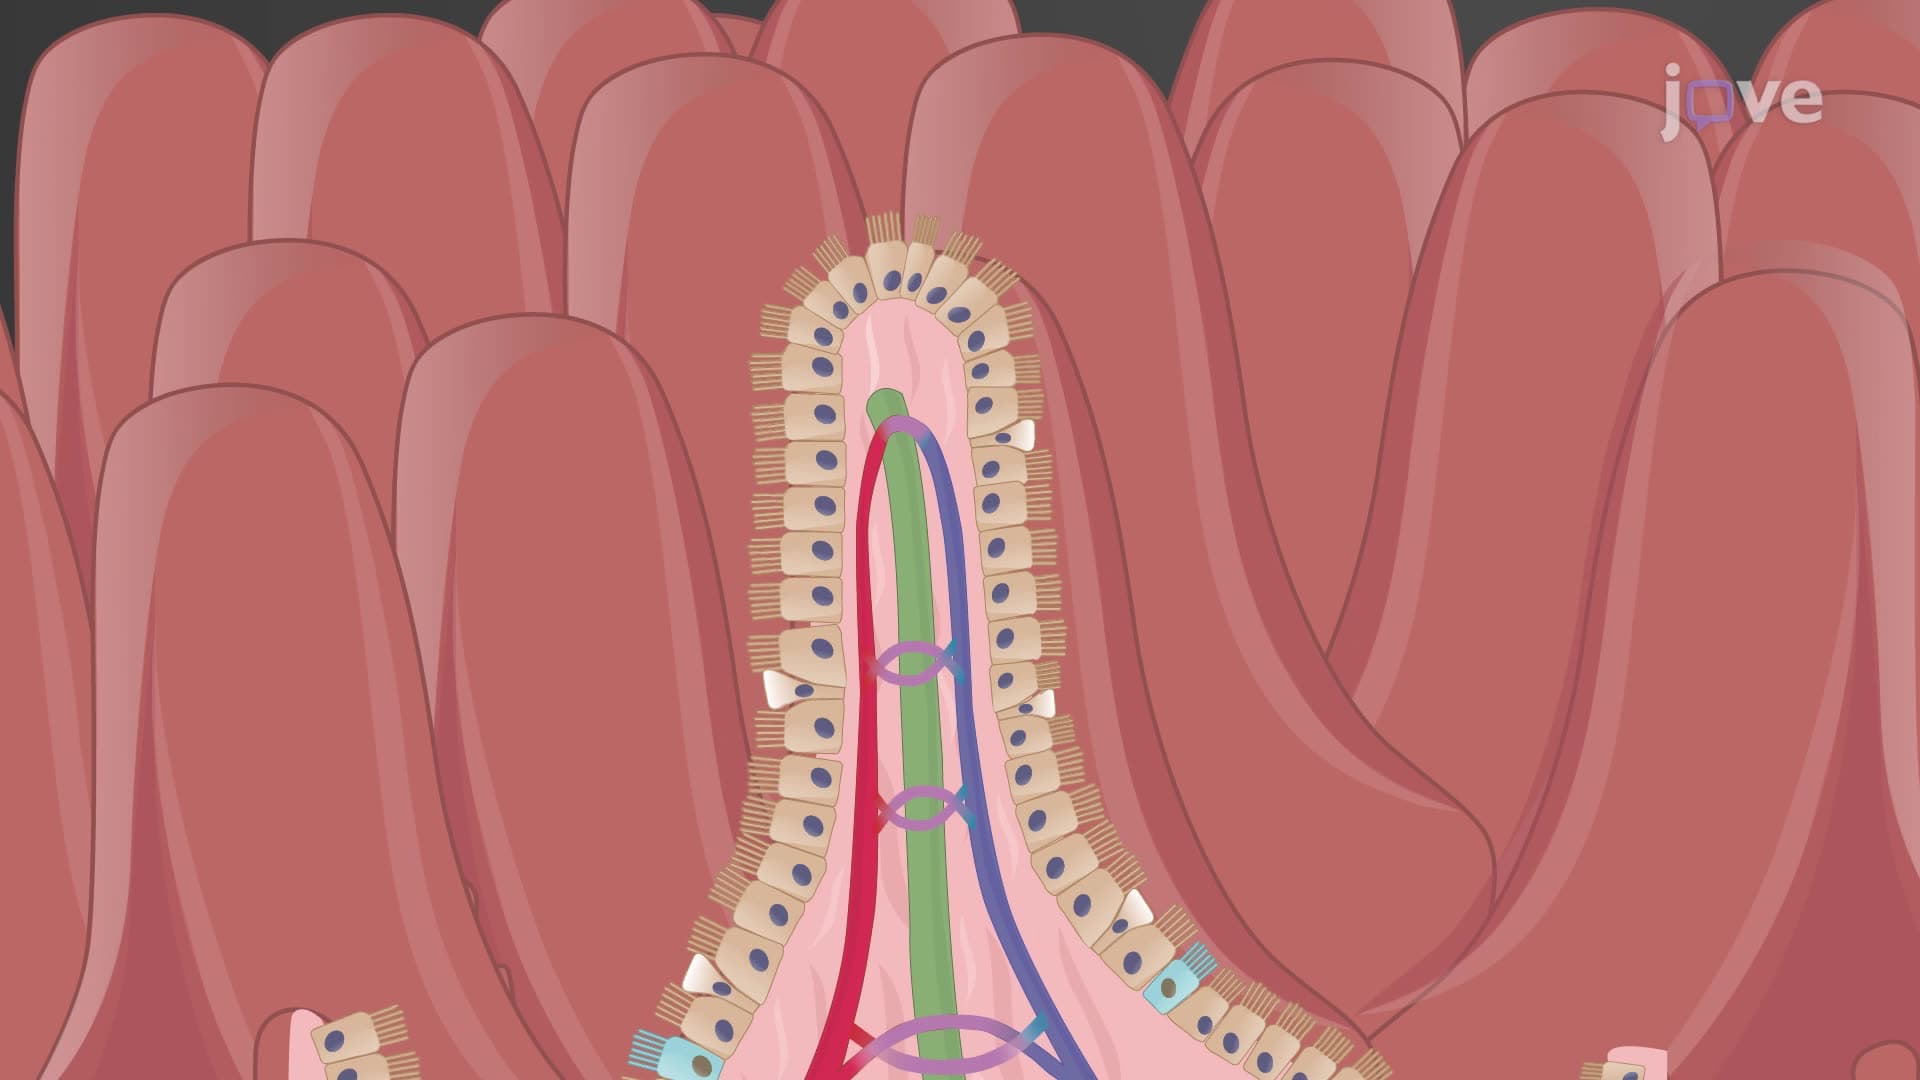
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:28
Development of the Oral Microbiota
 01:11
Pyloric Obstruction
 01:27
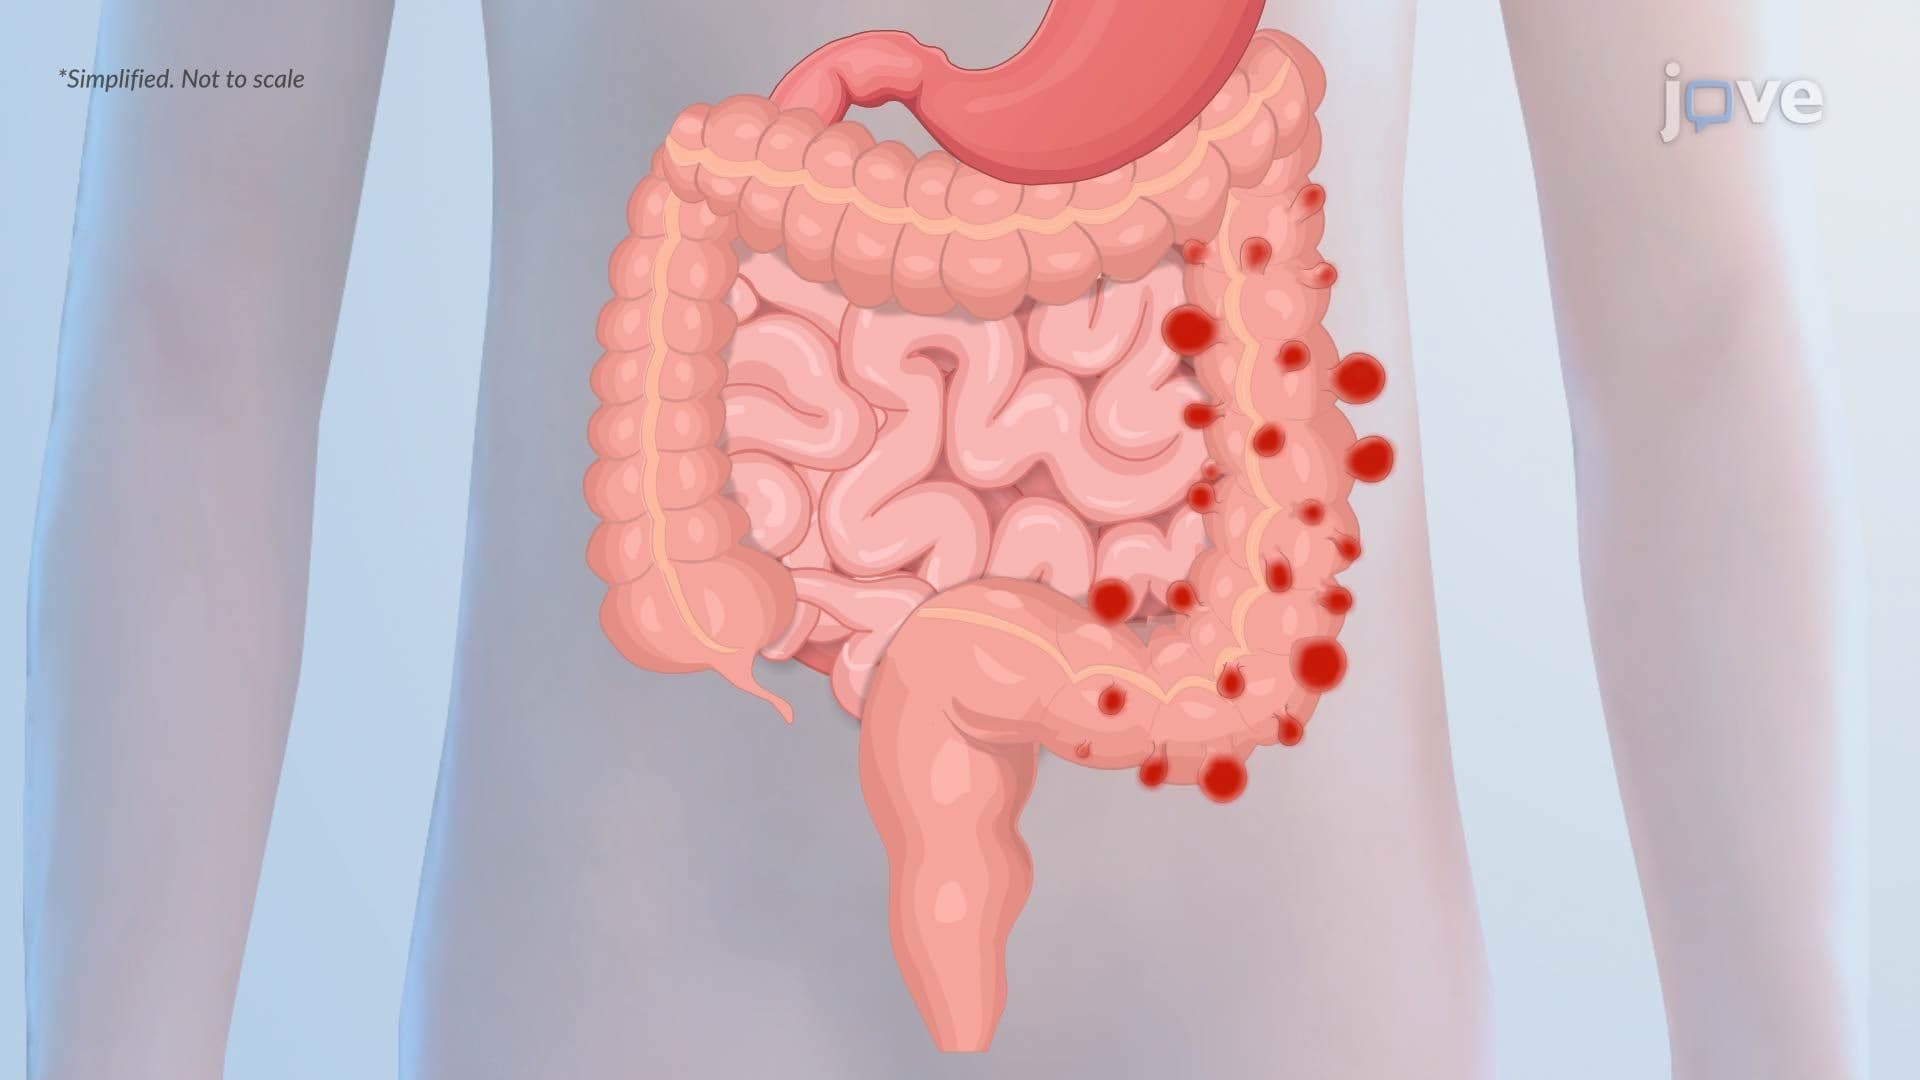
Diverticular Disease of the Colon