'Hair-on-end' skull changes resembling thalassemia caused by marrow expansion in uncorrected complex cyanotic heart disease
Related Experiment Video
Updated: Aug 7, 2026
Culture of Murine Embryonic Metatarsals: A Physiological Model of Endochondral Ossification
Published on: December 3, 2016
David M Walor1, Walter E Berdon, Sjirk J Westra
1Department of Radiology Children's Hospital of New York, Columbia University Medical Center, 3959 Broadway, New York, NY 10032, USA. Web2@columbia.edu

Insights
Rare skull changes, previously seen in children with cyanotic heart disease, are now observed in complex uncorrectable cases. These findings highlight a link between chronic hypoxia and specific bone abnormalities.
Area of Science:
- Pediatric Cardiology
- Radiology
- Hematology
Background:
- The "hair-on-end" skull finding, historically associated with thalassemia, was infrequently reported in children with cyanotic congenital heart disease (CCHD) in the mid-20th century.
- These changes were predominantly noted in patients with tetralogy of Fallot and D-transposition of the great arteries.
Observation:
- With advancements in surgical correction, these osseous changes have become exceedingly rare.
- They are now primarily observed in a limited cohort of pediatric patients with uncorrectable complex CCHD experiencing chronic hypoxia.
Findings:
- This report details two cases: a 5-year-old boy with uncorrectable CCHD exhibiting significant skull marrow expansion (evaluated by CT) and an 8-year-old with tetralogy of Fallot and pulmonary atresia (evaluated by plain skull radiographs).
- The precise incidence of these "hair-on-end" skull changes in contemporary pediatric CCHD populations remains undetermined.
Implications:
- The findings suggest a correlation between chronic hypoxemia in complex congenital heart disease and specific radiographic bone abnormalities.
- Further research is needed to ascertain the true prevalence of these changes and their clinical significance in surviving pediatric patients with complex CCHD.
Abstract:
"Hair-on-end" skull changes resembling thalassemia were rarely described in the 1950s and 1960s in children with cyanotic congenital heart diseases; these changes were described almost entirely in patients with tetralogy of Fallot or D-transposition of the great arteries. As these lesions have become correctable, the osseous changes, never common, seem now only to exist in a small number of patients with uncorrectable complex cyanotic congenital heart disease who survive in a chronic hypoxic state. We present two cases: a case of marked marrow expansion in the skull of a 5-year-old boy with uncorrectable cyanotic heart disease studied by CT, and a second case of an 8-year-old with tetralogy of Fallot and pulmonary atresia studied by plain skull radiographs. The true incidence of these findings is unknown.
More Related Videos
Related Concept Videos
 01:33
Pleiotropy
 01:14
Changes in Skin Color: Clinical Perspectives
Albinism
Albinism is a genetic disorder that affects (completely or partially) the coloring of skin, hair, and eyes. The defect is primarily...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:24
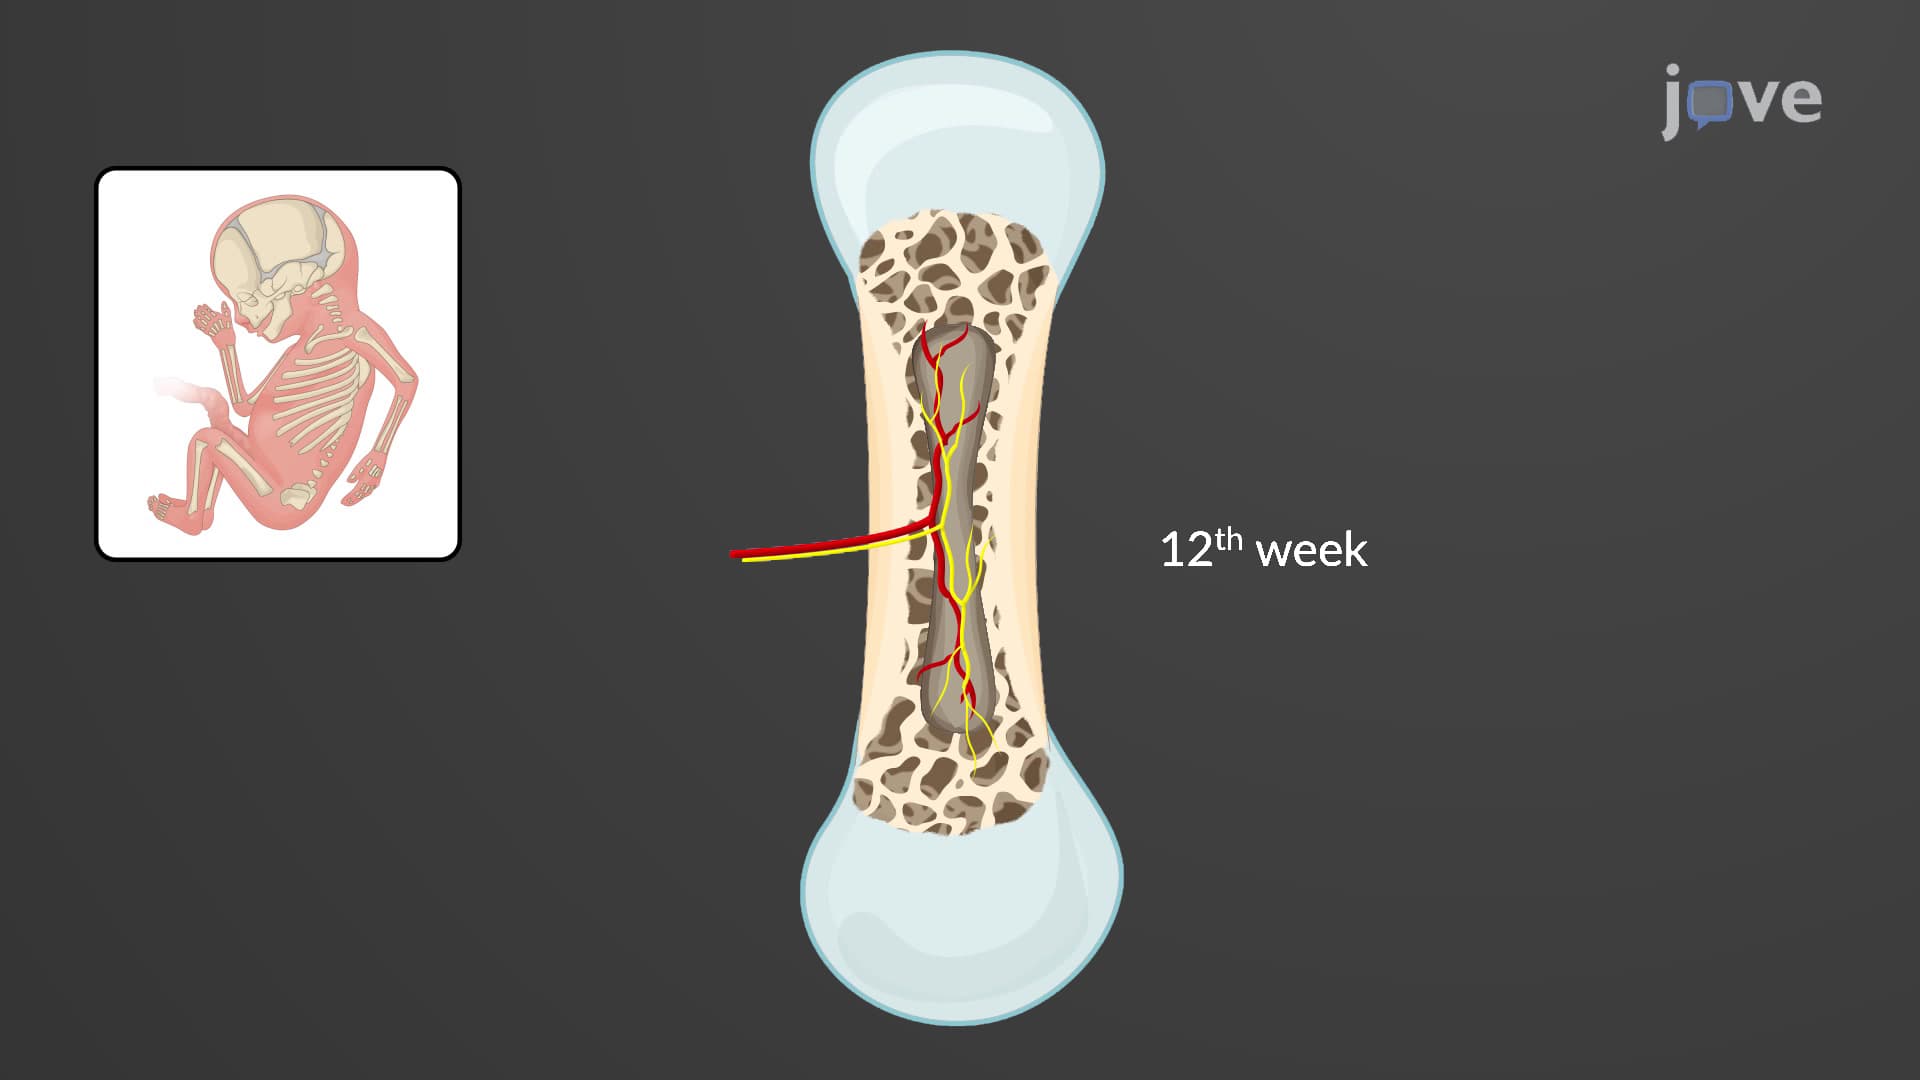
Bone Formation by Endochondral Ossification
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy