Related Experiment Video
Updated: Aug 18, 2026


Adapting Taylor Dispersion to Measure the Dispersion Coefficient of Electrolyte Solutions via an Accessible Microfluidic Setup
Published on: October 7, 2025
The effect of two different protocols of potassium haemodiafiltration on QT dispersion
Michele Buemi1, Emanuele Aloisi, Giuseppe Coppolino
1Department of Internal Medicine, University of Messina, Italy. buemim@unime.it

Insights
Variable potassium removal during haemodialysis (HDF(k)) may reduce arrhythmia risk in patients. This method showed improved ECG markers like QT(c) dispersion compared to standard haemodiafiltration (HDF), suggesting a safer approach for cardiovascular health.
Area of Science:
- Nephrology
- Cardiology
- Biomedical Engineering
Background:
- Patients on haemodialysis face higher cardiovascular disease and arrhythmia risks.
- Potassium concentrations influence cardiac arrhythmias in these patients.
- Electrocardiogram (ECG) parameters like QT interval dispersion (QT(d)) and corrected QT dispersion (QT(cd)) indicate arrhythmia risk.
Purpose of the Study:
- To compare the effects of standard haemodiafiltration (HDF) with constant potassium and HDF with variable potassium (HDF(k)) on ECG parameters and arrhythmia risk.
- To assess plasma electrolytes, intra-erythrocytic potassium, and red blood cell membrane potential during different dialysis methods.
Main Methods:
- A cohort of 28 haemodialysis patients underwent both HDF and HDF(k) treatments.
- ECG measurements (QT, QT(d), QT(c), QT(cd)) were taken at multiple time points during dialysis.
- Plasma electrolytes, intra-erythrocytic potassium, and resting electrical membrane potential (REMP) were measured concurrently.
Main Results:
- HDF(k) resulted in a more gradual decrease in plasma potassium compared to HDF.
- REMP reduction was greater and more significant with HDF than HDF(k).
- HDF(k) demonstrated statistically significant reductions in QT(d), QT(c), and QT(cd) compared to HDF, indicating lower arrhythmia risk.
Conclusions:
- Haemodiafiltration with variable potassium (HDF(k)) significantly impacts QT(c) differently than standard HDF.
- ECG data suggest HDF(k) may lower arrhythmia risk due to variable potassium removal.
- HDF, unlike HDF(k), induced hyperpolarization, potentially destabilizing cardiac cells.
Background:
The risk of developing cardiovascular diseases is higher in patients on haemodialysis than in the general population. These patients may develop arrhythmias that depend on the extra- and intracellular concentrations of potassium. ECG findings, particularly the QT interval and its dispersion (QT(d)) and the QT(c) (QT interval corrected for heart rate according to Bazett's formula) and its dispersion (QT(cd)), may be direct indicators of the risk of developing arrhythmia.
Methods:
Our cohort comprised 28 patients who were dialysed for 3.5-4 h three times per week, first with haemodiafiltration with a constant potassium concentration (HDF) in the dialysis bath then with haemodiafiltration with variable concentrations of potassium (HDF(k)). ECGs were done at different time intervals: at the start of dialysis (T(0)), at 15 (T(15)), 45 (T(45)), 90 (T(90)) and 120 min (T(120)) after the beginning of the session, and at the end of treatment (T(end)). ECG-derived data (QT, QT(d), QT(c) and QT(cd)) were measured. At the same time points, plasma electrolytes, intra-erythrocytic potassium and the electrical membrane potential at rest (REMP) of the erythrocytic membrane were measured.
Results:
Plasma potassium concentration diminished more gradually in HDF(k) than in HDF, the difference being statistically significant at T(15) and T(45) (P<0.05), and T(90) (P<0.01). The intra-erythrocytic potassium concentration remained constant throughout the observation period. In both HDF and HDF(k), REMP was lower at all points after T(0) (P<0.05), but the reduction was greater and more significant in HDF than in HDF(k) at T(15) and T(120) (P<0.05). ECG revealed a statistically significant diminution in HDF(k) vs HDF in the measures of dispersion of QT and QT(c) at T(15), T(90), T(120) and T(end) (P<0.01) and of QT(cd) at T(45) (P<0.05). The mean of QT(d), adjusted for plasma potassium, increased over time in HDF with large alternate mean increase and decrease peaks and error intervals. In HDF(k), instead, there was a progressive and constant diminution with minor error intervals. QT(cd) adjusted for plasma potassium had the same trend. A marked difference was found between the final values in standard HDF and those in HDF(k).
Conclusions:
HDF and HDF(k) have significantly different effects on QT(c). ECG data demonstrate that the risk of arrhythmia could be lower, with a variable removal of potassium during haemodialysis. With HDF but not HDF(k), hyperpolarization of the cell membrane is detected, and this could have a destabilizing effect on different types of cardiac cell, giving rise to retrograde circuits.
Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:15
Dialysis
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
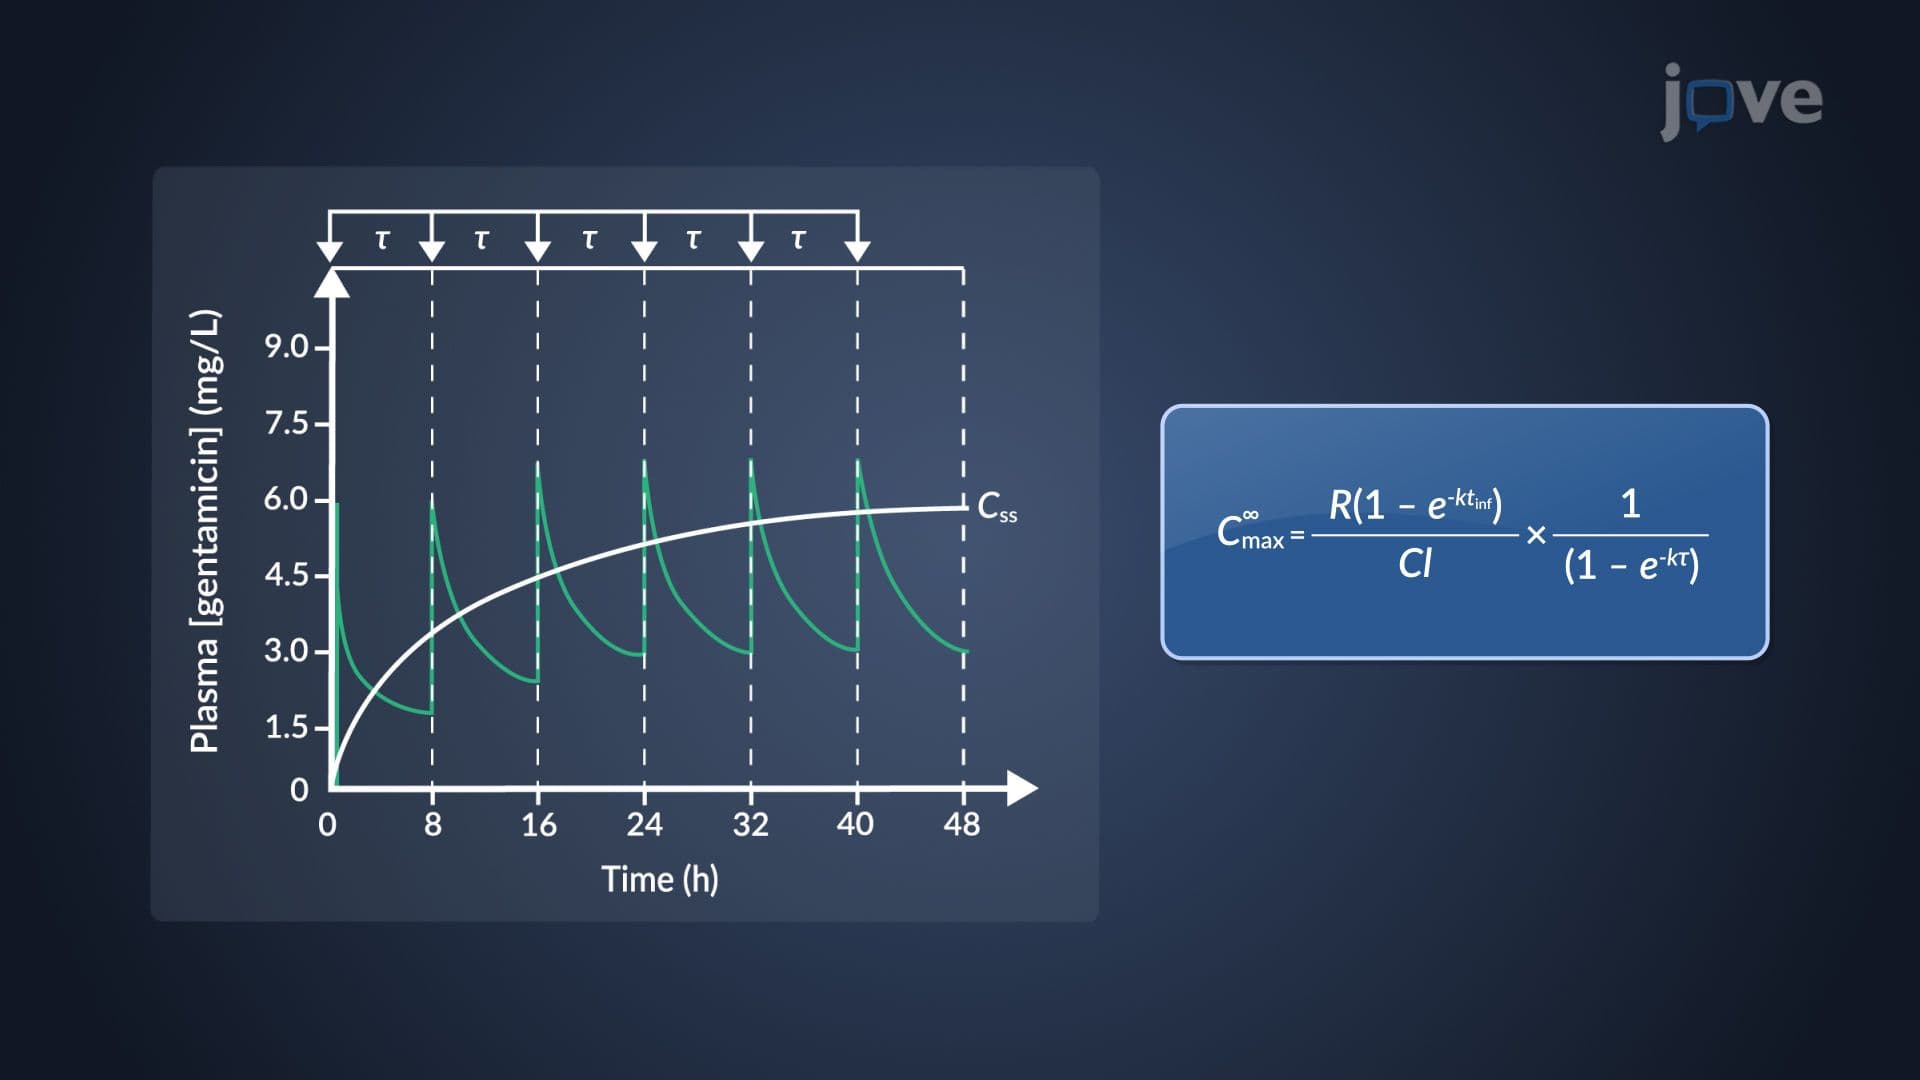 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
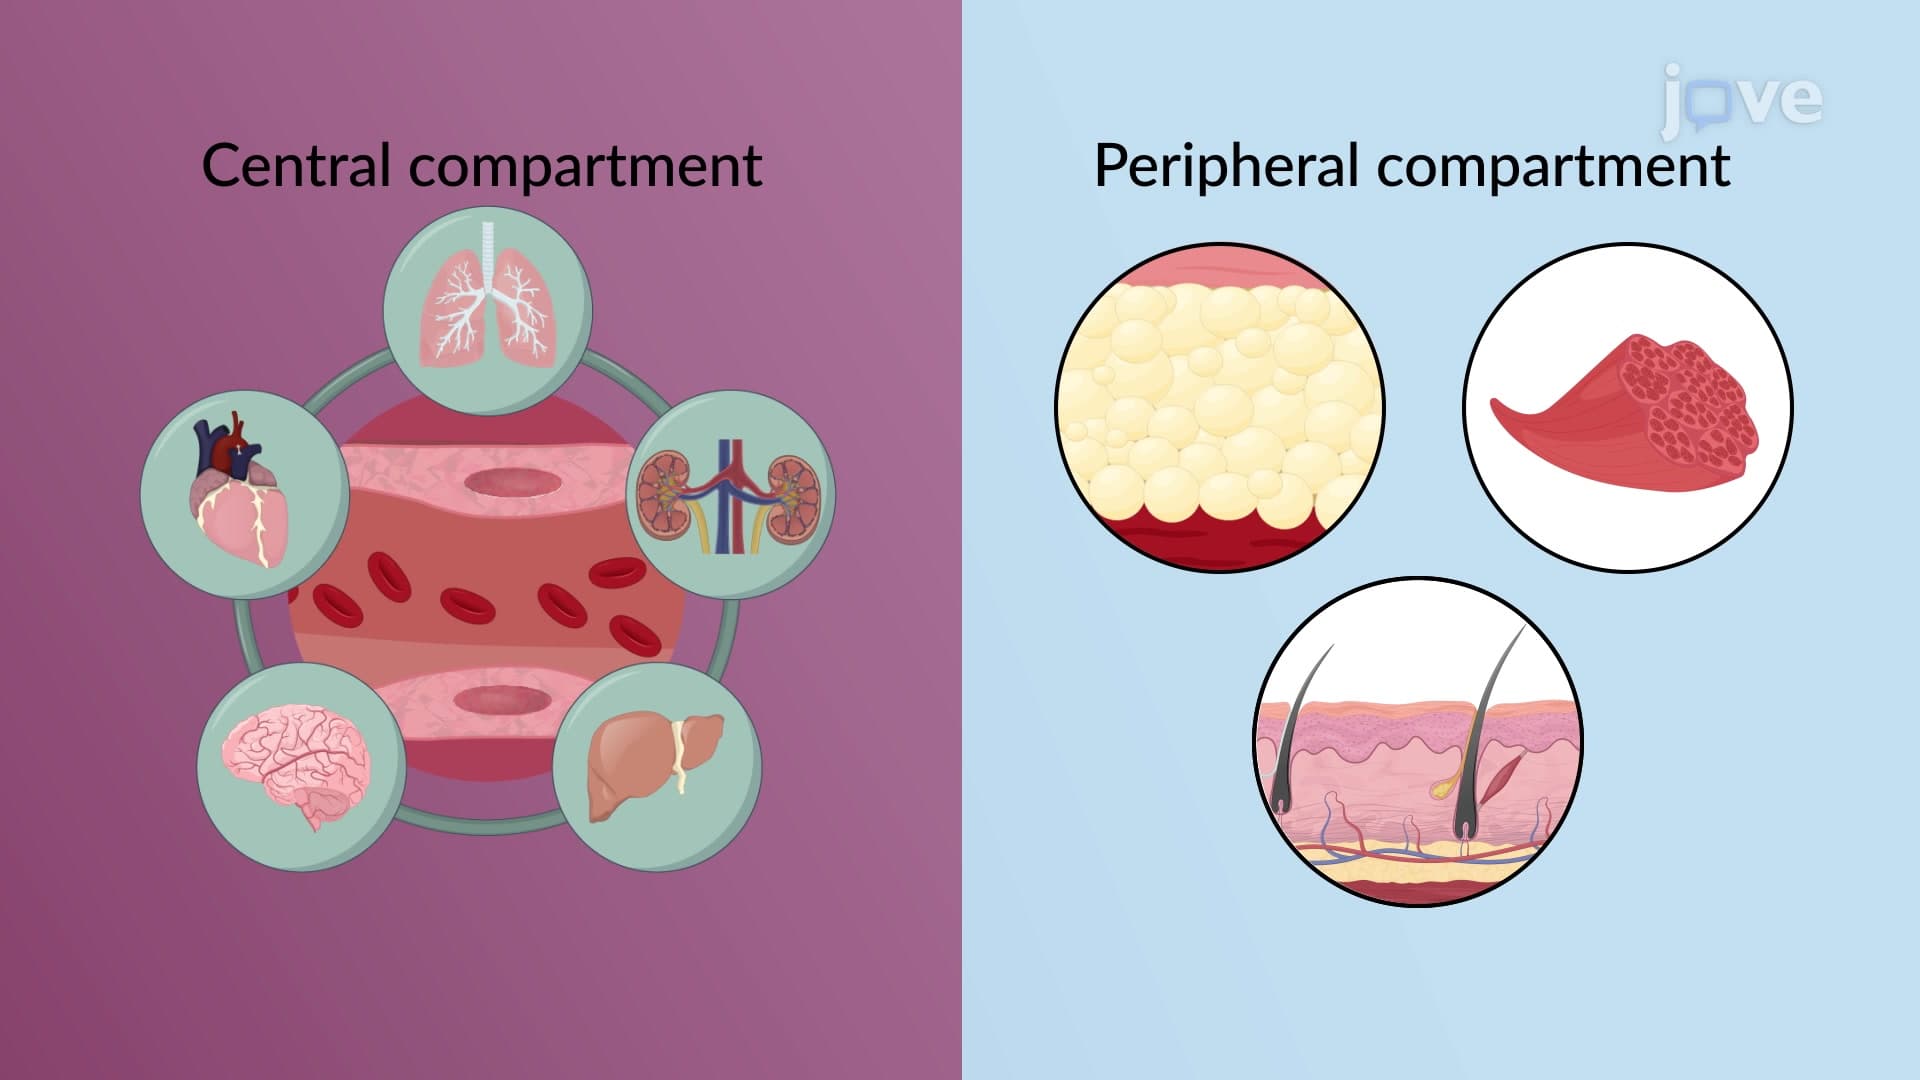 01:20
Compartment Models: Two-Compartment Model
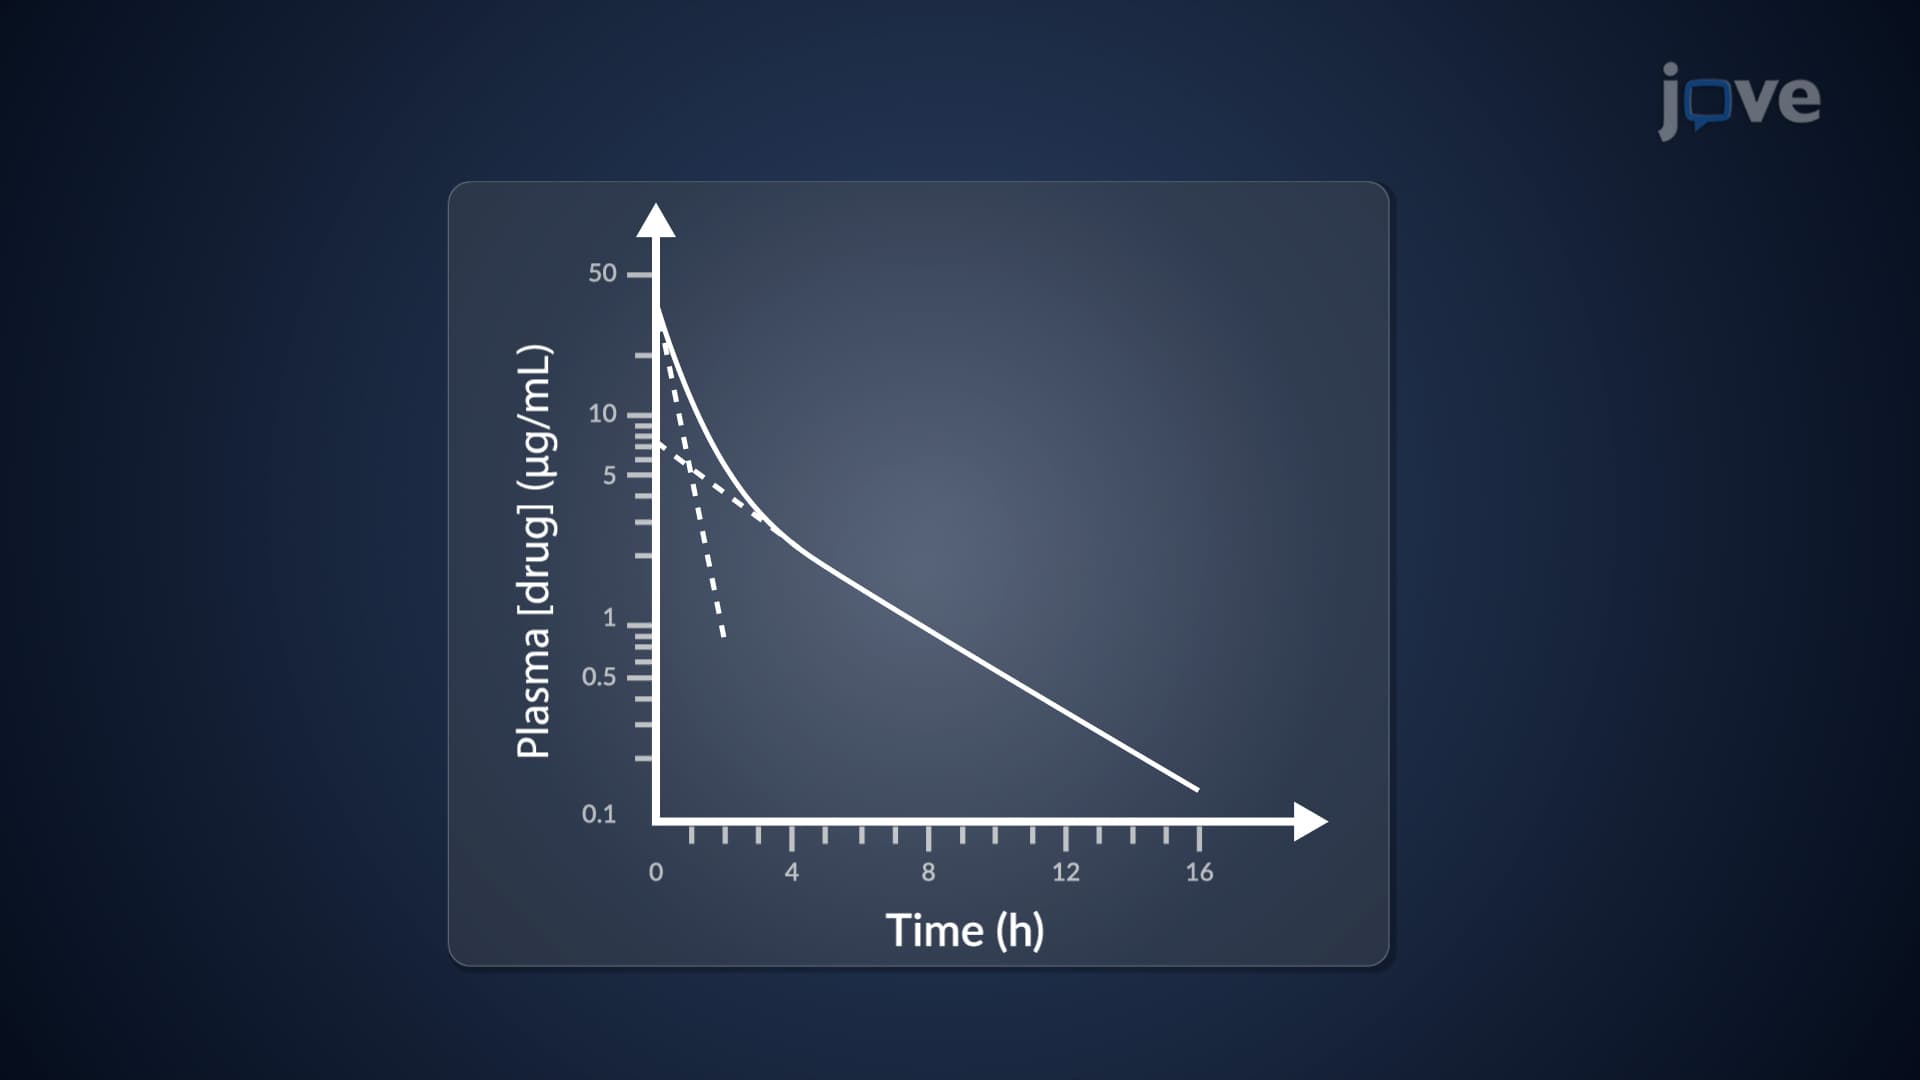 01:18
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...