Related Experiment Videos
Is laparotomy necessary in the diagnosis of fever of unknown origin?
R Ozaras1, A D Celik, K Zengin
1Department of Infectious Diseases and Clinical Microbiology, Istanbul University, Cerrahpasa Medical Faculty, Istanbul, Turkey. rozaras@yahoo.com

Abstract:
Fever of unknown origin (FUO) is a diagnostic challenge for the practising physician. Detailed medical history, physical examination, non-invasive laboratory tests, and radiologic examinations compose the first level in the diagnostic approach to the FUO. When a diagnosis cannot be established with these procedures, some invasive diagnostic techniques and finally exploratory laparotomy are performed. Although advanced diagnostic measures and imaging-guided less invasive procedures have decreased the need, laparotomy remains as a final diagnostic method for FUO cases. In this study we evaluate the role and importance of laparotomy in the diagnosis of our FUO cases. In 17 out of 126 patients (8 male, 9 female, the median age 35.8 years) hospitalized in our clinic between 1982 and 2002 with the diagnosis of FUO, the diagnosis was established by laparotomy. The diagnosis was made directly in 13 patients, and indirectly (by excluding other diseases) in 2 patients. In several FUO series, the contribution of laparotomy to the diagnosis of FUO was reported as 27-100%. This rate was found to be 88% in the present study. During laparotomy on 17 cases, tissue samples were taken from spleen, liver, intra-abdominal and mesenteric lymph nodes. Pathologic examination of these tissue samples revealed miliary tuberculosis in 4; non-Hodgkin's lymphoma in 3; Hodgkin's lymphoma in 3; liver tumour in 1; hairy cell leukemia in 1; peritonitis carcinomatosis in 1. In the patients with miliary tuberculosis, the liver (3) and/or spleen (2), and/or lymph node (3) revealed caseating granulomas. Laparotomy diagnosed 3 of 5 cases whose abdominal ultrasonography and computerized tomography were normal. In conclusion, although advanced diagnostic methods decreased the need for laparotomy in FUO, if non-invasive and invasive diagnostic measures fail, laparotomy may contribute to the diagnosis. The selection of the patient and the timing are important for laparotomy.
Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
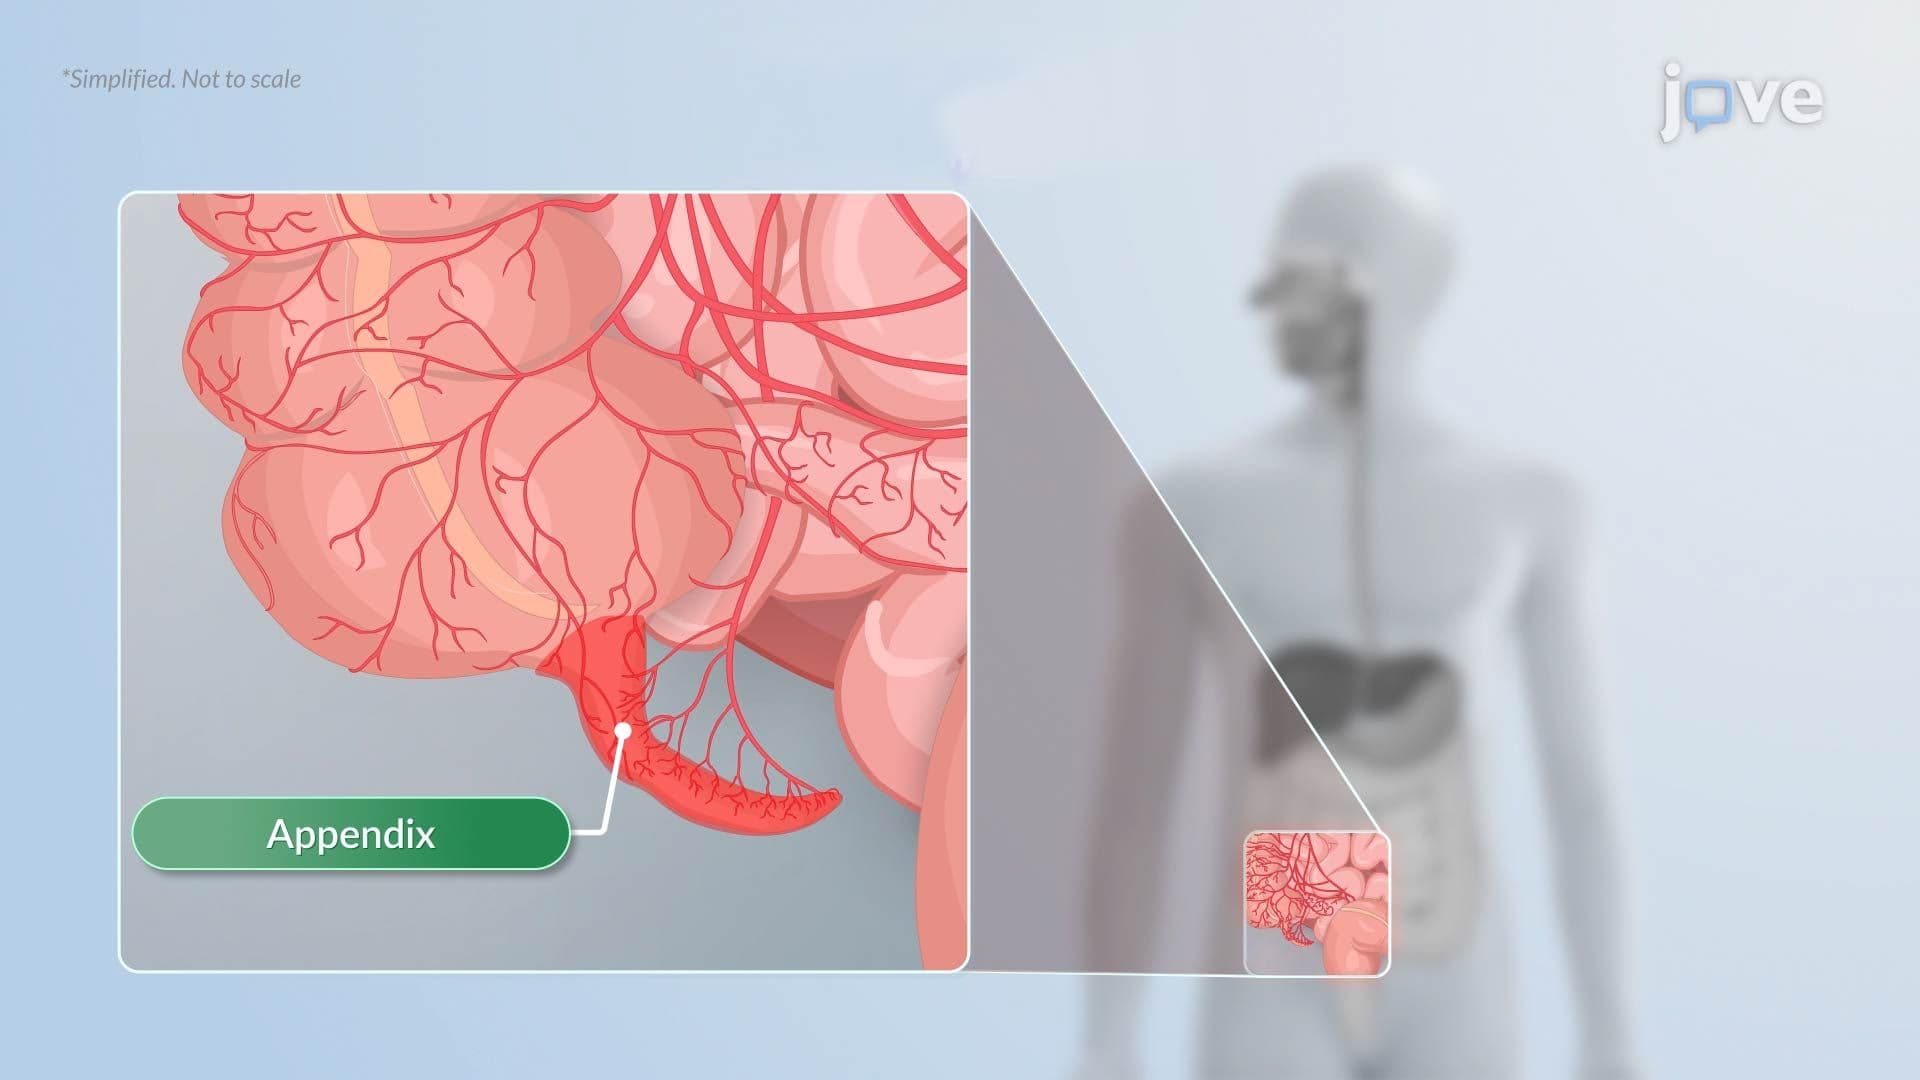 01:19
Appendicitis